Medicare Advantage Competition at the Local Level: A Case Study of Birmingham, Alabama
Competition is central to the design of Medicare Advantage (MA), with the potential to encourage plans to improve quality, lower enrollees’ out-of-pocket costs, and offer additional benefits. Yet in many parts of the country, MA enrollment is highly concentrated among just one or two insurers. Birmingham, Alabama, stands out. Unlike many local MA markets, Birmingham …
Competition is central to the design of Medicare Advantage (MA), with the potential to encourage plans to improve quality, lower enrollees’ out-of-pocket costs, and offer additional benefits. Yet in many parts of the country, MA enrollment is highly concentrated among just one or two insurers.
Birmingham, Alabama, stands out. Unlike many local MA markets, Birmingham has sustained a relatively high level of competition: five or more Medicare Advantage organizations have competed in the market over the past decade, and today eight MA organizations compete for most enrollees.
In a new case study,Medicare Advantage Competition at theLocal Level: A Case Study of Birmingham, Alabama, Georgetown University’s Medicare Policy Initiative examineswhy Birmingham’s MA market is more competitive, how plans compete for enrollees, and what that competition means for beneficiaries and the Medicare program.
The report identifies several factors that have helped foster competition in Birmingham, including:
A large Medicare population with high MA enrollment
Growth in Special Needs Plans
Employer use of MA for retiree coverage
Medicare payment policies that make the market attractive to plans
Alabama’s approach to Medicaid, which has facilitated entry by D-SNPs
The Birmingham experience also illustrates an important policy tension: more competition can produce meaningful benefits for enrollees, but not every form of competition necessarily produces greater value for beneficiaries or taxpayers.
The case study highlights questions for policymakers about MA payment, supplemental benefits, quality incentives, and how to promote the beneficial effects of competition while limiting unintended consequences.
Sustaining Medicare’s Stand-Alone Prescription Drug Plans (PDPs): Part 1—Why are PDP options declining for Medicare beneficiaries?
When beneficiaries first become eligible for Medicare and during each year’s open enrollment period, they have the opportunity to decide whether to get coverage through traditional Medicare (TM) or a Medicare Advantage (MA) plan. Although that decision involves many factors, one key consideration is how they will get prescription drugs. Beneficiaries who use TM typically enroll in …
When beneficiaries first become eligible for Medicare and during each year’s open enrollment period, they have the opportunity to decide whether to get coverage through traditional Medicare (TM) or a Medicare Advantage (MA) plan. Although that decision involves many factors, one key consideration is how they will get prescription drugs. Beneficiaries who use TM typically enroll in a stand-alone prescription drug plan (PDP), while beneficiaries who choose MA usually have drug benefits as part of their MA prescription drug plan (MA-PD).
To continue offering beneficiaries a meaningful choice between TM and MA, policymakers need to ensure that both PDPs and MA-PDs are available and affordable. But currently, prescription drug coverage through PDPs is substantially more expensive than coverage offered through MA-PDs, and there has been a steep drop in PDP availability. In this blog, we review how:
Beneficiaries in TM face higher premiums and declining numbers of PDPs;
Part D’s redesign and other factors have led to higher spending;
Policy actions have moderated premium increases for beneficiaries, but only temporarily; and
MA’s payment system offers MA-PDs a competitive advantage over PDPs.
A subsequent blog will discuss policy options for sustaining the PDP market and their tradeoffs.
Beneficiaries in traditional Medicare have higher premiums and fewer plan options
Most stand-alone PDPs are more expensive than getting prescription coverage through MA-PDs. In 2026, PDP monthly premiums average $36 but can range from zero to well over $100 for plans with enhanced (basic plus supplemental) benefits. Most enrollees in MA-PDs have enhanced benefits and pay an average of just $8 per month; 75% of enrollees pay no premium at all. MA-PDs can offer zero- or low-premium drug coverage because they can use a portion of the MA payments they receive from the federal government to buy down Part D premiums.
1) It increased the generosity of Part D’s standard benefit, improving affordability for many beneficiaries but also leading to higher drug spending; and 2) It required plans to bear more of the financial risk for their enrollees’ drug spending, which occurred at the same time that prescription spending became harder to predict.
A more generous benefit coincided with higher brand-name and specialty drug spending An important goal of the IRA was reducing beneficiaries’ exposure to high out-of-pocket (OOP) costs for drugs. Prior to 2024, enrollees had to pay 5% coinsurance for each prescription once they reached Part D’s catastrophic threshold, amounting to thousands of dollars in additional OOP spending for certain high-priced medications. The IRA eliminated Part D enrollees’ cost sharing above the catastrophic cap, and in 2025, lowered the cap to $2,000 ($2,100 in 2026). In defining the catastrophic cap for this purpose, the value of supplemental benefits is newly being counted towards that cap. As a result, enrollees in plans with enhanced coverage can reach the threshold with accumulated cost sharing much lower than $2,100. One recent analysis found that non-LIS enrollees in enhanced plans who reached the cap paid an average of $900 OOP in 2025, though they sometimes pay higher monthly premiums to enroll in these plans.
Part D plans took on more financial risk at the same time their costs became less predictable Under Part D, Medicare makes two types of monthly payments for each enrollee’s basic drug benefits—a fixed-dollar (capitated) amount called the direct subsidy that is risk adjusted and, for enrollees who reach catastrophic levels of spending, a portion of the cost of each prescription filled (called reinsurance). The initial intention was that Part D plans would bear most of the risk for their enrollees’ spending through capitated payments, giving them a strong incentive to manage benefit spending. However, over time, Part D spending evolved in ways such that the majority of Medicare’s subsidies took the form of cost-based reinsurance, muting this incentive.
The IRA shifted greater financial liability back to Part D plan sponsors and introduced changes that increased plans’ uncertainty about their benefit costs, at least in the near term. In 2025, while keeping total subsidies stable, Medicare significantly reduced its reinsurance payments to plans and increased direct-subsidy payments. Plans began bearing risk on 60% of benefit spending for brand-name drugs above the OOP cap instead of 15%, at the same time that the cap was lowered, leaving plans uncertain about how many more prescriptions enrollees would fill.
Two other factors add to plans’ uncertainty. First, under the redesigned benefit, plans are now responsible for and bear risk on more benefit spending for LIS enrollees. Medicare previously paid for all of LIS enrollees’ benefits in the coverage gap other than their nominal copayments. Second, Part D began using the Maximum Fair Prices (MFPs) for the first 10 drugs selected for price negotiation in Medicare in 2026. Lower MFPsreduce benefit spending but may simultaneously reduce plan sponsors’ privately negotiated rebates with drug manufacturers. Selected drugs are also exempt from manufacturer discounts. The overall effect of these offsetting pressures on Part D premiums is unclear, but both make it more challenging for plans to predict benefit spending.
As a result, plans may bid conservatively (high). For 2025, uncertainty about the benefit redesign’s effects led plans to bid what they thought was conservatively on benefit costs. However, enrollees’ use of brand-name and specialty drugs was even higher than predicted, and plans likely bid too low, correcting upward in 2026.
Some of this uncertainty will diminish over time, as plans get more data on actual utilization and spending and gain experience with the use of MFPs, but it is possible some uncertainty will remain. Time will tell whether there is some flattening in spending growth in the next few years, or whether utilization increases will continue to push spending up.
Temporary steps have kept Part D premiums lower than they would be otherwise
Out of concern about how much premiums might increase after Part D’s benefit redesign, policymakers constrained premium growth through 2029 in the IRA. CMS also initiated a demonstration to limit PDP premium growth that will end this year. These measures moderated premium increases for beneficiaries over the last few years. However, this relief is temporary. Beneficiary premiums are expected to rise sharply in 2030, and some beneficiaries may see higher premiums this year with the demonstration ending.
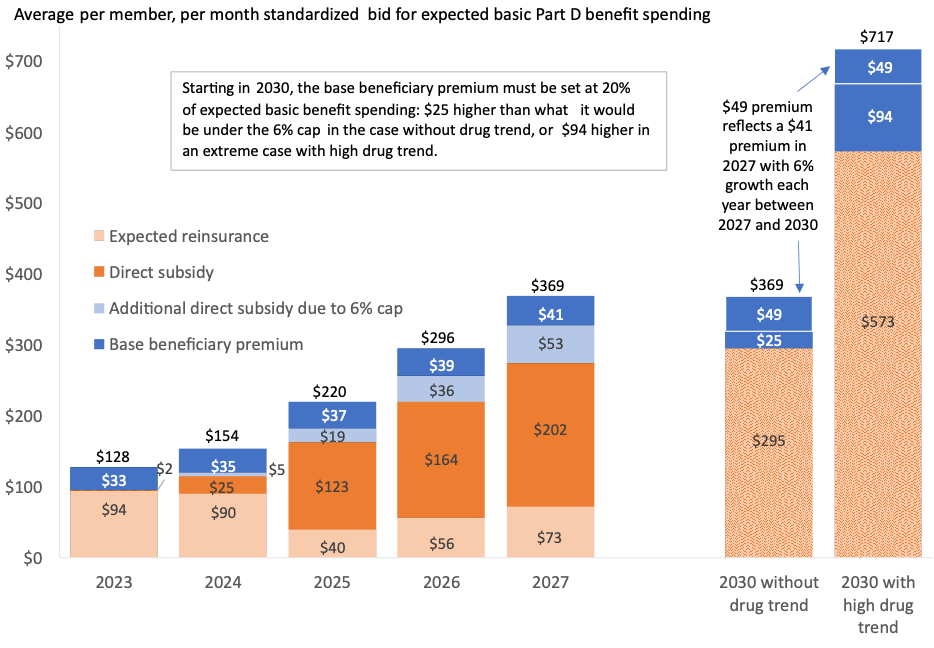
The IRA capped all Part D premium increases through 2029 Policymakers capped annual increases in Part D’s base beneficiary premium (a portion of the average bid among PDPs and MA-PDs) to no more than 6%. This measure has constrained premium growth among PDPs and MA-PDs since 2024 and increased program spending by raising Medicare’s direct subsidy (see Figure 1). For 2027, the cap will limit the base beneficiary premium to $41 per month rather than the $94 per month it would be otherwise.
Figure 1. The IRA’s 6% premium growth cap increased Medicare’s direct subsidy and limited increases in the base beneficiary premium, but premiums will increase sharply in 2030 when it expires
Notes: Sums may not add to totals due to rounding. Values for 2030 are for two hypothetical cases developed by actuary Katie Holcomb—one in which drug trend does not grow from 2027 levels and another in which drug trend between 2027 and 2030 grows each year by the same rate as between 2026 and 2027. The $49 base beneficiary premium in 2030 reflects 6% annual growth from the $41 base beneficiary premium in 2027. Direct spending = the capitated, risk-adjusted amount Medicare pays Part D plans. Base beneficiary premium = a portion of the average bids submitted by PDPs and MA-PDs; the actual premium enrollees pay for their Part D plan may differ from the base premium. Reinsurance = Medicare payments to Part D plans to cover a portion of each prescription’s cost once beneficiaries reach the catastrophic phase. Source: CMS, Office of the Actuary. Annual Releases of Part D National Average Monthly Bid Amount and Other Part C&D Bid Information.
In 2030, the 6% cap will expire and Part D’s base beneficiary premium must instead cover at least 20% of basic benefit costs compared with 13% in 2026 and 11% in 2027, resulting in a large premium jump. If the 6% cap continues to hold each year, the base beneficiary premium would increase from $41 in 2027 to $49 in 2030. One actuary’s analysis suggests that even before accounting for the trend in drug spending, to reach 20% of basic benefit costs, all monthly Part D premiums would automatically increase by $25 (see Figure 1). As an extreme assumption, if drug spending increased each year by the same annual rate as observed between 2026 and 2027 bids, in 2030, all Part D premiums would go up by $94 per month.
Payment system advantages for Medicare Advantage drug plans (MA-PDs)
The way MA-PDs are paid creates certain advantages for MA-PDs over PDPs that contribute to the instability of the PDP market. MA plans receive billions annually in payment rebates from the federal government, fueled in part by much higher federal subsidies to MA plans relative to TM, that they can use to lower their enrollees’ drug premiums and cost sharing. This gives MA-PDs an additional funding source not available to PDPs, and may undermine competition between TM and MA.
In 2026, MA-PDs put about $13 billion of their MA payments, or $51 PMPM, toward lowering their Part D enrollee premiums and cost sharing. The targeted subsidies that PDPs received through the premium stabilization demonstration are swamped by the additional resources MA-PDs have. Once the PDP premium demonstration ends in 2027, MA-PDs can continue to use their rebates to reduce the cost of Part D coverage and the differential between PDP and MA-PD premiums may grow wider. This difference may become especially evident after the IRA’s 6% cap on growth in the base beneficiary premium expires in 2030.
Without additional policy changes, the implications of higher drug spending for Medicare beneficiaries and taxpayers are higher premiums, higher program costs, and potentially even fewer PDPs and qualifying benchmark plans. Having fewer PDPs to choose from could affect beneficiaries’ ability to find a plan that meets their needs, while the higher cost of PDPs could make it harder for beneficiaries to choose TM and further erode its ability to compete with MA.
In a subsequent blog, we will review a number of policy approaches to address the sustainability of the PDP market, including a discussion of their tradeoffs.
MA Enrollee Advisory Group Member Interviewed by New York Times
A recent New York Times article explores the growing role of supplemental benefits in Medicare Advantage—from transportation and fitness programs to allowances for over-the-counter items and groceries—examining both the policy debates surrounding these offerings and their impact on seniors’ daily lives. We’re proud to share that Lorinda Destrini, a valued member of our Medicare Advantage …
A recent New York Times article explores the growing role of supplemental benefits in Medicare Advantage—from transportation and fitness programs to allowances for over-the-counter items and groceries—examining both the policy debates surrounding these offerings and their impact on seniors’ daily lives.
We’re proud to share that Lorinda Destrini, a valued member of our Medicare Advantage Enrollee Advisory Group, was interviewed for the piece. Lorinda shared her firsthand experience utilizing her plan’s healthy food allowances and rides to medical appointments, bringing an essential beneficiary perspective to national discussions on how supplemental benefits support older adults facing rising everyday costs. Read the full article in The New York Times →
The Push for Medicare Advantage Transparency: How Recent Legislation in the House Targets Existing Data Gaps
With Medicare Advantage (MA) becoming the dominant form of coverage in Medicare, understanding MA is central to understanding the cost and quality of care that Medicare beneficiaries receive, as well as their experience in the program. The growth in MA also has important implications for Medicare spending. The Medicare program pays substantially more for MA …
With Medicare Advantage (MA) becoming the dominant form of coverage in Medicare, understanding MA is central to understanding the cost and quality of care that Medicare beneficiaries receive, as well as their experience in the program. The growth in MA also has important implications for Medicare spending. The Medicare program pays substantially more for MA enrollees than it does for similar beneficiaries enrolled in traditional Medicare, and will pay MA plans a projected $615 billion this year for benefits covered under Parts A and B.
Despite the important role MA plays in today’s Medicare program, policymakers, Medicare beneficiaries, and researchers face major gaps in understanding how federal dollars are used by MA plans, the results these plans achieve, and their impact on beneficiaries and the broader health care system. The lack of transparency undermines effective oversight of the Medicare program and efforts to understand the value MA provides to beneficiaries and taxpayers. Limited information about key differences between MA plans, such as their use of prior authorization, also hinders beneficiaries’ ability to navigate the complex set of coverage options and select a plan that reflects their preferences.
In July 2026, the House Energy and Commerce and Ways and Means Committees debated and advanced a slate of bills aimed at requiring more transparency and reporting from MA plans on key aspects of the program, including supplemental benefits, payments and cost sharing, medical loss ratios, and prior authorization. The committee markups represent an unusually strong bipartisan push for greater transparency and oversight of MA. The number and scope of MA policies considered are notable, especially given that nearly all of the bills advanced without a single opposing vote. The bipartisan support suggests a growing recognition that the large amount of federal spending and MA’s role in shaping enrollees’ care merit additional reporting in targeted areas that are foundational to understanding and overseeing the MA program.
We discuss the information gaps these bills would help fill, if passed, and opportunities to improve policymakers’ ability to assess and oversee the performance of the MA program and beneficiaries’ ability to choose a plan that meets their needs.
Improving Transparency: Supplemental Benefits
Why does it matter?
MA plans use rebate dollars paid to them by the federal government to pay for supplemental benefits (such as hearing aids, dental care, gym memberships, and over-the-counter allowances) and reduce out-of-pocket costs for enrollees. Rebates to MA plans have more than doubled in the past decade and are expected to average about $2,660 per enrollee in 2026—an all-time high—as the result of coding intensity, favorable selection, and other factors that have led to more generous MA benchmarks and higher payments. Special needs plans receive even larger rebates of $3,300 per enrollee; they expect to spend more than $2,500 of that on non-Medicare covered benefits. Last year, Medicare’s rebate payments to plans totaled $84 billion.
There is little publicly available information on how MA plans use their rebate dollars, the supplemental benefits enrollees use and their cost, or the value the benefits provide to enrollees or taxpayers, despite the large amount the Medicare program spends on rebates each year and plans’ extensive marketing of supplemental benefits to enrollees.
What would the bills do?
The bill advanced by the House Energy and Commerce Committee would require plans to report enrollee-level use and spending for supplemental benefits. The Ways and Means Committee advanced a similar bill; however, it appears to call for plan-level rather than enrollee-level reporting. Both bills would take steps to improve the public availability of the supplemental benefit data, including requiring CMS to make the data available to researchers and to publicly post a file with information on supplemental benefit use, plan spending on these benefits, and the amount enrollees pay when they use the benefits.
What are the policy implications and considerations?
The House bills’ reporting requirements would support greater oversight over how Medicare dollars are spent and improve policymakers’ ability to assess the value of the large federal investment in supplemental benefits. The data the requirements yield will be most meaningful for oversight and research efforts if they are provided at the enrollee level and can be linked with data on enrollee outcomes and utilization to allow researchers to assess whether specific benefits are well-targeted to enrollees based on need and whether their use improves enrollee health outcomes.
Improving Transparency: MA Plan Payments and Enrollee Cost-Sharing
Why does it matter?
While CMS currently collects certain billing information through the encounter data system, including some payment information, there are significant gaps in our understanding of MA payments to providers and enrollee out-of-pocket costs. For example, while the potential for lower out-of-pocket costs can be an important draw for MA enrollees, existing transparency gaps make it difficult to assess how much enrollees actually pay out of pocket for health care services and how those costs vary across plans. Information on payments and enrollee spending is omitted from the data provided to researchers.
In addition, many non-claims-based payments, such as payments made through capitated and value-based arrangements, are not captured in the encounter data, although they are common in MA and important to understanding overall payment levels. Information on the amount and structure of these arrangements could help policymakers assess their implications for other aspects of the program, including medical loss ratio calculations, coding incentives, and plan and provider behavior.
What would the bills do?
The Energy and Commerce and Ways and Means Committees advanced legislation that would require MA plans to report additional information in their encounter data on payments, enrollee cost sharing, and ownership relationships with certain entities. First, the legislation would require MA plans to include the billing amount for each item or service furnished to an enrollee, as well as what the enrollee paid out of pocket. The Energy and Commerce Committee version of the bill would also require plans to report payments for care provided under value-based or capitated arrangements using a methodology established by the Secretary. Both versions of the bill require MA plans to indicate when an enrollee receives an in-home health risk assessment from an entity they share common ownership with.
What are the policy implications and considerations?
This information is essential to understanding payments to providers—an important driver of MA plans’ costs—in addition to government and enrollee spending. In combination with the supplemental benefit reporting described above, these data would provide a more complete picture of how MA plans use the federal dollars they receive, and the costs associated with the care and benefits provided to enrollees. The usefulness of these new data will depend on their accuracy and completeness. MA encounter data have well-documented challenges with reliability and completeness, making continued efforts to assess and enforce plan compliance with reporting requirements important to ensuring the new information can support meaningful research and oversight.
Improving Transparency: How MA Plans Spend Premium Dollars
Why does it matter?
The medical loss ratio (MLR) is intended to protect consumers and taxpayers by requiring that MA plans spend at least 85% of premium revenue on providing care to enrollees and quality improvement activities. As insurers have increasingly acquired physician practices, home health agencies, and other health care entities over the past decade, experts have raised concerns that vertical integration may weaken the effectiveness of the MLR requirement. There is the potential for vertically integrated MA plans to inflate the pricesthey pay to their owned entities above competitive market rates, allowing plans to report higher expenses for the purposes of MLR while retaining those profits within the same parent company. Existing data are insufficient to assess the extent to which this potential MLR gaming is occurring and to effectively enforce the MLR requirements.
What would the bills do?
Bothcommittees advanced bills to increase the information publicly available on health plans’ MLRs. The legislation would require MA plans to post on their websites, in a consumer-friendly format, the components that make up their MLR. This includes the amount of premium revenue each plan collects, the claims costs they incur when enrollees receive care, and the amount spent on non-claims costs, as well as their MLR itself (i.e., the percent of premium revenue spent on claims and other qualifying expenses).
What are the policy implications and considerations?
These bills would make information about how plans are spending premium dollars and their MLR more accessible for consumers. However, they would not provide additional insight into how vertical integration may be affecting MA plans’ pricing and MLR compliance. To strengthen oversight, policymakers could consider expanding the MLR transparency provision to collect information on MA plans’ related-party entities and their payments to those entities. This information could be collected more narrowly in the context of MLR reporting or as part of broader efforts to increase the transparency of MA plans’ ownership relationships and payments to health care entities they contract with given the impact that widespread, insurer-led vertical integration can have not only on MLR compliance, but also on coding intensity, payments, patient referrals, and other outcomes.
Improving Transparency: Prior Authorization, Denials, and Appeals
The Improving Seniors’ Timely Access to Care Act requires more granular plan-level reporting of prior authorization requests, denials, and response times, as well as additional information such as disclosing whether artificial intelligence or other technology was used in making prior authorization decisions. Under the bill, MA organizations must report this information to CMS, which would be required to post it on its website. Displaying the information in a centralized location rather than on individual plan websites could allow beneficiaries to more easily access and compare information across plans.
What are the policy implications and considerations?
The transparency provisions included in the legislation could provide policymakers, beneficiaries, researchers, and providers with better information on how prior authorization is used across MA plans. More granular plan-level information could be particularly useful to beneficiaries because prior authorization practices may affect their experience accessing care and be an important consideration when comparing and selecting coverage options. For policymakers, these more detailed data could also support oversight and enforcement of existing prior authorization requirements and help identify where additional guardrails may be needed to protect enrollees’ access to needed care.
Conclusion
MA now accounts for the majority of enrollment and spending in the Medicare program. Yet, in contrast to the traditional Medicare program where the government has broad access to standardized data on utilization, cost, and quality, there is limited information on core features of MA that affect beneficiary outcomes and experiences, as well as Medicare spending. The bipartisan legislation that the House Energy and Commerce and Ways and Means Committees recently advanced to the House floor would help improve transparency in the MA program, particularly when coupled with strong enforcement mechanisms and other measures to increase the usefulness of the information.
Institutional Special Needs Plans (I-SNPs) Explained
Institutional Special Needs Plans (I-SNPs) are Medicare Advantage (MA) plans available to beneficiaries who need the level of care provided in a nursing facility or psychiatric facility. A new explainer from the Medicare Policy Initiative describes I-SNPs in the MA market and outcomes, issues with oversight of I-SNPs, and raises unanswered questions about the I-SNP program. …
Institutional Special Needs Plans (I-SNPs) are Medicare Advantage (MA) plans available to beneficiaries who need the level of care provided in a nursing facility or psychiatric facility.
A new explainer from the Medicare Policy Initiative describes I-SNPs in the MA market and outcomes, issues with oversight of I-SNPs, and raises unanswered questions about the I-SNP program. Download the explainer to learn more about:
How I-SNPs compare to other types of MA plans
The growth of I-SNPs in the MA market
The impact of I-SNPs on Medicare spending
Concerns that I-SNPs may draw dually eligible beneficiaries away from more integrated plan options
I-SNPs have the potential to align nursing home and Medicare incentives, yet the lack of available information on I-SNPs’ impact on Medicare spending requires additional reporting and regulation.
Chronic Condition Special Needs Plans (C-SNPs) Explained
Chronic Condition Special Needs Plans (C-SNPs) are Medicare Advantage (MA) plans that focus on one or more chronic conditions. C-SNPs can target 22 different chronic conditions, yet most target cardiovascular disease, chronic heart failure, and diabetes. No C-SNPs currently focus on cancer, substance use disorders, or stroke. Key highlights from this explainer include:
Chronic Condition Special Needs Plans (C-SNPs) are Medicare Advantage (MA) plans that focus on one or more chronic conditions. C-SNPs can target 22 different chronic conditions, yet most target cardiovascular disease, chronic heart failure, and diabetes. No C-SNPs currently focus on cancer, substance use disorders, or stroke.
Key highlights from this explainer include:
C-SNPs can generate double the profit of standard MA plans, in part because new enrollees receive higher default risk adjustment scores.
C-SNPs often enroll beneficiaries who are dually eligible for Medicare and Medicaid, but unlike Dual Eligible Special Needs Plans, C-SNPs aren’t required to coordinate with the state Medicaid agency – possibly steering dually eligible beneficiaries away from more integrated care options.
In 2022, 18% of C-SNP enrollees rapidly disenrolled within three months, raising questions about beneficiary understanding and provider eligibility verification.
C-SNPs are growing faster than any other type of MA plan-increasing by 45% between 2025 and 2026. This explainer breaks down how C-SNPs work, why they are growing rapidly, and critical policy questions surrounding their profitability and oversight.
This Health Affairs Forefront piece by Erica Socker and Katie Keith examines how recent court challenges—most notably a federal district court decision in favor of Clover Health—are spotlighting the deep structural flaws of Medicare Advantage’s Quality Bonus Program. Despite costing taxpayers an estimated $16 billion annually, the star ratings system has increasingly become a battleground …
This Health Affairs Forefront piece by Erica Socker and Katie Keith examines how recent court challenges—most notably a federal district court decision in favor of Clover Health—are spotlighting the deep structural flaws of Medicare Advantage’s Quality Bonus Program. Despite costing taxpayers an estimated $16 billion annually, the star ratings system has increasingly become a battleground in the courts. In the wake of the Clover ruling, CMS’s decision to recalculate ratings will funnel hundreds of millions of additional dollars to private insurers, boosting payments without any actual improvement in care quality. As other insurers rush to file copycat lawsuits, we unpack the legal and fiscal fallout, highlighting why this growing instability presents an urgent opportunity for policymakers to rein in runaway overpayments and fundamentally reform the program so that star ratings actually serve Medicare beneficiaries.
Medicare Advantage Enrollees Weigh In: Four Recommendations to Improve Supplemental Benefits
This policy brief examines the challenges MA enrollees face during annual open enrollment and outlines five policy recommendations based on the experiences of a 17-member MA Enrollee Advisory Group (AG). While participants valued the benefits offered by MA plans, they consistently described the process of selecting and comparing plans as complex and difficult to navigate. …
This policy brief examines the challenges MA enrollees face during annual open enrollment and outlines five policy recommendations based on the experiences of a 17-member MA Enrollee Advisory Group (AG). While participants valued the benefits offered by MA plans, they consistently described the process of selecting and comparing plans as complex and difficult to navigate.
AG members highlighted five core hurdles:
Overwhelming advertisements and direct-to-consumer sales tactics during open enrollment cause severe informational overload.
Limited awareness of the official Annual Notice of Change prevents enrollees from effectively tracking yearly cost and benefit modifications.
Usability challenges and filtering limitations within the Medicare Plan Finder complicate side-by-side plan comparisons.
Financial transparency gaps and lack of disclosure obscure the neutrality of third-party agent and broker recommendations.
Low public visibility and capacity constraints restrict access to State Health Insurance Assistance Program counselors, despite them serving as the most trusted source of guidance.
Download the policy brief to learn about the five recommendations MA enrollees have for policymakers to improve transparency, strengthen consumer protections, enhance plan comparison tools, and expand access to independent enrollment assistance.
CMS’s WISeR Model Faces Potential Repeal Following GAO Determination
On May 20, 2026, Congressional Democrats led by Senators Ron Wyden (D-OR), Rep. Suzan Delbene (D-WA), and Rep. Greg Landsman (D-OH) introduced a resolution to repeal the Centers for Medicare & Medicaid Services’ (CMS) Wasteful and Inappropriate Service Reduction (WISeR) model via the Congressional Review Act (CRA). If certain requirements are met, the resolution could …
On May 20, 2026, Congressional Democrats led by Senators Ron Wyden (D-OR), Rep. Suzan Delbene (D-WA), and Rep. Greg Landsman (D-OH) introduced a resolution to repeal the Centers for Medicare & Medicaid Services’ (CMS) Wasteful and Inappropriate Service Reduction (WISeR) model via the Congressional Review Act (CRA). If certain requirements are met, the resolution could come to a vote with immunity from a Senate filibuster.
Last year, the Medicare Policy Initiative published a blog summarizing the requirements of the six-year WISeR model, as well as concerns about potential harm to patients. In short, WISeR aims to reduce unnecessary, duplicative, and “low-value” care in Traditional Medicare by 1) introducing prior authorization requirements to a subset of items and services in Traditional Medicare, and 2) leveraging enhanced technologies—including artificial intelligence (AI)—in the prior authorization process. CMS is currently testing the model in six states: Arizona, New Jersey, Ohio, Oklahoma, Texas, and Washington.
CMS officially implemented the WISeR model on January 1, 2026, partnering with six companies to implement its prior authorization requirements. In this blog, we detail the key actions that led to the CRA resolution and provide updates on the WISeR model since its formal introduction.
Congressional Pushback on the WISeR Model Prior to Implementation
In July 2025, Reps. Alexandria Ocasio-Cortez (NY-14) and Lloyd Doggett (TX-37), along with 40 of their colleagues, sent a letter to CMS urging the agency to halt implementation of the WISeR model, citing concerns similar to those previously discussed. In response, CMS issued a list of Frequently Asked Questions (FAQs) that clarify certain aspects of the model. The FAQs emphasize that WISeR does not change Medicare coverage or payment of the included services. CMS also stated that Participants (i.e., companies conducting prior authorizations under the model) would be financially penalized for inappropriate denials and that providers and beneficiaries would maintain the right to appeal denied claims.
However, the FAQs did not fully address concerns raised by some Members of Congress and stakeholder organizations. In November 2025, Reps. Delbene (WA-01), Landsman (OH-01), Bera (CA-06), Schrier (WA-08), Pocan (WA-02), and Larsen (WA-02) introduced legislation that would have prohibited CMS from implementing the WISeR model. The House Appropriations Committee also adopted an amendment to the Fiscal Year 2026 Labor, Health and Human Services, Education, and Related Agencies (LHHS) Appropriations bill that would have withheld appropriations funding for the model, but this amendment was not included in the final Act that was signed into law.
Despite this opposition, CMS moved forward with implementation, announcing the six model participants in December 2025:
Cohere Health, Inc. as the vendor for Texas
Genzeon Corporation as the vendor for New Jersey
Humata Health, Inc. as the vendor for Oklahoma
Innovaccer Inc. as the vendor for Ohio
Virtix Health LLC as the vendor for Washington
Zyter Inc. as the vendor for Arizona
Early Implementation: Anecdotal Reports of Technical Challenges and Low Approval Rates
Due to technical issues, the WISeR model became effective on January 15th, 2026 rather than January 1st. Following implementation, some providers reported problems with online portals, technical glitches, and communication with model participants. The Washington Post reported that, in Texas, approximately 62% of prior authorization requests received initial approval. The approval rate increased to 84% after a physician review following initial non-authorization. This is lower than reported approval rates for prior authorization requests in MA, which often exceed 90%, although rates vary across services and plans. These figures also reflect a limited period of implementation in a single state and may not be representative of overall model performance. Other analyses suggest the impact of the WISeR model may be more modest, partially because WISeR services account for a small percentage of Medicare Part B spending and relatively few beneficiaries use these services.
The Speed of Implementation Leads to a Lawsuit and Modifications to the Model
In March 2026, the Electronic Frontier Foundation, a digital and privacy rights nonprofit, filed a Freedom of Information Act lawsuit against CMS seeking additional information about the technologies and AI tools being used by model participants. In April 2026, CMS announced it would delay the implementation of two services under the WISeR model “to allow additional time for operational readiness”: Deep Brain Stimulation for essential tumors and Parkinson’s disease as well as Percutaneous Image-Guided Lumbar Decompression for spinal stenosis.
Democrats Invoke the Congressional Review Act
While CMS continued implementation of the model, Democrat-led congressional scrutiny also intensified. A series of oversight efforts culminated in a Government Accountability Office (GAO) determination that WISeR constitutes a rule for purposes of the CRA.
Under the CRA, federal agencies are required to submit rules to Congress before they can take effect. If an agency fails to submit a rule to Congress, Congress may take certain special procedures to repeal the rule or stop the rule from going into effect. This process is generally triggered when Members of Congress request that the GAO produce a formal opinion as to whether an agency’s action satisfies the definition of a rule. A GAO determination may trigger the CRA’s expedited procedures for a joint resolution of disapproval, which can be used to repeal a rule or prevent it from taking effect.
In December 2025, Senators Wyden, Murray, Gillibrand, and Blumenthal sent a letter to the GAO requesting it determine whether the WISeR model constitutes a rule. On May 12, 2026, the GAO concluded that the WISeR model meets the Administrative Procedure Act definition of a rule since, among other things, the model prescribes new requirements for Traditional Medicare providers in certain states by mandating prior authorization for certain services.
Congressional Democrats Introduce Joint Resolutions of Disapproval to Repeal WISeR
As a result of GAO’s determination, Senate and House Democrats separately introduced joint resolutions of disapproval. Senator Ron Wyden (D-OR) sponsored the resolution in the Senate, while Reps. Suzan DelBene (D-WA.) and Greg Landsman (D-OH) introduced the resolution’s House counterpart. Both resolutions have attracted numerous Democratic co-sponsors.
Under the CRA, Congress has a limited 60-day period following a GAO determination during which Members may seek expedited consideration of a joint resolution of disapproval, and the joint resolution cannot be filibustered in the Senate, if the Members meet certain requirements. If the resolution passes both chambers of Congress and is signed by the President, CMS would be required to terminate the model.
Conclusion
The WISeR model remains one of the most closely watched demonstrations currently underway at CMS. Five months into implementation, the available evidence remains limited. Early reports suggest that some providers have experienced technical challenges and lower-than-expected approval rates, while CMS has already modified certain aspects of the model by delaying implementation for select services. At the same time, questions remain regarding the technologies used by model participants, the model’s payment incentives, and its overall impact on beneficiary access to care.
The recent GAO determination and subsequent CRA resolutions have introduced a new level of uncertainty regarding the model’s future. While it remains unclear whether Congress will vote to repeal the model, these recent developments underscore broader questions surrounding the model’s future. The model ultimately raises broader policy questions about the role and future of prior authorization, artificial intelligence, and utilization management tools in Medicare.
Beyond Insolvency: The Bigger Picture of Medicare’s 2026 Financial Outlook
On June 9, the Medicare Trustees published their annual report on the financial outlook for the Medicare program. The report calls attention to the serious fiscal challenges facing the Medicare program, which provides coverage to about 70 million Americans aged 65 and older and people with disabilities. It also highlights the large and increasing burden …
On June 9, the Medicare Trustees published their annual report on the financial outlook for the Medicare program. The report calls attention to the serious fiscal challenges facing the Medicare program, which provides coverage to about 70 million Americans aged 65 and older and people with disabilities. It also highlights the large and increasing burden that high Medicare costs place on Medicare beneficiaries and taxpayers. This blog discusses key takeaways from the 2026 Medicare Trustees report, including the rapid growth in Medicare spending in parts B and D and the important role Medicare Advantage plays in driving spending.
Medicare’s Hospital Insurance (HI) Trust Fund Projected to Reach Insolvency in 2033
The Trustees report’s headline news is that the Hospital Insurance (HI) trust fund is expected to reach insolvency in 2033, three months earlier but in the same year as previously projected. The HI trust fund pays for Part A services, such as inpatient hospital stays, skilled nursing and other post-acute care services, as well as hospice care for Medicare beneficiaries. At the point of insolvency, the HI trust fund will be able to reimburse providers only 89 cents for every dollar of Part A services provided, and substantial spending reductions or tax increases will be needed to close the shortfall.
The slight deterioration in the status of the HI trust fund relative to last year’s projection is largely due to changes in the taxation of Social Security benefits enacted in the One Big Beautiful Bill Act that will reduce the trust fund’s revenue.
Focus on the HI Trust Fund Obscures the Bigger Picture of Medicare’s Worsening Fiscal Situation
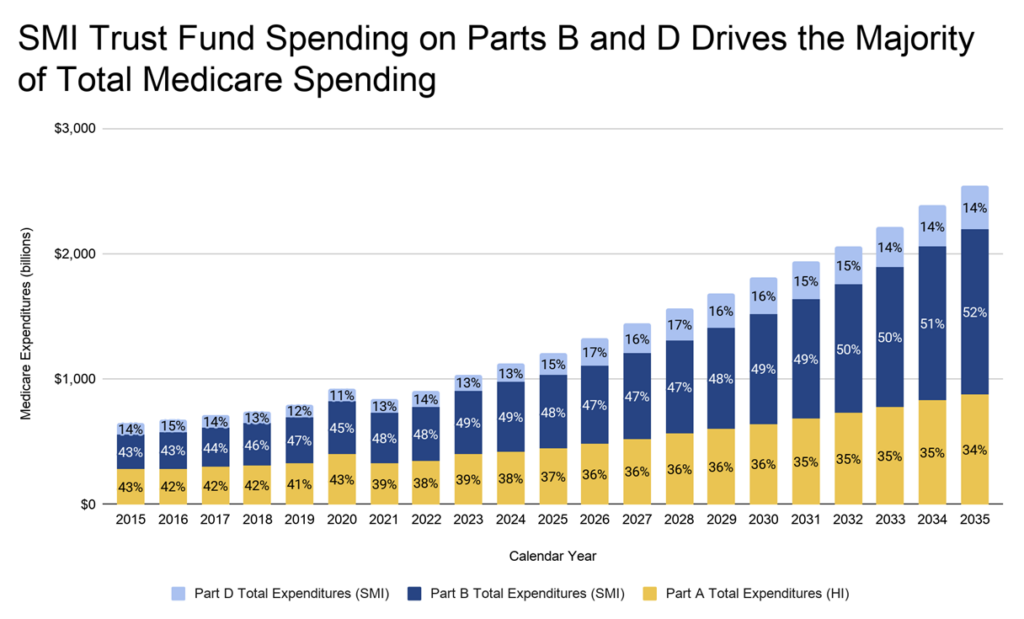
While the HI insolvency year receives significant attention and is pointed to as an indicator of the fiscal health of the Medicare program, perhaps an even more important part of the story relates to spending in the rest of the Medicare program. Spending on outpatient services (Part B) and prescription drugs (Part D) is a larger and faster-growing share of total Medicare spending. The cost of Part B alone – $584 billion in 2025 – dwarfs spending in Part A ($444 billion), and the share of Medicare spending attributed to Part A is declining over time as spending shifts from inpatient to outpatient services.
Source: 2026 Medicare Trustees’ Report Tables III.B4, III.C4, and III.D3
Medicare spending reached more than $1.2 trillion in 2025, and the Medicare Trustees project it will cost nearly $19 trillion over the next decade. This growth is driven by two main factors: 1) the continued aging of the baby boomers into Medicare, and 2) an increase in the volume and intensity of services that Medicare enrollees are receiving. Due to its rapid growth, Medicare spending is projected to continue outpacing the growth in the overall economy, increasing from 3.9% of gross domestic product (GDP) in 2025 to 6.5% by 2050.
Relative to last year’s report, Medicare Part D spending increased substantially in large part due to increased utilization of GLP-1s and high-cost specialty drugs. Projected Part B spending decreased in the short term with recent changes to payments for skin substitutes, but will grow more quickly over the longer term as spending for Part B drugs, typically physician administered drugs, increases.
Spending Growth in Medicare Parts B and D Increases the Financial Burden on Beneficiaries and Taxpayers
The high cost of Medicare Parts B and D places an increasing burden on beneficiaries and taxpayers over time, as higher beneficiary premiums and a larger share of general revenues are required to finance this spending. This is because the trust fund that pays for Part B and Part D services is financed differently from the HI trust fund in important ways.
The HI trust fund pays for services covered by Medicare Part A and is primarily financed through dedicated Medicare payroll taxes on earnings. Beginning in 2027, spending on Part A services will exceed the HI trust fund’s income and begin to draw down the trust fund’s reserves. When the HI trust fund becomes insolvent in 2033, its reserves will be depleted and new revenue coming into the trust fund will be insufficient to cover the full anticipated Medicare cost of Part A services. To date, Congress has always stepped in to avert the insolvency of the HI trust fund.
The Supplementary Medical Insurance (SMI) trust fund pays for all of Part B – outpatient care including physician services, as well as durable medical equipment – and Part D-covered outpatient prescription drugs. In contrast to the HI trust fund, theSMI trust fund can never become insolvent. It is financed through a combination of Medicare beneficiary premiums and federal general revenue (largely corporate and personal income taxes), adjusted each year to cover the anticipated costs of Parts B and D. As the cost of providing the services covered by Parts B and D grows, so do the premiums beneficiaries pay and the amount of general tax revenues needed to fund the Medicare program.
The rapid rise in spending in Parts B and D translates into higher premiums and cost sharing for Medicare beneficiaries. Beneficiary premiums finance about one-quarter of spending in Parts B and D. In 2026, the standard monthly Part B premium jumped by almost 10% to $202.90, exceeding $200 a month for the first time. Annual Part B premiums will increase by 6.6% on average over the next 10 years. The Trustees expect Part D premiums to grow at an even faster pace during that period due in part to the expiration of additional subsidies to dampen premium increases after Part D’s benefit redesign.
As the cost of Part B and D benefits increases over time, a greater share of beneficiaries’ Social Security benefits will likely go to paying these higher out-of-pocket costs. The combined average premiums and cost-sharing that beneficiaries pay for Parts B and D are about one-quarter of the average Social Security benefit in 2026. By 2050, premiums and cost-sharing will increase to more than one-third of the average benefit.
The high cost of Parts B and D also increases the burden on taxpayers who finance the remaining three-quarters of the spending through general revenues, which are primarily deficit-financed. Medicare spending is a major source of growing federal deficits and the increase in the federal debt, which can limit the government’s ability to invest in other priorities and crowd out private investment. Over the next decade, Medicare spending is projected to account for the largest increase in federal spending as a share of GDP, other than outlays for interest on the federal debt. Spending on all other mandatory health programs is projected to decline.
The Increased Role of Medicare Advantage in Driving Medicare Spending
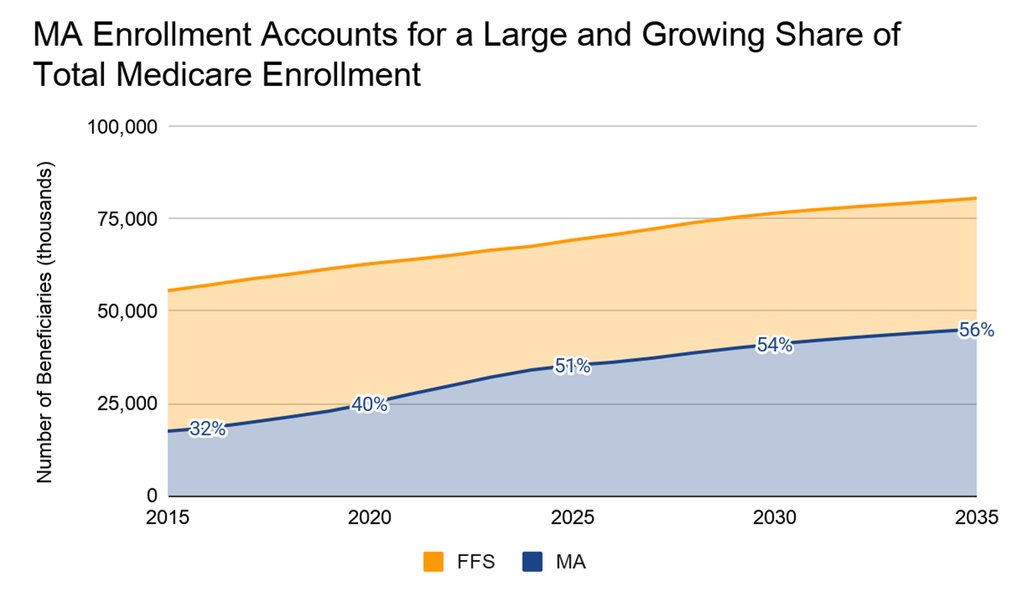
MA accounts for the majority of Medicare enrollment today. MA enrollment experienced a substantial increase over the past decade – rising from 34% of total enrollment in 2017 to 51% today – and is projected to increase to 56% by 2035.
Payments to MA plans are an increasingly important driver of overall Medicare spending as enrollment in MA grows. Over the next decade, MA alone will account for more than $9 trillion of Medicare’s total spending. However, MA is not funded from its own trust fund, and payments to MA will draw on both the HI and SMI trust funds to cover the cost of the Part A and B services these plans provide to enrollees. Roughly 40% of MA plans’ funding comes from the HI trust fund, and 60% comes from the SMI trust fund, although these shares change over time.
A substantial body of evidence finds that the Medicare program pays more to cover MA enrollees than it does for similar beneficiaries enrolled in traditional Medicare. In 2026, Medicare will spend about 14% more to cover MA enrollees, translating into $76 billion in additional spending this year alone.
Codingintensity and favorable selection into MA are responsible for much of this higher spending, although factors such as the quality bonus program in MA and the way MA payment benchmarks are set also play a role. The higher payments to MA plans contribute to rising Part B premiums for beneficiaries in both traditional Medicare and MA, resulting in beneficiaries paying about $11 billion more in premiums in 2026.
Conclusion
The Medicare Trustees report paints a bleak picture of Medicare’s financial health and highlights the urgent need for reforms to lower Medicare spending. Medicare spending is projected to continue increasing faster than Medicare payroll taxes and faster than the overall economy, resulting in projected insolvency of the HI trust fund in the next seven years. Perhaps even more concerning are the projections of higher beneficiary premiums and the need for more deficit-financed general revenue to sustain the program.
Policymakers and experts have proposed a number of solutions that could improve the Medicare program’s fiscal outlook, including reducing wasteful spending in Medicare and raising additional revenue to finance the trust fund. This year’s report emphasizes the important role MA, certain outpatient services, and drugs play in driving Medicare spending. These are all places policymakers could look to when weighing reforms to reduce the program’s spending. A set of policy changes will likely be needed to fully close the Medicare HI trust fund shortfall and slow the growth of Parts B and D spending to put the program as a whole on sounder financial footing.
For a description and brief analyses of potential reforms to the MA and Part D programs, see MPI’s compendium of policy proposals.
Medicare Advantage Insurers and Brokers Fail to Toss Whistleblower Lawsuit
This Health Affairs Forefront article by MPI’s Neil Patil and Ciannah Correa analyzes the ongoing litigation between the Department of Justice (DOJ) and Medicare Advantage brokers on the use of administrative services to disguise illegal kickbacks. The DOJ intervened in the whistleblower lawsuit, alleging that the MA Organizations (MAOs) paid the broker defendants hundreds of …
This Health Affairs Forefront article by MPI’s Neil Patil and Ciannah Correa analyzes the ongoing litigation between the Department of Justice (DOJ) and Medicare Advantage brokers on the use of administrative services to disguise illegal kickbacks. The DOJ intervened in the whistleblower lawsuit, alleging that the MA Organizations (MAOs) paid the broker defendants hundreds of millions of dollars in ”kickbacks” disguised as ”marketing” funds to influence brokers to sell their plans.
The DOJ alleged that MAOs and brokers incorrectly labeled kickbacks as marketing payments while the MAOs and brokers claimed these payments were in fact marketing services. The court agreed with the DoJ that these payments were not administrative payments based on the substance of the agreement.
Brokers argued that the Anti-Kickback Statute (AKS) targets “medical care kickbacks” and not health insurance plans. The court disagreed with defendants noting that the AKS was designed to strengthen the Medicare and Medicaid programs, and its scope includes insurers.
The court agreed with DoJ that MAOs violated the False Claims Act (FCA) by falsely certifying compliance with the AKS and anti-discrimination laws. Brokers then argued it was MAOs that violated the FCA, not the brokers, since they submitted the false claims, but the court still found the brokers’ conduct violated the FCA.
While the court’s decision reinforced DOJ’s reliance on the FCA to address MA marketing abuses, there are still significant roadblocks to passing broker regulations. Additionally, ongoing discussions of the constitutionality of whistleblower lawsuits could damage efforts to ensure integrity in Medicare. This lawsuit demonstrates the importance of the FCA in deterring bad actors, but there is still a need for meaningful regulatory oversight in addition to litigation.
[Event] Leveling the Playing Field in Medicare Advantage: The Role of Smaller Plans in a Changing Market
On Monday, May 4, 2026, Georgetown’s Medicare Policy Initiative in collaboration with Arnold Ventures hosted a briefing, “Leveling the Playing Field in Medicare Advantage: The Role of Smaller Plans in a Changing Market.” Speakers included: Access slides from the briefing here.
On Monday, May 4, 2026, Georgetown’s Medicare Policy Initiative in collaboration with Arnold Ventures hosted a briefing, “Leveling the Playing Field in Medicare Advantage: The Role of Smaller Plans in a Changing Market.”
Speakers included:
Alec Aramanda, Principal Deputy Director, Center for Medicare, CMS
Matt Eyles, Executive Vice President, Government & Business Strategy, Alignment Health
From “Flat” to Favorable: How Medicare Advantage Payments Increased in the Calendar Year (CY) 2027 Rate Announcement
In January 2026, the Centers for Medicare & Medicaid Services’ (CMS) Calendar Year (CY) 2027 Medicare Advantage (MA) Advance Notice proposed what appeared to be a near-flat payment update: a 0.09% increase, or roughly $700 million before accounting for expected MA risk score growth. This blog examines what changed between the Advance Notice and the final Rate Announcement, why payments increased, and how common this pattern has been in recent years.
This upward revision is notable, but it is far from unprecedented. In fact, it reflects a broader pattern in MA rate-setting: proposed payment updates are often revised upward in the final Rate Announcement. This blog examines what changed between the Advance Notice and the final Rate Announcement, why payments increased, and how common this pattern has been in recent years.
A Near-Flat Starting Point: CY 2027 Advance Notice
The CY 2027 Advance Notice initially signaled a restrained approach to MA payments. The proposed 0.09% increase suggested a year of minimal growth, particularly when compared to prior years of more robust payment updates.
After factoring in expected growth in costs of nearly 5%, CMS proposed several policy changes that would have led to this relatively modest increase, most notably:
Updating the Risk Adjustment Model: CMS proposed updating the underlying Medicare fee-for-service (FFS) data used to calibrate the Version 28 (v28) risk adjustment model from 2018 diagnoses and 2019 expenditures to 2023 diagnoses and 2024 expenditures. This would have updated the model to reflect more recent spending patterns associated with various diseases, conditions, and demographics. When combined with the normalization factor, an adjustment to account for projected growth in Medicare FFS spending between 2024 and 2027, updates to the risk adjustment model would have been the single largest factor behind the modest proposed update.
Limiting Sources of Diagnoses: CMS proposed excluding diagnoses derived from chart reviews (CRRs)not linked to a clinical encounter. This proposal aimed to address longstanding concerns about how MA coding intensity leads to higher MA payments than under Medicare FFS, worsening the financial sustainability of the program. CMS also proposed refinements to exclude diagnoses from audio-only encounters.
Taken together, these proposals signaled that CMS had planned to tighten MA payments through both technical updates and policy changes that targeted coding practices.
A Meaningful Increase: CY 2027 Rate Announcement
When CMS finalized the CY 2027 Rate Announcement, it incorporated a 2.48%—or over $13 billion— MA payment increase over 2026 levels, due to more complete spending data and policy decisions to reverse some of the agency’s initial proposals. When accounting for the MA risk score trend, this amounts to a 4.98% (or approximately $26 billion) MA increase over 2026 levels.
Several key changes explain this shift:
Updated Medicare FFS Spending Data Increased the Effective Growth Rate: CMS incorporated newly available FFS data through the fourth quarter of 2025 when calculating the effective growth rate. Because FFS spending trends were stronger than previously estimated, this update contributed modestly (0.36 percentage points) to higher MA payment rates.
Modification to the Unlinked CRR Policy: While CMS finalized its proposal to exclude diagnoses from unlinked chart reviews, it introduced an important modification: diagnoses from unlinked CRRs will still be allowed for beneficiaries who switch between MA organizations. This adjustment softened the policy’s financial impact. Without it, the reduction in MA payments for 2027 would have been approximately -1.78%, compared to -1.53% as finalized.
CMS’ Deferral to Update the Risk Adjustment Model Data: Most notably, CMS chose not to finalize the proposal to update the v28 model with more recent Medicare FFS data. Instead, the agency retained the existing calibration (based on 2018 diagnoses and 2019 expenditure data), citing a desire to “allow the MA market more time to adjust” following the recent phase-in of the v28 model. This decision substantially reduced the negative impact on payments. The combined effect of risk model revisions and the normalization factor would have reduced MA payments in 2027 by -3.32%. After the decision to keep the older risk adjustment model, the final Rate Announcement noted that the normalization factor alone would lower payments by a comparatively smaller –1.12%.
A Familiar Pattern
The CY 2027 experience is not an outlier—it is part of a consistent historical trend. Table 1 shows that the final MA payment rates between 2016 and 2027 averaged 1.26 percentage points higher than what CMS proposed in each year’s Advance Notice.
While many different factors can contribute to the changes between the proposed and final MA payment rates, two structural features of the MA rate-setting process help explain this pattern. First, the effective growth rate is frequently revised upward as more complete Medicare FFS data becomes available. Over the past 11 years, the effective growth rate has been higher in the Rate Announcement than in the Advance Notice in 9 out of 11 years.
Second, CMS often modifies or delays policies that would significantly reduce payments, particularly in response to industry concerns. As highlighted in CY 2027, CMS modified its proposal to exclude unlinked CRRs and decided not to update the risk adjustment model, which pushed the final MA rate higher.
Similar types of industry-friendly modifications have occurred in the past. For instance, in 2023, CMS proposed to fully implement the v28 model in 2024, which would have led to a modest 1.03% payment increase for 2024. In light of comments received, in the finalized CY 2024 Rate Announcement, CMS chose instead to phase-in the model over a three-year period and the final payment increase for CY 2024 landed at 3.32%. These types of adjustments can reflect practical considerations, such as market stability, but can also reflect an especially strong responsiveness to industry feedback, especially when proposals would result in large payment shifts.
Table 1. Year-to-Year Expected Average Change in CMS-Reported MA Revenue and Effective Growth Rate, Calendar Years 2016-2027
Calendar Year
CMS Reported Effective Growth Rate
CMS Reported Expected Average Change in MA Revenue
Effective Growth Rate (Advance Notice)
Effective Growth Rate (Rate Announcement)
Percentage Point Difference Between Advance Notice and Rate Announcement
Advance Notice
Rate Announcement
Percentage Point Difference Between Advance Notice and Rate Announcement
Sources: Data was compiled as reported in the CMS Advance Notice Fact Sheet and CMS Rate Announcement Fact Sheet, as reported by CMS with respect to each calendar year from 2016 to 2027. As noted in the MPI blog entitled, “Apples to Oranges: Including the MA Risk Score Trend in CMS’s Estimates of MA Payments”, CMS has historically been inconsistent in including the MA risk score trend in the “year-to-year percentage change bottom-line table” which can be found in each Advance Notice and Rate Announcement fact sheet.
Implications for Plans, Beneficiaries, and Policymakers
The CY 2027 Rate Announcement presents a mixed picture.
MA plans will receive an approximate $26 billion payment increase in 2027. For MA plans, the higher-than-expected payment increase—particularly when combined with risk score growth—represents a positive development. Payments are projected to be approximately $26 billion higher when accounting for risk trends, providing additional financial flexibility.
At the same time, the 2027 MA payment increase is smaller than those seen in some recent years. If enrollees’ use of services continues to rise, MA plans that are less successful at managing care may face pressure to adjust benefits and cost structures. These adjustments could include higher premiums, increased cost sharing, reduced supplemental benefits, more constrained provider payments, reduced access to care, or selective market exits. MA plans may also need to trim administrative costs and accept lower margins. Nevertheless, the overall MA market has withstood other financially challenging times and yet maintained robust plan choices and supplemental benefit offerings in most areas.
Looking Ahead: A Structural Feature, Not an Exception
The continued pattern of upward revisions raises important questions about the MA rate-setting process. While some increases are driven by updated data, others reflect policy decisions that have historically tended to favor the industry. The CY 2027 Rate Announcement underscores a key reality: upward revisions from the proposed MA payments to the final MA rates are structurally embedded in the MA payment process.
CMS’ decision to delay updating the risk adjustment model highlights a larger issue. While calibrating the v28 model on older 2018 diagnoses and 2019 expenditure data may support short-term stability, it also prolongs reliance on pre-COVID data that may be less reflective of current spending patterns. CMS itself notes that the longer the agency waits to update the v28 model, the larger the year-over-year bottom line repercussions for MA organizations may be. Rather than focusing solely on proposed versus final payment rates, policymakers may want to pay greater attention to how to improve incentives in the MA program. This includes examining how payment policies influence coding intensity, care management, benefit design, and plan participation—and whether those incentives are driving value for beneficiaries and taxpayers. Medicare beneficiaries and taxpayers are best served when MA organizations focus their resources on managing their enrollees’ care more than identifying diagnoses. As CY 2027 demonstrates, the difference between proposed and final rates is only part of the story. A more durable path forward will require focusing not just on payment levels, but on designing policies that promote high-quality, efficient care across the MA program.
How CMS Policies to Reverse Protections for Medicare Beneficiaries Reflect a Broader Deregulatory Push
The Centers for Medicare & Medicaid Services has finalized its Contract Year 2027 Medicare Advantage (MA) and Part D final rule. In this blog, MPI’s Neil Patil examines how policies finalized in this rule alter the regulatory framework governing MA marketing and how these changes fit within a broader shift in federal regulatory philosophy.
Deregulation is a key strategy of the Trump Administration. In fact, an executive order signed on January 31, 2025 directed federal agencies to repeal ten regulations per every new regulation that is issued. This push to deregulate was evident in certain Medicare Advantage (MA) marketing rules finalized in Centers for Medicare and Medicaid’s (CMS) Contract Year (CY) 2027 MA and Part D final rule where CMS reversed several Biden-era rules aimed at regulating the marketing of MA plans.
Background
Medicare beneficiaries have long reported that they receive an overabundance of advertising from MA plans and third-party marketing organizations (TPMOs). There has been clear evidence that misleading marketing materials and certain TPMO marketing and sales strategies have resulted in increased confusion and, for some, enrollment in MA plans without the beneficiaries’ knowledge.
The Biden Administration sought to address problems with MA marketing through the CY 2023–2025 MA and Part D rules. These rules were aimed at curbing misleading marketing, improving oversight of agents/brokers and TPMOs, and reducing financial incentives that could steer beneficiaries into plans. CY 2023-2025 MA and Part D final rule actions to regulate the marketing of MA plans under the Biden Administration included the following:
Require TPMO disclosures: Marketing entities must clearly disclose that they do not offer every available plan in the beneficiary’s area and must identify the insurers they represent.
Disclose plan sponsors in ads: If a TPMO advertises plan benefits, it must identify the MA organizations offering those plans with the same prominence as the benefits themselves.
Oversight obligations: MA plans must maintain compliance programs to monitor agents and brokers and report non-compliance to CMS.
Prohibit misleading marketing language or imagery, including claims that cannot be substantiated (e.g. unsupported superlatives like “best”).
Restrict use of the Medicare name, logo, or card in advertisements unless approved and used in a non-misleading way.
Prohibit marketing of benefits not available in a beneficiary’s service area or exaggerated savings claims based on unrealistic comparisons.
Broaden CMS review of advertisements by expanding the definition of “marketing” so more ads must be submitted to CMS for approval before use.
As a result of these rules, in 2024, CMS reported that since 2023, the agency has issued denials for over 1,500 TV ad submissions that were non-compliant and misleading to consumers. As discussed in the CY 2027 MA and Part D final rule, many of these new Biden-era MA marketing requirements were characterized by the MA industry as creating unnecessary delays, administrative burden, and paperwork without providing meaningful beneficiary protection. However, some research has also shown that many smaller MA plans support these marketing reforms. This is because marketing deregulation tends to favor large, national insurers with the financial resources to dominate the marketing sector.
President Trump’s Executive Order Directs Federal Agencies to Repeal Ten Existing Regulations for Every New Regulation
On January 31, 2025, less than 2 weeks after taking office, President Trump signed Executive Order (EO) 14192, “Unleashing Prosperity Through Deregulation,”. This EO established one of the most ambitious deregulatory initiatives in recent federal policy. The order directs federal agencies to repeal at least ten existing regulations for every new regulation issued, unless prohibited by law. It also requires that the total incremental cost of new regulations to fall “significantly less than zero” in fiscal year 2025, effectively mandating a net reduction in regulatory costs across the federal government.
The order frames regulatory reduction as a core economic priority. According to the policy statement accompanying the order, the Administration argues that federal regulations impose “massive costs” that restrain innovation, limit economic growth, and create compliance burdens for businesses and individuals. The Office of Management and Budget (OMB) was tasked with implementing the initiative through a regulatory budgeting framework, requiring agencies to track regulatory costs and offset new rules by eliminating existing ones.
CMS Reverses MA Marketing Protections
On April 6, 2026, CMS released the CY 2027 MA and Part D final rule, a sweeping annual regulatory package that touches nearly every aspect of the programs—from quality ratings and enrollment rules to marketing practices. While much of the policy discussion has focused on the technical details of those changes, the rule is best understood in the broader political context of the Trump Administration’s regulatory philosophy.
In particular, several of the marketing-related proposals appear to be part of the wider deregulatory effort tied to EO 14192. Importantly, when these rules were first proposed, CMS explicitly tied them to the broader deregulatory mandate of EO14192—noting that several provisions are intended to “reduce burden and remove requirements that are duplicative or no longer necessary.”
The CY 2027 MA and Part D final rule reflects the deregulatory philosophy described in the EO by reversing several marketing and communications rules implemented during the Biden Administration. New CY 2027 changes that reduce regulation of MA marketing:
The new 2027 final rule eliminates certain restrictions governing the timing and structure of marketing events. Under previous requirements, MA plans were required to separate educational events from marketing events and follow strict rules about when marketing discussions could occur. The new 2027 final rule allows marketing activities to occur immediately after educational events and in the same location, provided beneficiaries receive appropriate notice.
The new 2027 final rule removes the48-hour waiting period between a beneficiary signing a scope-of-appointment form and meeting with an agent, allowing agents and brokers to discuss plan options more quickly after a beneficiary expresses interest.
Another change involves the use of superlatives in marketing materials. Previous CMS rules restricted terms such as “best” or “top-rated” unless plans could substantiate those claims. The rule removes those restrictions, arguing that broader prohibitions against misleading information already provide sufficient oversight.
In addition, the rule would reduce the required retention period for recorded marketing calls from ten years to six years, lowering compliance costs for plans and TPMOs.
In addition to marketing changes, the rule includes other deregulatory actions, such as:
Eliminating certain health equity reporting requirements
Rescinding the requirement that MA plans send mid-year notices about unused supplemental benefits
Issuing a Request for Information (RFI) seeking ideas for additional regulatory streamlining in Medicare, further signaling the Administration’s intention to pursue broader regulatory reduction in the program.
Taken together, these changes would significantly reduce the administrative requirements governing Medicare Advantage marketing practices.
The Policy Debate
Proponents and opponents of the final rule’s new measures debate a fundamental question: are existing consumer protection laws and CMS oversight mechanisms sufficient to protect beneficiaries without the more detailed marketing rules established by the Biden Administration?
The CY 2027 MA and Part D final rule illustrates how regulatory policy in Medicare Advantage is increasingly shaped by broader political and administrative priorities. EO14192 created a government-wide directive to reduce regulatory burdens and eliminate existing rules as a condition of issuing new ones. In the Medicare Advantage program, that mandate appears to be translating into a reconsideration of several oversight mechanisms adopted in recent years—including those governing plan marketing and agent/broker conduct. Whether these changes will ultimately improve the Medicare Advantage market – or create new challenges for beneficiaries – will depend on how CMS balances regulatory simplification with the need for strong consumer protections.
As policymakers weigh the success of recent reforms, this blog explores why the a mathematically projected decline in MA overpayment percentages from the latest version of the risk adjustment model (v28) alone should not be mistaken for a final resolution to the well-documented issue of coding intensity, and how the potential impact of CMS’s latest changes proposals to exclude unlinked chart reviews may come into play.
For years, high coding intensity in the Medicare Advantage (MA) program, sometimes caused by “upcoding,” has served as what many policymakers and analysts view as a central flaw in the MA program. The Medicare Payment Advisory Commission (MedPAC) estimates that, in 2026, higher coding intensity by MA plans directly contributes to $22 billion out of a total $76 billion in higher payments to MA, as compared to what the government would have paid if those enrollees were instead in Medicare Fee-For-Service (FFS). While estimates of higher payments vary by year and methodology, the direction of the finding is not largely contested, despite the fact that the MA program was originally created to lower costs for the federal government while achieving the same or better-quality care as Medicare FFS by leveraging private insurers’ expertise.
Has the phase-in of v28 solved upcoding?
Changes to the MA risk adjustment model can reduce coding intensity and achieve federal savings. Since 2024, CMS has been phasing in version 28 (v28) of its hierarchical condition category risk-adjustment model. V28 aims to decrease MA plans’ rates of coding intensity and upcoding by reclassifying some of the most commonly coded diagnoses – those that led to higher payments without corresponding increases in care provided – to make them harder to code inappropriately, among other technical changes and updates. It has been fully phased in for 2026.
MedPAC annually revises its estimate of how MA payments compare to what federal spending would have been under Medicare FFS to incorporate more recent data. This year, the topline is striking: It found that higher MA coding intensity (and upcoding) will result in 4% higher payments to MA plans for 2026. That’s much lower than MedPAC’s previous estimates. Higher coding now accounts for less than a third of the total estimated 14% higher payments to MA plans than what spending would have been in Medicare FFS.
MedPAC estimates that uncorrected coding intensity, or coding intensity by MA plans above and beyond the 5.9% statutory coding pattern adjustment that resulted in overpayments to MA, reached its highest level at about 10% in 2022 and 2023. It’s tempting to compare that peak to the recent 2026 estimate of 4% – leading some to see those numbers and ask: Has v28 “solved” upcoding?
In this blog, we’ll break down why a conclusion that v28 has solved upcoding completely is incorrect and discuss where policymakers might consider going from here.
What v28 has effectively done so far:
In 2025, MedPAC estimated that, before CMS’s statutory requirement to reduce MA payments by 5.9%, MA spending was 16.4% higher than what federal spending would have been if the same beneficiaries were in Medicare FFS. MedPAC annually estimates MA coding intensity for the latest available data year, and then projects trends forward to evaluate higher MA spending for more recent years. For example, to prepare estimates for its 2025 report, MedPAC analyzed MA payment data from 2023, data from when CMS used the previous v24 risk adjustment model.
In its March 2026 report, MedPAC lowers its estimates for coding intensity in 2025 from 16.4% to 12.5% after incorporating newer data from 2024 — the first year of the v28 phase-in. This more recent data also allowed MedPAC to revise its estimates about how quickly risk scores have been growing over time – a dominant factor in the estimated decrease in coding intensity
After deducting CMS’s 5.9% coding pattern adjustment and accounting for a slower risk score trend, MedPAC now finds that 4% of overpayments are likely because of higher coding intensity.
Signs that there are still aspects of upcoding that v28 has not fully fixed:
MedPAC estimates that coding intensity is still 10.3% higher in MA than Medicare FFS.
Average MA risk scores are still increasing relatively year over year, as demonstrated by CMS’s annual calculation of a positive risk score trend in the Advance Notice.
Drastically high coding intensity is still achievable under v28, with one MA organization reported to have over 20% higher coding intensity relative to Medicare FFS during the v28 phase-in as of 2024. MedPAC has reported a large range of variation in MA plans’ coding intensity, from a few MA organizations coding at a lower rate than Medicare FFS, to some reaching 10-20% higher coding intensity than Medicare FFS.
Even though MedPAC projects a downward trend in the percent of MA overpayments caused by coding intensity from 2024 to 2026 (the time period where v28 was being phased in to replace v24), such a decrease is not guaranteed, nor likely, to continue forever. Further, 2025 and 2026 are projected estimates of coding intensity based on estimated impacts,
Upcoding has been slowed down, but it’s likely not yet gone away.
MA markets will likely continue prioritizing the coding arms race in response to v28
Now, the MA market is in the very first year of the complete v28 phase-in. Novel technology investments and adaptive methods are likely to be explored and mastered in response to v28. While v28 has, so far, effectively diminished the easier gains MA plans had previously adapted to achieve, v28 does not fundamentally change the payment structure MA plans are competing on.
Therefore, today, upcoding has not been solved, despite mathematical estimates and hypothetical projections that it could be.
Even with v28, the costs are high, and CMS has taken more steps forward
“Four percent in MA higher payments compared to what would have been paid in Medicare FFS” translated to just $7-10 billion in overpayments in 2018-2019. By comparison, 4% in MA higher payments (in 2026) now amounts to $22 billion annually in higher spending on MA plans. This increase has led to an unprecedented average of over $2,300 in rebate payments per enrollee per year. As the government continues to spend more on Medicare at large, and as more adults age into Medicare and live longer, the amount of money at stake may continue to rise, even if the percentage of overpayment attributed to coding appears to be the same or smaller than previous years.
In tandem, the v28 phase-in and the proposed changes in the CY 2027 Advance Notice could very nearly shutter the financial effects of MA coding intensity. However, in response to comments, it is possible that CMS modifies or chooses not to finalize proposals in the Advance Notice. Even if the policies are finalized, the mere implementation of these changes, however, should not be mistaken for a final resolution in the broader context of MA overpayment.
How can policymakers continue to move the needle to right size MA payment?
The most important thing policymakers can do is to watch diligently to see how the MA market responds before formulating an opinion on the overall impact of v28. Policymakers may consider:
Monitoring how MAOs adapt to v28, rather than relying solely on static projections. Whether coding intensity continues to decline as expected, and for whom, will be key to observe.
Evaluating how smaller MA plans respond to the risk adjustment changes. Competition among smaller MA organizations is an important consideration for CMS, as stated in the RFI released in November 2025. CMS and policymakers should therefore monitor and evaluate how smaller MA organizations respond to the risk adjustment changes and potentially consider policies to ensure policies continue to promote competition.
As MA markets adapt to v28 and (potentially) to the exclusion of diagnoses from unlinked chart reviews, policymakers may consider future legislation and/or regulatory policies to continue improving MA payment accuracy according to updated market evidence and research.
A Policymaker’s Guide to Interpreting Studies that Compare Medicare Advantage and Traditional Medicare Payment
With Medicare spending projected to reach $2 trillion by 2032, getting the cost story right matters. But for policymakers and staff, that is easier said than done. Research comparing Medicare Advantage (MA) and Traditional Medicare (TM) often appears to point in different directions, but the differences often reflect different research method choices, different definitions, and …
With Medicare spending projected to reach $2 trillion by 2032, getting the cost story right matters. But for policymakers and staff, that is easier said than done. Research comparing Medicare Advantage (MA) and Traditional Medicare (TM) often appears to point in different directions, but the differences often reflect different research method choices, different definitions, and different underlying policy questions.
This resource is designed to help policymakers cut through that confusion and interpret studies evaluating MA and TM with a more critical eye.
The guide offers policymakers:
A framework for understanding how researchers define “cost” and “value” differently depending on what they are trying to measure.
A side-by-side comparison of four major 2024–2025 studies to show why they reach different conclusions.
Plain-language explanations of key terms and concepts like risk adjustment, coding intensity, and favorable selection—the technical fault lines that shape this debate.
Nine simple, yet concrete questions to assess whether a new study actually answers the policy question the policymaker hopes to address.
Medicare Advantage Enrollees Weigh In: Five Recommendations to Improve Open Enrollment
This policy brief examines the challenges MA enrollees face during annual open enrollment and outlines five policy recommendations based on the experiences of a 17-member MA Enrollee Advisory Group (AG). While participants valued the benefits offered by MA plans, they consistently described the process of selecting and comparing plans as complex and difficult to navigate. …
This policy brief examines the challenges MA enrollees face during annual open enrollment and outlines five policy recommendations based on the experiences of a 17-member MA Enrollee Advisory Group (AG). While participants valued the benefits offered by MA plans, they consistently described the process of selecting and comparing plans as complex and difficult to navigate.
AG members highlighted five core hurdles:
Overwhelming advertisements and direct-to-consumer sales tactics during open enrollment cause severe informational overload.
Limited awareness of the official Annual Notice of Change prevents enrollees from effectively tracking yearly cost and benefit modifications.
Usability challenges and filtering limitations within the Medicare Plan Finder complicate side-by-side plan comparisons.
Financial transparency gaps and lack of disclosure obscure the neutrality of third-party agent and broker recommendations.
Low public visibility and capacity constraints restrict access to State Health Insurance Assistance Program counselors, despite them serving as the most trusted source of guidance.
Download the policy brief to learn about the five recommendations MA enrollees have for policymakers to improve transparency, strengthen consumer protections, enhance plan comparison tools, and expand access to independent enrollment assistance.
Leveling the Playing Field: Why Smaller Medicare Advantage Plans Are Calling for Payment Reform
In this blog, Carrie Graham and Laura Skopec explore the views of local and regional plans expressed in a 2025 closed-door roundtable convened by Georgetown University’s Medicare Policy Initiative and West Health. Representatives of smaller plans expressed support for several reforms to the MA risk adjustment methodology to rein in aggressive upcoding and to refocus competition on the quality of care, not the volume of diagnoses.
In January 2026, the Centers for Medicare and Medicaid Services (CMS) released a Request for Information (RFI) seeking input on options to modernize Medicare Advantage (MA) payment, specifically recognizing that smaller MA plans may be disadvantaged by the current risk adjustment system. Reducing waste, fraud and abuse in health care spending is a bipartisan priority and a key focus of CMS’s current leadership. At the same time, CMS wants to ensure that smaller, regional MA plans remain competitive and continue to be offered as a viable choice for Medicare beneficiaries.
Originally, the MA program was approved by Congress with the goal of offering a private health plan option that would provide higher-quality care at a lower cost for both beneficiaries and the federal government. Over half of all Medicare beneficiaries now choose to enroll in MA, and they do, on average, accrue lower out of pocket costs and additional benefits. However, analysts estimate the federal government will spend approximately $76 billion more for MA beneficiaries in 2026 compared to those in traditional Medicare – estimated to result in $1.2 trillion in overpayments to MA plans by 2035. These overpayments are cause by both favorable selection (i.e., when MA plans attract enrollees with lower spending than their risk scores would predict), and “upcoding” – when MA plans assign diagnostic codes to enrollees that artificially inflate risk scores. While recent changes to the risk adjustment system have lessened upcoding-related overpayments, the risk adjustment system continues to be scrutinized by Congress, CMS, and mediaoutlets, with a particular focus on the use of in-home health risk assessments and chart reviews to mine higher-paying diagnoses.
Policymakers have taken some steps to reduce MA upcoding and overpayment:
Congress requires CMS to correct for upcoding by imposing a minimum 5.9% coding pattern adjustment across all MA plans.
The V28 CMS-HCC model (implemented beginning in 2024) includes several coding changes specifically intended to reduce and better align payments with true clinical risk.
In March 2025, Senators Cassidy (R-LA) and Merkley (D-OR) introduced the bipartisan No Unreasonable Payments, Coding, or Diagnoses for the Elderly Act (NO UPCODE Act), which would, among other things, exclude diagnoses found through HRAs and chart reviews from risk score calculations.
What are local and regional MA plans, and why do they matter?
The MA market is becoming more concentrated, with 77% of enrollees currently in a plan owned by one of 8 large national MA organizations, and less than a quarter enrolled in one of 150 local or regional MA plans. We define local and regional plans as those with 500,000 or fewer enrollees. Some of these smaller plans are offered only in one market, while others are important players within a larger region. The majority of smaller plans are non-profit, and some focus on specific populations such as those who are dually eligible for Medicare and Medicaid. Smaller plans often have different business models and methods of operation, as well as smaller service areas and fewer financial resources than the larger, national carriers.
As CMS has recognized, smaller local and regional MA plans can provide important choices for beneficiaries. In particular, they may be better able to innovate to meet the needs of their enrollees because of their historic connections to the communities they serve.
How the current MA payment system advantages larger plans
In recent years, as the MA market became more concentrated, certain payment strategies have made it increasingly difficult for smaller plans to compete.
Current risk adjustment rules favor large MA plans that have the resources to invest in more aggressive coding. For example, many plans use health risk assessments conducted in enrollees’ homes to glean additional diagnoses to maximize risk scores and payments. This requires personnel resources for home visits and technology to review charts. Larger, more well-resourced MA plans have the funds to invest in these strategies while smaller plans may not. In fact, large, national MA organizations (MAOs) tend to have the highest additional payments attributed to aggressive coding tactics and are more likely to use those tactics like in-home health risk assessments or chart reviews (though there is variation in coding intensity across both smaller and large regional plans). One MPI roundtable participant described the current incentives to aggressively code as an “arms race,” stating that smaller plans do not have the financial resources to compete with larger MAOs, and that the financial investments in chart reviews and HRAs for upcoding purposes could be better spent on patient care.
The coding pattern adjustment can penalize plans that do not engage in aggressive coding. Congress requires CMS to impose a coding pattern adjustment of at least 5.9% on all MA plans. This adjustment reduces the amount each plan is paid in order to make up for the tendency of MA to code more aggressively compared to traditional Medicare. This across-the-board adjustment does not take into account that there is great variability in the amount of upcoding by plan. For context, although 16 MAOs have an average coding intensity of more than 20%, MedPAC estimates that 15 percent of MA enrollees are in plans that upcode less than the 5.9% adjustment. The blanket coding pattern adjustment not only penalizes MA plans that do not routinely engage in upcoding – it also acts as a financial incentive for plans to invest more in aggressive coding strategies to ensure their risk scores can absorb the 5.9% adjustment. Congress gave CMS the authority to increase the coding pattern adjustment, but it has not done so.
What do local and regional plans say about risk adjustment reform?
Large national plans (and the trade associations that represent them) have generally opposed reforms such as the bipartisan NO UPCODE Act, which would remove some incentives for upcoding. For example, one large trade association argues that reforms to limit overpayment would “harm seniors” because any reduction in payment to MA plans would require plans to reduce benefits or increase costs for enrollees. But in MPI’s 2025 roundtable, attendees from smaller plans said that competition based on aggressive diagnostic coding in MA burns through resources that could otherwise be spent on providing high-quality care. Thus, most roundtable participants supported reforms similar to those recommended by a trade association that represents smaller plans, including reforms that would simplify risk adjustment and reduce financial incentives to aggressively upcode.
While plan representatives at the roundtable were not always united on any particular solutions, several were open to specific options that have been outlined by members of Congress, the administration, MedPAC, and researchers, including the following:
Exploring opportunities to leverage technology, including electronic health records (EHRs) and artificial intelligence (AI). Smaller plan representatives were hopeful that EHR data and AI could be used to reduce reporting burdens while fairly distributing resources among plans. However, no specific proposals were mentioned, and plan representatives noted that the design and operational issues would need to be carefully considered for their impact across the MA market.
Reducing or eliminating the use of in-home health risk assessments (HRAs) for risk adjustment. While most participants emphasized that HRAs are an important tool for identifying beneficiary needs and coordinating care, many felt that the current system – which incentivizes plans to conduct HRAs in order to mine more profitable diagnoses – detracts from the original intent of HRAs as a tool to improve patient care. Some supported reforms that would eliminate the use of HRA-gleaned diagnoses for risk adjustment. One participant suggested that diagnoses from HRAs should only be used in risk adjustment if they required follow-up care. “… discussants were interested in policies that would maintain plans’ ability to capture codes in the home but require confirmation of those diagnoses through a handoff to a doctor and an in-office visit.”
Preventing abuses of chart reviews. While some participants suggested eliminating chart reviews as a source for risk adjustment diagnoses, others noted that small plans with less sophisticated coding technology may still need to use chart reviews to ensure accurate payment. However, smaller plans generally supported requiring diagnoses from chart reviews to be linked to a specific encounter to prevent abuse.
Focusing more federal oversight and audits on MA plans that have a record of upcoding. Many smaller plans were opposed to the CMS proposal to expand annual RADV audits to all plans. Instead, they preferred a policy that would focus on those plans with a history of the highest coding intensity. They argued that undergoing risk adjustment audits imposes higher costs and administrative strain on smaller MA plans, even though smaller plans are less likely to upcode, and audits therefore should be targeted rather than universal.
What does this mean for policymakers considering changes to MA risk adjustment?
There is currently bipartisan support in Congress and the administration for reducing waste, fraud, and abuse in health care. While most MA trade associations generally oppose any increased oversight of the program, smaller plans and their associations may be more open to reforms. These unique views from smaller, regional and local plans could help bolster the growing support for policymakers to reform payment policies.
As debate about potential reforms continues, policymakers in CMS and Congress should bear in mind that changes to the MA payment system may affect smaller, more localized MA plans differently than the larger, national MA plans. Policymakers should proactively seek feedback from smaller plans when considering MA reforms to ensure they are represented amid the typically dominant presence of large MAOs.
Contract Year 2027 Medicare Advantage and Part D Proposed Rule
This presentation highlights key policies in the Contract Year 2027 Medicare Advantage and Part D Proposed Rule. It serves as a resource to contextualize proposals with recent market trends in Medicare Advantage and key administration priorities leading up to the rule. MPI experts lay out proposals within the following key areas in the proposed rule: Read the presentation to learn more …
This presentation highlights key policies in the Contract Year 2027 Medicare Advantage and Part D Proposed Rule. It serves as a resource to contextualize proposals with recent market trends in Medicare Advantage and key administration priorities leading up to the rule.
MPI experts lay out proposals within the following key areas in the proposed rule:
MA marketing proposals
MA risk adjustment proposals
Quality Bonus Payments/Star ratings proposals
CMS Requests for Information
Medicare Part D proposals
Read the presentation to learn more about the key implications of the proposed rule for policymakers and Hill staffers. While not all proposals were finalized in April 2027, it is crucial to understand what was proposed and why for future policymaking, and to predict what changes may be pursued by CMS in the coming years.
Smaller Medicare Advantage Plans: How Do They Compare?
This data brief delivers a comprehensive snapshot comparing roughly 150 smaller MA plan sponsors against the nation’s eight largest companies. The report highlights the structural, geographic, and financial realities of these smaller plan options, illustrating how current rules leave them with less flexibility than their large commercial counterparts. Data shows smaller plans operate with lower …
This data brief delivers a comprehensive snapshot comparing roughly 150 smaller MA plan sponsors against the nation’s eight largest companies. The report highlights the structural, geographic, and financial realities of these smaller plan options, illustrating how current rules leave them with less flexibility than their large commercial counterparts.
Smaller plans command about 22% of total national MA enrollment, with a heavier concentration of members located in counties that feature lower traditional Medicare spending.
Enrollment in smaller plans leans heavily toward non-profit organizations (63% compared to just 10% among the top eight giants) and plans vertically integrated with local health systems that own hospitals.
Smaller plan sponsors focus more on traditional HMO products and integrated Special Needs Plans for beneficiaries with Medicare and Medicaid rather than broad PPO networks or commercial employer-group retiree plans.
Data shows smaller plans operate with lower average risk scores, lower risk-adjusted payments, and higher average Medical Loss Ratios (92.5% vs. 88.7%). Despite these tighter profit margins, many excel in performance, with over 70% of their enrollees in contracts awarded 4 or more stars in the 2026 ratings.
CMS Takes Aim at Upcoding: Ending “Unlinked” Chart Reviews in Medicare Advantage
MPI’s Neil Patil and Carrie Graham explain how unlinked chart reviews currently function within MA risk adjustment, why CMS and federal oversight bodies have raised concerns about their role in upcoding and overpayments, and how the proposal aligns with longstanding recommendations from government oversight bodies and MA payment experts.
On January 26, 2026, the Centers for Medicare & Medicaid Services (CMS) proposed as part of the Calendar Year (CY) 2027 Advance Notice that Medicare Advantage Organizations (MAOs) will no longer be able to submit diagnoses gleaned through “unlinked” chart reviews to bolster their enrollees’ risk scores. CMS considers chart reviews to be “unlinked” if they are done outside of an actual clinical encounter. If finalized, this change is expected to decrease MA payments by 1.53%, or over $7 billion, in 2027 (compared to 2026). This, along with a lower-than-expected increase in payment rates, represents one of the most impactful changes to MA payment in the past decade.
The diagnoses that are used to calculate the risk score and PMPM payment for every MA enrollee come from three different sources:
Encounter data: In each clinical visit (including primary care, hospital visits, or in-home visits), the provider records—or “codes”—all the diagnoses they address during that visit. These codes are then recorded in encounter data, which is later submitted to CMS to inform risk scores.
Health Risk Assessments (HRA): An HRA is a face-to-face assessment of a patient by a clinician to identify problems or diagnoses that were missed during previous visits, and potentially find gaps in care. HRAs are often conducted by third-party vendors hired by MAOs via home or video visits with enrollees, and diagnoses from HRAs are typically reported in an encounter data record.Government oversight bodies have estimated that in home HRAs account for $7.5 billion annually in additional risk adjusted payment to MA plans.
Chart Review Records (CRR): Currently, MA plans can conduct retrospective chart reviews with the purpose of identifying diagnoses that were not recorded in encounter data. MAOs often contract with third-party vendors or use artificial intelligence (AI) to review records and automate the assignment of diagnostic codes. The majority of MAOs review their enrollees’ medical history to identify diagnoses that may have been left off of the claims submitted by the provider.
Linked vs. Unlinked Chart Review Records
Currently, there are two types of CRRs that are submitted by MAOs for payment: linked CRRs and unlinked CRRs. Linked CRRs refer to CRRs with diagnoses that appeared in a previously submitted encounter data record—meaning they were coded by a provider as a diagnosis that was addressed during a clinical visit. Unlinked CRRs are CRRs with diagnoses that do not appear in a separate encounter data record. Thus, they are not associated with a specific service or care.
CMS Proposed this Change to Reduce Overpayment to MA Plans
The original purpose of the MA program was to save Medicare money by leveraging managed care delivery systems to reduce the use of low-value care. However, a January 2026 analysis by the Medicare Payment Advisory Commission (MedPAC) found that MA payments are currently $76 billion above what spending would have been in Traditional Medicare (i.e. Medicare Fee-for-Service). The higher spending in MA is, in part, attributed to a practice called “upcoding,” a term that generally refers to providers or payers billing for services at a higher level of complexity than was actually provided or documented in the file.
Prohibiting the use of diagnoses gleaned from unlinked chart reviews is a step that has been recommended by government oversight bodies and MA payment experts to reduce the impact of upcoding. The Health and Human Services Office of the Inspector General (HHS-OIG), identified the use of CRRs (as well as HRAs) as a major driver of upcoding and overpayment in MA.
A 2019 HHS OIG study found that MAOs almost always used CRRs as a tool to add, rather than delete diagnoses, and that unlinked CRRs resulted in an estimated $2.7 billion in potential overpayments to MAOs in 2017. In its report, the HHS-OIG recommended that CMS reassess the risks and benefits of allowing unlinked CRRs to be used as a source of diagnoses for risk adjustment. CMS concurred with the recommendation and stated the agency would conduct a review of unlinked CRRs to determine whether they should be used as sources of diagnoses for risk adjustment. Nearly 58% of MA contracts submitted unlinked CRRs in 2022, and CMS specifically noted that excluding these unlinked CRRs from risk adjustment “may reduce differences in payment” due to “differential coding across MA organizations.” Ultimately, as part of the CY 2027 Advance Notice, CMS proposed to exclude diagnoses from unlinked CRRs for risk-adjusted payments to MAOs.
Other CMS Policies that could Improve MA Payment Accuracy
There are additional changes proposed in the CY 2027 Advance Notice that may further improve payment accuracy to MAOs:
Version 28 Risk Adjustment Model: The full phase-in of the 2024 MA Risk Adjustment Model (v28) could further reduce overpayment to MA plans. This version, partially implemented in the CY 2024 Rate Announcement, restructured condition categories using the International Classification of Diseases-10 (ICD-10) system. It also removed several diagnoses associated with coding variation from risk-adjusted payments. The v28 model has been phased-in over three years, with the full phase-in beginning in 2026. In January 2026, MedPAC reported that the v28 model reduced coding intensity in recent years, and corresponded with reduced payments, stable supplemental benefits, and high plan availability.
Updated Data Years: CMS is also proposing to calibrate the v28 model using more recent Traditional Medicare data. These updates reflect more up-to-date costs associated with various diseases, conditions, and demographic characteristics.
Exclude Audio-Only Diagnoses: Under the MA program, diagnoses from telehealth visits may be used for risk adjustment if they are from an approved inpatient, outpatient, or professional service. CMS is also proposing to calibrate the v28 model by excluding the underlying Traditional Medicare diagnostic data from audio-only services.
The No UPCODE Act
CMS’s proposal to exclude unlinked CRRs aligns relatively closely to not only HHS-OIG recommendations, but also to bipartisan legislation in Congress. In March 2025, Senators Bill Cassidy (R-LA) and Jeff Merkley (D-OR) re-introduced the No Unreasonable Payments, Coding, or Diagnoses for the Elderly (No UPCODE) Act. The legislation goes further than CMS’s proposal as it would require CMS to exclude diagnoses from both linked and unlinked CRRs as well as HRAs. The Congressional Budget Office estimated the bill could result in $124 billion in savings over 10 years.
After early discussions in the Senate to potentially include provisions of the No UPCODE Act in the 2025 reconciliation package, many Republican senators raised concerns. Additionally, CMS raised some potential operational complexities with identifying and excluding diagnoses from HRAs. However, CMS’s proposal may signal a renewed congressional interest in No UPCODE Act.
Next Steps
Ensuring that MA payments are accurate and that beneficiaries are receiving the care they need is critical to an effective MA program. Policymakers must balance the appropriate use of tools such as HRAs and CRRs to ensure patients receive the care they need, while preventing these tools from being exploited to drive overpayments to MA plans. CMS’s proposal to exclude diagnoses from unlinked CRRs may improve MA payment accuracy and ensure MA plans are paid appropriately for the care provided to beneficiaries. As policymakers consider how to improve MA payment accuracy, they may want to consider proposals to further limit or eliminate the use of HRA and chart review data in risk adjustment.
The comment period on the CY 2027 Advance Notice is open, and all comments must be submitted to CMS by February 25, 2026. The CY 2027 Rate Announcement will be published no later than April 6, 2026.
Apples to Oranges: Including the MA Risk Score Trend in CMS’s Estimates of MA Payments
MPI Health Policy Director Neil Patil breaks down how to evaluate the CMS reported expected average MA payments to plans and what the number might really mean once all factors are accounted for.
On January 26, 2026, the Centers for Medicare & Medicaid Services (CMS) announced, as part of the Calendar Year (CY) 2027 Advance Notice, a proposed 0.09 percent, or over $700 million, payment increase for MA plans in 2027. But inconsistencies in how this amount was reported may underestimate the actual proposed increase in MA payments for 2027.
Each year, the Advance Notice proposes updates to MA and Part D payment policies and the subsequent Rate Announcement, which is statutorily required to be issued by the first Monday in April, finalizes MA and Part D payment policies for the upcoming calendar year. CMS also issues a fact sheet for each Advance Notice and Rate Announcement, which includes a “year-to-year percentage change” table that provides the expected average change in MA payment relative to the previous year.
How this “year-to-year percentage change” table presents the information can influence the public’s perception of the proposed and final MA payment rates. Over the years, CMS has not consistently included projected increases in payment due to increases in MA diagnosis coding and risk scores in the calculation of the final expected average change in MA payment. In this blog, we will break down how to evaluate the presented “year-to-year percentage change,” and what the number might really mean once all factors are accounted for.
CMS’s 0.09 Percent Expected Average Increase in MA Payments for CY 2027 Does Not Include the MA Risk Score Trend of 2.45 Percent
Based on the proposed MA payment policies in the CY 2027 Advance Notice, CMS estimates that MA plans will receive a 0.09 percent average increase, or over $700 million, in MA payments from 2026 to 2027. However, a footnote below this table indicates that this total “does not include an adjustment for underlying coding trend in MA” and “For CY 2027, CMS expects the MA risk scores to increase, on average, by 2.45% due to the underlying coding trend.” This adjustment for the underlying coding trend is referred to as the MA risk score trend, which represents an estimated industry average annual change in risk scores for the upcoming year, and accounts for the average change in population and coding practices across all MA plans. The MA risk score trend is estimated as the average annual change in MA risk scores for MA enrollees over a three-year period calculated using the model(s) proposed for the payment year. It is also important to note that different MA risk adjustment models have resulted in different risk score trends, as evidenced by the lower trend under 2024 MA risk adjustment model (v28). Meaning, this model has resulted in less increases in codes year-over-year than the previous model (v24).
CMS has been Inconsistent in Including the MA Risk Score Trend in its Reported Calculation of the Expected Average Increase in MA Payments
CMS has historically been inconsistent in including the MA risk score trend in the “year-to-year percentage change bottom-line table” which can be found in each Advance Notice and Rate Announcement fact sheet, making it difficult to accurately compare the year-over-year expected percentage change in average MA payments. While the MA risk score trend is not incorporated into the risk adjustment model or benchmarks, CMS typically provides the MA risk score trend in the Advance Notice Fact Sheet and Rate Announcement Fact Sheet as an element for understanding the complete revenue picture for MA organizations in the payment year. In fact, in a 2023 Frequently Asked Questions on the MA 2024 Advance Notice, CMS stated “it is critical that MA plans consider the total impact of all proposed policies and factors in the Advance Notice together, including, for example, the MA risk score trend.”
However, CMS has only included the MA risk score trend as a row in the Advance Notice or Rate Announcement “year-to-year percentage change” table in six of the last twelve Advance Notices/Rate Announcements. In the six years where the MA risk score trend was not included in this table, CMS typically included the MA risk score trend figure as a footnote, with the exception of CY 2022 where CMS did not report the MA risk score trend in its Advance Notice or Rate Announcement fact sheet. This inconsistent approach can make it difficult to accurately assess the expected average change in MA revenue between different calendar years. For instance, CMS reported last year that the expected average change in MA revenue was 5.06 percent from CY 2025 to CY 2026 (which did not include the MA risk score trend), a modest increase from the 3.7 percent increase in the expected average change in MA revenue from CY 2024 to CY 2025 (which did include the MA risk score trend). However, when incorporating the MA risk score trend, the expected average change in MA revenue from CY 2025 to CY 2026 is closer to 7.16 percent, compared to the 3.7 percent increase in the expected average change in MA revenue from CY 2024 to CY 2025. Such inconsistencies in reporting of the top-line number can unintentionally skew stakeholders’ perception of what MA payment will look like compared to the previous year.
Year-to-Year Expected Average Change in MA Revenue when Incorporating the MA Risk Score Trend, Calendar Years 2016-2027
Calendar Year
CMS Reported Expected Average Change in MA Revenue (%)
MA Risk Score Trend
Expected Average Change in MA Revenue, including the MA Risk Score Trend (%)
Sources: Data was compiled as reported in the CMS Advance Notice Fact Sheet and CMS Rate Announcement Fact Sheet, as reported by CMS with respect to each calendar year from 2016 to 2027.
For the CY 2027 Advance Notice, CMS did not include the MA risk score trend in its calculation of the expected average change in MA revenue. When incorporating the MA risk score trend, the expected average change in MA revenue is 2.54 percent, as opposed to the CMS reported figure of 0.09 percent. For CY 2027, the MA risk score trend represents the estimated average annual change in MA risk scores from 2026 to 2027 calculated by using MA risk scores from 2022 to 2024 and using the 2024 CMS-HCC risk adjustment model (v28). We also note that historically, the final Rate Announcement tends to report a higher expected average change in MA revenue, compared to the Advance Notice, largely due to increases in the effective growth rate.
CMS Should Maintain a Consistent Methodology in its Calculation and Reporting of the Expected Average Increase in MA Payments
There has been an ongoing debate regarding whether the MA risk score trend should be included in the calculation of the expected average change in MA revenue. Some have stated that including the trend is “neither supported nor relevant” in the calculation of the expected average change in MA revenue, because the estimate is not part of the benchmark calculation and the agency provides little information on how the figure is calculated. Others, including CMS, have supported the inclusion of the MA risk score trend as a “key factor in evaluating the total level of MA payments” and the exclusion of the MA risk score trend “would underestimate MA payment levels to MA plans.” Ultimately, CMS must determine whether to include the MA risk score trend in its calculation of the expected average change in MA revenue and use a consistent approach each year in calculating this expected average change in MA payments. This will ensure MA plans and the public fully understand the impact of each year’s Advance Notice and Rate Announcement on MA payments.
Response to CMS Request for Information on Future Directions in Medicare Advantage – Risk Adjustment and Quality Bonus Payments
This formal comment letter responds directly to a federal Request for Information regarding the future of the Medicare Advantage program. The letter advocates for structural updates to level the playing field for smaller, local plans that are currently disadvantaged by a system that rewards massive coding infrastructure over cost-effective care.
This formal comment letter responds directly to a federal Request for Information regarding the future of the Medicare Advantage program. The letter advocates for structural updates to level the playing field for smaller, local plans that are currently disadvantaged by a system that rewards massive coding infrastructure over cost-effective care.
The policy recommendations are drawn from a closed-door roundtable with small MAOs managing fewer than 500,000 enrollees alongside an MA Enrollee Advisory Group composed of Medicare beneficiaries.
MPI supports reining in aggressive upcoding by requiring in-office doctor confirmation for in-home diagnoses, targeting RADV audits to plans with disproportionately high coding rates, and introducing a tiered coding intensity adjustment to avoid unfairly penalizing smaller plans.
The letter urges CMS to calibrate Star Rating cutpoints by region to reflect local population differences and to explore a more graduated bonus structure to smooth out steep payment cliff effects.
Participants heavily stressed that major reforms must be phased in gradually to prevent resource-limited local plans from completely withdrawing from the market and worsening insurer consolidation.
[Webinar] How Medicare Beneficiaries Choose Plans — And What the CY 2027 Medicare Advantage Proposed Rule Might Change
On January 14, 2026, Georgetown’s Medicare Policy Initiative in collaboration with Arnold Ventures hosted a webinar, “How Medicare Beneficiaries Choose Plans — And What the CY 2027 Medicare Advantage Proposed Rule Might Change.” Speakers included: • William Cielo, MA enrollee and member of the MPI MA Advisory Group • Carrie Graham, Director of the Medicare …
On January 14, 2026, Georgetown’s Medicare Policy Initiative in collaboration with Arnold Ventures hosted a webinar, “How Medicare Beneficiaries Choose Plans — And What the CY 2027 Medicare Advantage Proposed Rule Might Change.”
Speakers included:
• William Cielo, MA enrollee and member of the MPI MA Advisory Group
• Carrie Graham, Director of the Medicare Policy Initiative (Moderator)
• Jack Hoadley, SHIP Counselor and Research Professor Emeritus at Georgetown University
• Laura Skopec, Health Policy Senior Research Associate, Urban Institute
A Comparison of 2025 Medicare Advantage Legislation
This tool provides a one-stop-shop comparison of 2025 legislation that would impact the Medicare Advantage (MA) program. Made for policymakers, the tool visualizes: Download the tool to learn more about existing legislation, where there may be room for future legislation, and get ideas for what has and has not yet been proposed in various areas …
This tool provides a one-stop-shop comparison of 2025 legislation that would impact the Medicare Advantage (MA) program. Made for policymakers, the tool visualizes:
Which major MA policy domains are addressed by proposed legislation,
An at-a-glance table “checklist” comparison to quickly evaluate potential policy-topic overlaps, and
Easy to understand summaries of each proposal with breakdowns of which key aspects of the bill fall under each MA policy domain.
Download the tool to learn more about existing legislation, where there may be room for future legislation, and get ideas for what has and has not yet been proposed in various areas of MA. As policymakers weigh changes to the MA program, this fact sheet offers clear explanations and evidence-based insights to inform the discussion.
An Uneven Playing Field: Why Smaller Plans Are Calling for Stronger Guardrails on Medicare Advantage Marketing
In a new blog, Laura Skopec and Carrie Graham share findings from a 2025 closed-door roundtable and interviews with 12 local and regional MA plans. The blog highlights how high and variable commissions, opaque third-party marketing practices, and aggressive sales tactics can disadvantage smaller plans, despite their important role in local innovation, community engagement, and beneficiary-centered care.
As Medicare Advantage (MA) enrollment has surged over the past decade, so has spending on marketing and sales activities. The public funds paid to MA plans now support a complex—and lucrative—network of third parties such as call centers, online sites, lead generators, and independent insurance agents and brokers. One report found that $6.9 billion was spent on agent and broker commissions in 2023, up from $2.4 billion in 2018.
Policymakers on both sides of the aisle have expressed concerns about unscrupulous marketing practices that threaten Medicare beneficiaries’ ability to make informed enrollment decisions. As MA has become increasingly dominated by a few large national plans, smaller local and regional MA plans argue that today’s marketing rules favor large, national insurers with the financial resources to dominate the marketing sector.
The Centers for Medicare and Medicaid Services (CMS) has recognized the importance of “leveling the playing field” for smaller MA plans in an increasingly consolidated market. Most recently, the Calendar Year 2027 MA and Part D proposed rule includes a Request for Information (RFI) seeking input on how to improve competition in MA.
This blog reports themes from a 2025 closed-door roundtable with 12 local and regional MA plans to highlight how current marketing rules may disadvantage smaller plans and why many of them support reforms that differ from those favored by large national insurers.
A small number of large national MA plans now dominate the MA market.
Of the over 34 million Medicare Advantage enrollees in 2025, 77% were enrolled in one of 8 large national plans (defined as having over 500,000 enrollees across multiple states and regions). In contrast, less than a quarter were enrolled in one of 150 local and regional MA plans. These smaller, non-national plans typically have different business models, methods of operation, smaller service areas, and fewer financial resources than the larger, national plans.
Local and regional MA plans play an important role in the MA marketplace
Roundtable participants reported that smaller MA plans are better able to innovate to meet the needs of Medicare beneficiaries in their regions because they are more connected to their communities, have established local relationships, and have more local market expertise than larger plans. Their smaller scope also enables quicker decision-making and more efficient implementation of new care models with less bureaucracy than larger plans that must coordinate across numerous markets.
Unscrupulous marketing of MA is a common complaint
During the annual open enrollment period, Medicare beneficiaries are inundated with advertisements, emails, phone calls, direct mailers, and television ads promoting MA plans. And each year, there are beneficiary complaints and reports about the use of unscrupulous marketing practices such as providing misleading or incomplete information to beneficiaries, cold calling beneficiaries, and even enrolling beneficiaries in an MA plan without their consent. Some MA plans have also been accused of discouraging enrollment in less profitable plans by reducing or eliminating agent and broker commissions for those plans. The Department of Justice filed a whistleblower-instigated False Claims Act suit against some large national plans for allegedly providing illegal kickbacks to agents and brokers in exchange for selling their plans. Another recent study found that smaller MA plans are sometimes left out of independent agents and brokers’ books of business entirely.
In 2023, CMS took steps to rein in MA marketing by finalizing a suite of MA marketing regulations aimed at protecting beneficiaries from misleading or aggressive sales practices, including limiting agent and broker compensation, more required disclosures and disclaimers, and more oversight of marketing communications and sales calls. Since then, some of these have been rolled back by CMS or the courts.
What marketing reforms could level the playing field for local and regional MA plans?
Smaller MA plans compete with large national insurers that have far greater financial resources, allowing them to invest heavily in marketing, technology, and analytics. Smaller plans can struggle to keep up with the high advertising spend of large MA plans. Larger plans can also spread high care costs and administrative costs across a larger beneficiary base, keeping their premiums and supplemental benefits more stable.
In the 2025 MPI roundtable with smaller plans, one participant described agent and broker commissions and other marketing costs as, “high, wasteful, and variable.” Some attendees indicated that agent and broker commissions can add 3-8% to costs, a significant investment for small plans. To level the playing field, smaller plans suggested several reforms to marketing, including:
Improve transparency in the third-party marketing industry. Some participants suggested CMS could collect data on the total amount paid to agents and brokers, including all fees, bonuses, and add-ons, to improve transparency into the MA sales market.
Doing more to ensure that third party marketers are providing beneficiaries with complete information about all their plan options. Or at least informing beneficiaries if they are privileging one plan due to financial incentives.If this cannot be ensured, then CMS should consider limiting the presence of third-party marketers in MA.
Consider more stringent caps on agent and broker compensation. Some roundtable participants echoed a recommendation from the Alliance of Community Health Plans (a trade organization that represents many local and regional plans) to cap spending on third-party marketing and strengthen CMS’s penalties for misleading marketing.
Consider standardizing agent and broker payment, including all fees and add-ons, and/or standardizing the level of marketing spending per enrollee across MAOs. However, some roundtable participants were concerned that any cap on total payment could become the new minimum, pricing smaller plans out of the market.
Improve and promote free consumer tools to help beneficiaries compare plans. Tools such as the online Medicare Plan Finder, the Medicare and You handbook, and federally funded State Health Insurance Assistance Programs are sources of free, unbiased information about plan choices. These resources should be continually improved to better help beneficiaries compare plans on factors such as star ratings, health outcomes, provider networks, prior authorization practices, denial rates, and supplemental benefits. Otherstudies and advocacy groups have indicated that the Medicare Plan Finder and other CMS tools are inadequate to meet beneficiaries’ needs for support, and that improvements could help reduce beneficiaries’ reliance on paid agents, brokers, and advertising.
Challenges to regulating MA marketing
While MA is a taxpayer-funded program that requires substantial government oversight to ensure fiscal responsibility and beneficiary safety, policymakers face many challenges to regulation and oversight of plan marketing, including:
Industry pressure to reduce plan burden. Policymakers struggle to balance the need for MA transparency and oversight with a desire to reduce administrative burdens on plans.
Courts have limited CMS’s ability to regulate MA marketing. In 2025, a Texas court ruled that CMS does not have the authority to comprehensively regulate fees and add-ons for agents and brokers under the current rules, so changes to commissions rules would require legislation passed by Congress.
States have no jurisdiction to regulate MA marketing. While state Departments of Insurance have a responsibility to regulate marketing of other health insurance products, they have no authority over MA marketing. In 2025, when a fewstatestried to limit the practice of reducing or eliminating commissions for less profitable plans during open enrollment, some MAOs sued to block any enforcement action. CMS later clarified that states do not have the authority to regulate agent and broker commissions in MA.
The complexity of the current marketing landscape can impede oversight. It can be hard to tease out the relationships and roles of independent agents and brokers versus third-party marketers versus overseas call centers, making it difficult to disentangle various entities and craft targeted policy solutions.
Next steps on MA marketing
Overall, it is not clear that spending more on marketing in MA successfully improves beneficiary decision-making or helps enroll beneficiaries in products that best suit their needs. At MPI’s roundtable, smaller plans argued that focusing on improving the quality of beneficiary care, rather than on aggressive marketing, would be a better use of taxpayer funds.
As with manyotherissues in MA, an important first step is increased transparency. CMS currently has the authority to collect and release more data to inform policy, such as more granular data on marketing spending, as well as total agent and broker payments (not just commission payments). CMS’s recent Request for Information on advancing competition and leveling the playing field through changes to risk adjustment and the Star Ratings system is an important first step, but CMS could also go further to collect information and ideas to help enhance competition through better oversight of marketing practices and stronger enrollment supports.
A Comparison of the Improving Seniors’ Timely Access to Care Act of 2025 and CMS Rulemaking
As Medicare Advantage oversight evolves, how do CMS’s administrative rules compare to Congress’s pending legislative fixes? This policy brief breaks down the key differences between the Improving Seniors Timely Access to Care Act of 2025 and recent CMS regulations governing prior authorization. While regulatory rules establish foundational standards for electronic prior authorization and continuity of care, critical …
As Medicare Advantage oversight evolves, how do CMS’s administrative rules compare to Congress’s pending legislative fixes?
This policy brief breaks down the key differences between the Improving Seniors Timely Access to Care Act of 2025 and recent CMS regulations governing prior authorization. While regulatory rules establish foundational standards for electronic prior authorization and continuity of care, critical gaps remain across AI oversight, provider gold-carding, and plan-level transparency. Read the brief to explore where executive rulemaking ends, why legislative action is required, and what these changing standards mean for enrollees and providers.
A Policymaker’s Guide to Medicare Advantage Payment
Medicare Advantage payment is a complex web, with a multitude of equations, calculations, and risk adjustments weaving together in various ways. As policymakers consider changes to the MA program, it is important to understand how proposed changes can impact the different aspects of the MA payment cycle. Read the guide to learn more about: This guide is designed to help policymakers and …
Medicare Advantage payment is a complex web, with a multitude of equations, calculations, and risk adjustments weaving together in various ways. As policymakers consider changes to the MA program, it is important to understand how proposed changes can impact the different aspects of the MA payment cycle.
Read the guide to learn more about:
How benchmarks are structured and calculated
The Quality Bonus Payment Program
The risk adjustment process
The implications to MA payment from the version 28 risk adjustment model
Timeline of regulatory actions for MA payment and enrollment
This guide is designed to help policymakers and key stakeholders develop more comprehensive and effective policy solutions by referencing this tool to understand where policies may reach functional and technical challenges in operationalization.
In November 2025, the Centers for Medicare & Medicaid Services (CMS) announced the negotiated Medicare prices for the 15 selected Medicare Part D drugs for 2027. In this MPI blog, Health Policy Director Neil Patil examines these drug pricing actions and whether the steps taken under Trump’s second term will actually improve the affordability of prescription drugs.
On November 25, 2025, the Centers for Medicare & Medicaid Services (CMS) announced the negotiated Maximum Fair Prices (MFPs) for the 15 selected Medicare Part D drugs for initial price applicability year 2027 under the Medicare Drug Price Negotiation Program (Negotiation Program). These 15 selected drugs include big-ticket medications, such as the GLP-1 drugs Ozempic and Wegovy, as well as other medications used to treat diabetes, cancer, and other chronic conditions. CMS estimates that these prices will save Medicare about $12 billion in net covered drug costs and will save beneficiaries an estimated $685 million in out-of-pocket costs under the standard Part D benefit.
The Negotiation Program was established by the Inflation Reduction Act of 2022 (IRA), and signed into law by President Joe Biden, but the Trump Administration has attempted to build on President Biden’s IRA through a number of drug pricing policies:
Executive Order: On April 15, 2025, President Trump issued a sweeping executive order, which, among other policies, aims “to improve the Inflation Reduction Act”, implement a payment model “to obtain better value for high-cost prescription drugs”, streamline drug importation processes, and impose tariffs on manufacturers who do not agree to build manufacturing plants in the United States.
TrumpRX: In October, 2025, the Trump Administration launched TrumpRx.gov, a government-operated website where individuals can directly purchase certain drugs—without using insurance–from participating manufacturers at discounted prices.
GLP pricing negotiations: On November 6, 2025, the Trump Administration announced agreements with manufacturers Eli Lilly and Company and Novo Nordisk, to commit to reducing the prices for certain medications, including Ozempic and Wegovy, when purchased through TrumpRx.gov.
New Demonstration Model: On November 6, 2025, Centers for Medicare & Medicaid Innovation (CMMI) announced a new voluntary five-year GENErating cost Reductions fOr U.S. Medicaid (GENEROUS) model, which aims to test an approach, in which manufacturers that participate in the Medicaid Drug Rebate Program (MDRP) provide supplemental rebates to state Medicaid agencies that result in MFN pricing for covered outpatient drugs.
The passage of the Inflation Reduction Act, which included policies to negotiate Medicare drug prices, redesign the Medicare Part D standard benefit, and apply penalties for manufacturers who raise prices at a rate faster than inflation, took major steps to improve drug price affordability for both the federal government and consumers. The proposed Trump-era initiatives appear to a be an effort to continue to reduce drug prices in the United States. However, many remain skeptical on whether true price reductions and affordability will be achieved from these Trump Administration efforts. This blog examines these recent drug pricing actions and whether these actions will improve the affordability of prescription drugs.
TrumpRx
The November 6, 2025 announcement of new Most-Favored Nation (MFN) agreements with Eli Lilly and Novo Nordisk, including steps to make their GLP-1 products more affordable across markets certainly made headlines. Under the new MFN agreements, Ozempic will be priced at $350 per month on TrumpRx.gov, a significant reduction from its list prices of $1000 per month. The Eli Lilly diabetes medication, Trulicity, will be priced at $389 per month, a nearly $600 price reduction in its list price. Both manufacturers also agreed to provide state Medicaid agencies with access to MFN pricing. The companies have also committed to investments to expand U.S. manufacturing capacity, with Eli Lilly committing $27 billion in new U.S. manufacturing investments, and Novo Nordisk committing $10 billion in investments.
It remains unclear the extent to which this announcement will improve the affordability of these medications. First, the MFN-agreed prices are being made directly to consumers, but the price reductions are presented in terms of the medications’ list prices, which are the retail prices of the product set by the manufacturer. Typically, the final price made available is much lower after discounts, rebates, and other price concessions. For instance, one study found that average discounts on brand-name drugs in Medicare Part D were about 40 percent of the retail list price. These discounts are much higher in Medicaid, as one Congressional Budget Office (CBO) study found that the total average Medicaid rebate rate is about 77 percent of the retail list price. There may also be additional rebates that the CBO did not account for in the analysis.
It is also important to note how the prices vary between the Trump Administration’s new MFN agreements and the Medicare-negotiated MFP. In the case of the blood thinning medication Eliquis, the Medicare-negotiated MFP of $231 list price is lower than the MFN-agreed upon direct-to-consumer price of $346 for a 30-day supply of the drug. However, CMS recently announced the negotiated MFP for Ozempic of $274 list price for a 30-day supply, which is higher than the MFN-agreed upon direct-to-consumer price, applicable to Medicare Part D plans, of $245 for a 30-day supply of the drug. Although more information may needed to do direct comparisons, including pricing by National Drug Code.
CMMI GENEROUS Model
The voluntary five-year GENEROUS model will test an approach that result in MFN pricing for covered outpatient drugs, would reduce costs for Medicaid programs. The model is limited to single-source drugs and innovator multiple-source drugs and CMS will calculate MFN pricing based on manufacturer-provided data on the average net international prices for the drug (across the United Kingdom, France, Germany, Italy, Canada, Japan, Denmark, and Switzerland). States would then receive the MFN price through a guaranteed net unit price for each covered outpatient drug under the model, which is set to begin on January 1, 2026 and run through December 31, 2030.
Studies have found that prescription drugs in the United States are significantly higher than in other developed countries, with one study finding overall U.S. prices to be about 2.78 times higher, while brand-name drugs are roughly 3.22 times higher in the U.S. than in other comparable nations. A 2019 House Ways and Means Committee report found that Americans pay as much as 67 times more than consumers in other nations for prescription drugs, even when accounting for rebates.
The GENEROUS model only applies to the Medicaid program, which exhibits the largest percent discounts across federal programs, at least 77 percent of the retail list price. The model could lead to larger savings if it applied to other health programs, such as the Medicare program, given that gross Medicare Part D spending is estimated to total $141 billion in 2026 and has grown significantly over the past decade. The Negotiation Program only applies to anywhere from 10 to 20 high-expenditure Medicare Part B or D drugs each year, and so a model testing international drug pricing mechanisms on drugs not subject to the Negotiation Program, could more drastically improve the affordability of drugs to beneficiaries.
Medicare Drug Price Negotiation
CMS began negotiating the first set of 10 high-expenditure Medicare Part D drugs in 2023 and announced negotiated MFPs for those drugs in August, 2024. This first set of drugs provided list price discounts of anywhere from 38 percent (Imbruvica) to 79 percent (Januvia) of the 2023 list price. CMS estimated that these lower prices, which take effect on January 1, 2026, will save $6 billion annually to the Medicare program, after taking into effect the rebates that are already generating net prices lower than list prices. The negotiated prices would also reduce out-of-pocket spending by about $1.5 billion in 2026.
On November 25, 2025, CMS announced negotiated MFPs for the second round of 15 Medicare Part D drugs selected for negotiation, with price discounts ranging from 38 percent (Austedo) to 84 percent (Janumet) of the 2024 list price. CMS estimated even larger Part D savings for these lower prices, which take effect on January 1, 2027, with Medicare Part D savings of $12 billion annually and an estimated $685 million in out-of-pocket savings to Medicare Part D beneficiaries in 2027.
CMS is required by law to announce the next round of 15 Medicare Part B or Part D drugs subject to price negotiation by February 1, 2026. However, this will be the first round of drugs to incorporate newly enacted restrictions for certain orphan drugs, in accordance with the One Beautiful Bill Act (OBBA), which was signed into law by President Trump on July 4, 2025. The IRA excluded certain orphan drugs that are approved to treat a single rare disease or condition, but the OBBA broadened this exclusion, excluding orphan drugs that are designated for multiple rare diseases or conditions. This could mean drugs like the immunotherapy medication Keytruda may not be selected for negotiation, and the CBO has estimated that this provision will result in about $8.8 billion in higher Medicare spending – reducing savings from the Negotiation Program by almost 10% of the estimated $98.5 billion in savings.
Conclusion
Given the historical trend of prescription drug costs, policymakers need to take significant steps to reduce drug prices. Drug prices in the United States far exceed those of comparable countries, and the extent to which the Trump Administration’s actions will reduce drug costs and increase affordability for beneficiaries is unclear. However, it is clear that the Administration has been taking a multi-faceted approach, including voluntary agreements and tariffs. While there are some finer details to iron out, it could be the case that other approaches, such as the one prescribed in S.1753, the End Price Gouging for Medications Act, which would peg U.S. drug prices, across multiple federal programs, at the lowest retail price available in multiple reference countries, would also lead to savings for both federal programs and consumers. Policymakers and stakeholders should consider exploring additional approaches to reduce drug prices and produce savings for taxpayers and consumers.
CMS Suspends New Medicare Advantage Prior Authorization Transparency Rules Amid Public Concerns About Care Denials
CMS’ decision to suspend enforcement of key prior authorization and utilization management rules in Medicare Advantage will halt a source of information and transparency. In this MPI blog, Research Fellow Ciannah Correa breaks down the rules that CMS has suspended, what PA transparency rules still take effect in 2026, and how these changes may affect enrollee choice and oversight in MA.
On June 16, 2025, the Centers for Medicare & Medicaid Services (CMS) indicated it will not enforce previously finalized regulations related to utilization management (UM) and prior authorization (PA) oversight in Medicare Advantage (MA). Specifically, CMS will not enforce rules requiring MA plans to include health equity expertise in their UM committees, nor rules that would have required MA UM Committees to produce and make public plan-level reports that would identify disparities or inequities in how they were approving or denying care. These regulations aimed to increase transparency around MA plans’ differences in approving care by income, dual eligibility and disability status – they would not have examined racial disparities.
Why this is important?
This is now the second action taken by the Trump administration to move away from MA prior authorization and UM guardrails and oversight. The administration previously declined to finalize requirements for AI oversight, MA plan transparency on PA approval rules, and service-level PA reporting. The suspension of these specific rules further reduces PA/UM transparency, at a time when care denials are causing significant public concern. In this blog, we discuss what has changed, what requirements are still in force for Contract Year (CY) 2026, and what these changes mean for enrollee choice and MA plan oversight.
Utilization Management Committees rely on physicians to represent the interest of their patients
In April 2023, CMS required all MA plans to establish a UM Committee to ensure that PA program consistency with Traditional Medicare coverage requirements. CMS set requirements for the composition of these UM Committees. For example, they must include practicing physicians across a multitude of specialties, at least one who specializes in care for older adults and/or people with disabilities, and at least one independent practicing physician with no conflicts of interest relative to the MA organization. The required range in physician type and expertise was designed to ensure that patients across diagnosis type and age are represented when plans make prior authorization decisions. MA enrollees are not currently required to be included in MA plans’ UM program development process.
CMS suspends enforcement of a rule that required expertise in health equity on UM Committees
In the CY 2025 MA and Part D Final Rule, CMS added a requirement that at least one UM committee member have expertise in health equity. This was defined as a physician with experience conducting studies to identify disparities among different population groups or enacting systems change to achieve equitable and fair care delivery for all MA enrollees in the plan. This requirement was in response to data showing that beneficiaries with certain social risk factors, such as those who were dually eligible for Medicaid, were subject to higher care denials in MA – up to twice the denials received by non-dual enrollees despite, on average, having fewer prior authorization requests. Moreover, dually eligible individuals are more likely to live in poverty and have higher rates of disability than those who are in MA only. Thus, this rule aimed to mitigate such disparities before realizing negative health outcomes by requiring a physician with health equity expertise to advise within the UM Committee. The suspension therefore reduces one mechanism CMS had established to help MA plans assess disparities in their UM practices.
CMS also suspends enforcement of more detailed prior authorization reporting by MA plans
The CY 2025 final rule included a requirement that the above-mentioned UM Committees publish a health equity analysis showing rates of denials and approvals of care by population. These reports would have highlighted any differences in PA practices for select populations: those who are dually eligible, low-income enrollees (identified by their enrollment in the Part D Low Income Subsidy program), and those with disabilities. This requirement would have increased CMS and the public’s visibility into how UM policies are applied to all enrollees and specific populations.
Another requirement of this rule was that the reports would have been more detailed. For example, it would require a summary of PA denials and approvals for items and services broken out instead of aggregated by service category. In addition, this reporting would be at the plan-level, rather than the currently-required aggregated reporting at the contract level. This more granular reporting would have provided local, relevant data for enrollees – rather than contract-level reporting that aggregates metrics across sometimes hundreds of plans from across the country.
Finally, the rule would have required more detailed and stricter posting requirements, ensuring reports were easily accessible and free to view. With these rules no longer enforcing clear, accessible, and standardized reporting of plan-level PA metrics, the extent to which reporting is public is left to each plan’s interpretation. Medicare beneficiaries, agents, counselors and providers will not be able to easily evaluate plans by their demonstrated PA practices, and CMS loses a potential source of data for oversight of MA plan PA practices.
What’s Next?
Some PA transparency requirements are still in effect. Beginning in 2026, MA organizations must publish a list of all items and services that require PA, and eight distinct metrics regarding PA approval and denial rates, including PA decision turnaround times. The approval and denial metrics must be reported on aggregate for all items and services at the contract level, not at the individual plan level. These metrics will help illustrate overall PA performance patterns for the first time, but they won’t reveal local or population-level differences.
Congress is considering taking on these issues.Bipartisan actions to improve UM/PA oversight and transparency, such as the Improving Seniors Timely Access to Care Act have been introduced with the intent of codifying in statute some reporting requirements and even taking first steps towards monitoring artificial intelligence use in PA, among other actions. Additionally, some MA organizations have participated in a voluntary pledge to streamline prior authorization processes, but this pledge does not include plan-level nor population-based reporting.
While the suspension of these PA transparency reporting requirements reduces some administrative burden for MA plans, it also eliminates the first opportunity for CMS, the public and providers to evaluate how prior authorization practices may be different based on enrollee income, Medicaid eligibility and disability. To reiterate, the selected populations face higher health risks when care is denied. MA plans can still choose to examine their PA practices by population, but it is at their discretion and not required to be public, nor would it be required by any existing legislation.
The suspension of these rules eliminates a potential source of information beneficiaries could use to make an informed choice. Medicare beneficiaries currently have few reliable, plan-level sources of information when they are comparing plans during open enrollment. As a result, most consumers currently choose an MA plan based solely on the cost of premiums or supplemental benefits offered, not realizing that plans may differ in the actual care they approve. The suspended requirements maintain a key information gap by removing the reporting of plan-level PA metrics that would have allowed enrollees, their assisters, advocates, researchers, and CMS to compare how PA policies affect populations with specific social risk factors – information that could be particularly relevant for consumers who face greater health risks if denied care.
The contract-level PA reporting that is still required to begin in 2026 will offer some insight into overall PA performance. But without plan-level and population-specific data, the public and CMS will lack accurate information about where, and for whom, denials are concentrated.
Recent headlines suggest the Medicare Advantage (MA) market is in turmoil—with insurers pulling back and a slowing of the MA enrollment boom that we have seen over the last few years. In this new blog, guest blogger Laura Skopec and Director Carrie Graham take a closer look at the data, policy changes, court rulings and competing narratives shaping next year’s MA landscape.
News reports have suggested that the Medicare Advantage (MA) market is in turmoil with MA plans exiting some markets and enrollment poised to fall. For their part, UnitedHealth estimates they will lose 1 million MA enrollees in 2026, and other health insurers have announced plans to exit the MA market entirely. In contrast, the Centers for Medicare & Medicaid Services (CMS) predicted that MA enrollment would remain stable in 2026, despite MA plans projecting a drop in enrollment. Similarly, beneficiaries will still have access to an average of 39 MA plans in 2026, down from 42 in 2025, and there were not significant changes in supplemental benefits between 2025 and 2026.
So which is it – is the MA market stable, or is the sky falling?
The Better Medicare Alliance, a lobbying group for MA plans, has urged Congress and CMS to “reject further cuts or policy changes” to MA, citing the “impact of cuts and regulatory actions during the previous administration.”
What does the evidence say about the MA market?
There are several pieces of evidence that support the MAO’s contention that the MA market is shifting. Data from the National Association of Insurance Commissioners (NAIC) indicates that there has been some financial tightening in the MA market driven by increasing health care use. For example, medical loss ratios in MA rose from 85.6% in the second quarter of 2024 to 86.8% in the second quarter of 2025. However, average gross profit margins in MA increased from $192 per member per month to $194 over this time period and remain higher than any other health insurance market (e.g., commercial insurance, Medicaid, employer-based insurance) that NAIC tracks.
In recent years, CMS has also made adjustments to the quality bonus program, reducing average star ratings and resulting in lawsuits from MAOs over lost revenue. CMS has also adjusted the MA risk adjustment model to reduce opportunities to game the system by coding more diagnoses, further reducing plan revenue. These CMS steps were taken, in part, based on longstanding criticism from MedPAC and others of overpayment to MA plans.
Medicare Advantage plans received regulatory and financial relief in 2025.
For example, CMS had previously projected that MA payment would increase by 3.70 percent on net. However, the Trump administration actually increased payment to an estimated 5.06 percent, more than double what CMS initially proposed. Overall, changes to star ratings and risk adjustment were more than made up for by increases in payment benchmarks and risk scores. MA plans have also won significant victories over CMS in the courts, vacating regulations about agent and broker compensation and risk adjustment audits. A 2024 rule requiring MA plans to notify enrollees about unused supplemental benefits has been delayed, and CMS also decided not to enforce rules requiring MA plans to produce more comprehensive reports on prior authorization and rates of care denials. In addition, while Congress has been considering legislation to rein in MA upcoding and prior authorization, these bills have not been voted on.
Finally, analyses of premiums and benefits for 2026 find that the reality is not as grim as some industry lobbyists have claimed. The average Medicare beneficiary will still have a choice of 39 MA plans in 2026, down from 42 in 2025. Further, CMS indicates that average premiums in MA will fall from $16.40 per month to $14.00 in 2026, and that supplemental benefit offerings will be stable. The Better Medicare Alliance estimates that 59% of MA plans will have $0 premium in 2026, and another analysis found that nearly all MA plans will continue to offer vision, hearing, and dental benefits. Taken together, these facts suggest that the MA market remains robust, and that the “cuts” decried by the MA industry have, in fact, simply been lower-than-desired payment increases, rather than reductions in payment.
What are Medicare beneficiaries experiencing during 2026 Open Enrollment?
As noted above, beneficiaries have somewhat fewer MA plans to choose from during 2026 open enrollment than last year, particularly in some areas of the country. In addition, some large health systems have ended relationships with certain MA plans, so beneficiaries need to look carefully to ensure their doctors are still covered. And in a few counties, particularly in Vermont, MA plans may no longer be available at all.
Reporters and MA plan associations have also pointed to increases in MA out-of-pocket costs and declines in supplemental benefits, but CMS has said supplemental benefit offerings remain stable. One analysis found the share of MA plans offering vision and hearing coverage remained the same between 2025 and 2026 (99% and 97% respectively), though somewhat fewer plans are offering benefits like home-delivered meals or non-emergency transportation in 2026. In addition, an industry analysis found that 59% of MA plans have $0 premiums in 2026.
Predictions of MA market doom have been wrong before
Both the Congressional Budget Office and the CMS Office of the Actuary predicted that the Affordable Care Act’s changes to the MA payment system would result in steep declines in MA enrollment. The opposite occurred. Between 2010 and 2025, MA grew from 25 percent of Medicare enrollment to 54 percent, despite increased financial pressure.
Where might MA be headed?
Some recent research suggests that after a big enrollment boom that resulted in over half of Medicare beneficiaries enrolled in MA in 2025, the predicted slowing in MA enrollment in 2026 is indicative of a market saturation, a point above which growth naturally plateaus. It is not clear whether MA has reached that point at a national level, but MA penetration growth has slowed a bit in recent years. This may not reflect a problem in the MA market, but instead be evidence that MA and traditional Medicare are reaching an equilibrium.
It is likely that the MAOs that can compete on price and benefit packages will continue to generate enrollment and profits in the MA market, while less competitive MAOs will continue to exit their less-profitable markets, adjust benefits, or close their less-profitable plans. In a functioning market, plan entries, exits, and shifts in strategy are a sign of healthy competition, not a sign the market is failing.
The Impact of Health Risk Assessments and Chart Reviews on Medicare Advantage Payment
This fact sheet examines how health risk assessments (HRAs) and retrospective chart reviews have contributed to “upcoding” in MA, driving federal costs, and outlines potential legislative and regulatory remedies.
This fact sheet examines how health risk assessments (HRAs) and retrospective chart reviews have contributed to “upcoding” in MA, driving federal costs, and outlines potential legislative and regulatory remedies.
In 2025, MedPAC estimated that CMS pays 20% more for MA enrollees than similar beneficiaries in Traditional Medicare, generating an estimated annual overpayment of $84 billion.
In 2023, HHS-OIG found that 1.7 million MA enrollees had diagnoses generated strictly through HRAs or chart reviews without any corresponding medical service record, resulting in an estimated$7.5 billion in risk-adjusted payments.
Coding intensity varies heavily among insurers; in 2017, an estimated 20 MA organizations accounted for 54% of risk-adjustment payments linked to chart reviews and HRAs.
Solutions have been proposed, such as the bipartisan No UPCODE Act, which would exclude HRA and chart review diagnoses from risk adjustment). Other proposals include increasing the statutory 5.9% coding intensity adjustment, implementing a tiered coding pattern adjustment tailored to plan behavior, codifying Risk Adjustment Data Validation (RADV) audit program, and expanding audit scopes.
[Event] Medicare Advantage Policies on the Horizon
On October 27, 2025, Georgetown’s Medicare Policy Initiative hosted a briefing titled Medicare Advantage Policies on the Horizon at the McCourt School of Public Policy in Washington, D.C. Speakers included: Access slides from the event here.
On October 27, 2025, Georgetown’s Medicare Policy Initiative hosted a briefing titled Medicare Advantage Policies on the Horizon at the McCourt School of Public Policy in Washington, D.C.
Speakers included:
Ciannah Correa, MPH, Research Fellow, Medicare Policy Initiative
Carrie Graham, PhD, Research Professor and Executive Director, Medicare Policy Initiative (Moderator)
David Meyers, PhD, Assistant Professor of Health Services, Policy, Policy and Practice, Brown University School of Public Health
Neil Patil, MPP, Senior Research Fellow and Policy Director, Medicare Policy Initiative
Jackson Thein, MPH, Director, Waxman Strategies
Namrata Uberoi, PhD, Director, Health Policy, West Health
Assessing Medicare Advantage Quality at the Plan versus Contract Level
Under the Quality Bonus Program, Medicare Advantage (MA) contracts are assigned a star rating of 1 to 5 based on about 40 quality measures. In this MPI Blog, Laura Skopec discusses the advantages and disadvantages of measuring MA quality at the plan and contract level.
In the Medicare Advantage (MA) program, private insurance companies hold one or more contracts with the Centers for Medicare & Medicaid Services (CMS) to provide Medicare benefits. As described in a previous blog, Medicare Advantage Organizations (MAOs) can include multiple, sometimes hundreds, of MA plans in one contract. Under the Quality Bonus Program (QBP), MA contracts are assigned a star rating of 1 to 5 based on about 40 quality measures. Payment bonuses are then applied to MA contracts based on overall star ratings, including boosts to payment benchmarks and higher rebate percentages that allow MAOs to offer lower cost-sharing or more supplemental benefits.
Contract-level quality ratings can create confusion for analysts and policymakers because MA plans are paid based on 1) estimates of care provided by the individual plan (i.e, the plan “bid”), and 2) on quality scores that are averaged across multiple MA plans in the contract. Contract-level quality ratings can also be misleading for Medicare beneficiaries who may not realize that the 5-star rating they see on the Medicare Plan Finder reflects an average across multiple MA plans, not necessarily the quality of the plan they are considering enrolling in.
Pros: Why Does CMS Measure MA Quality at the Contract Level?
The short answer is that MAO contracts tend to have substantial enrollment, providing a large, stable sample size for calculating quality measures.
Ensuring an adequate sample size is particularly important for quality measures that only apply to specific populations of plan members. For example, measures of blood sugar control are only reported for members 75 and younger with diabetes; and measures of osteoporosis management are only reported for women aged 67-85 who have had a bone fracture.
The large sample sizes in MA contracts also mean scores on quality measures are relatively stable year-to-year, avoiding large fluctuations that are unrelated to plan activities. This predictability makes it easier for MAOs to develop long-term quality improvement strategies and helps stabilize payment.
Because bonus payments are used by MAOs to provide supplemental benefits to members, the contract-level quality payments allow MAOs to offer consistent benefit packages across a service area.
Cons: Why Is Contract-Level Quality Measurement a Problem?
Contract-level star ratings may not be meaningful for beneficiaries or reflect their likely experience in their local plan.
Contracts can include plans with a mix of different eligibility rules, such as regular MA plans, special needs plans for people with chronic conditions or who are eligible for Medicaid, and employer-sponsored retiree plans, all combined under a single star rating score.
Calculating star ratings and quality bonuses at the contract level invites MAOs to “game the system.” MAOs have a strong financial incentive to achieve the highest possible star ratings for their contracts, either by improving quality broadly or by selectively combining high- and low-quality plans to maximize ratings. There is evidence that MAOs selectively combine plans into contracts to achieve higher star ratings, undermining the purpose of the program and obscuring true plan performance from beneficiaries.
Should CMS calculate star ratings and quality bonuses at the plan level instead?
CMS has the authority to measure star ratings and apply bonuses at either the contract or the plan level. Measuring quality at the plan level would have several advantages over the contract-level approach. First, plan-level star ratings would be more transparent for beneficiaries and allow them to directly compare the performance of plans they are eligible to enroll in. The plan-level approach would also be harder for MAOs to game by selectively combining plans and contracts, though MAOs would still have the ability to consolidate plans.
Despite its positive attributes, however, there are several drawbacks to plan-level quality measurement. First, some plans may not have sufficient enrollment to calculate some quality measures, particularly those measures focused on specific populations. This may be particularly true for smaller local plans or for plans in rural areas, making it more difficult for beneficiaries to compare among plans based on star ratings. Lower sample sizes would also mean that star ratings and quality bonuses might change more year-to-year, resulting in large swings in plan payment and supplemental benefits. This issue could potentially be addressed by setting a minimum enrollment threshold for plan-level quality measurement wherein plans with lower enrollment would continue to have their quality measured at the contract level. However, it is unclear whether such an approach would create unfair advantages and disadvantages across MAOs based on contract and plan size.
Moving to plan-level star ratings may also require significant changes to the way CMS transforms quality measures into the 5-point star ratings system. Right now, CMS sets national “cut points” for each measure to decide how many stars to award to a contract based on its quality measure performance. Because MA plans generally have a narrower geographic reach than contracts, it may not be fair to set these cut points nationally. Many of the star ratings measures are focused on clinical quality, and measuring quality at the plan level using national cut points may put plans in areas with lower-performing health systems at a financial disadvantage relative to plans in areas with higher-performing health systems. This problem could be addressed by setting cutpoints at the local level, however.
Are there other alternatives to plan or contract level quality measurement that should be considered?
MedPAC, researchers, and local and regional MAOs have suggested several alternatives to plan- or contract-level quality measurement that could improve transparency for beneficiaries and better incentivize MAOs to improve the quality of their products.
First, CMS could calculate star ratings for MAOs or parent organizations (e.g., United Healthcare) at the local level, such as by core-based statistical areas or metropolitan statistical areas. This approach, recommended by MedPAC, would provide beneficiaries with comparisons among MAOs in their market, rather than among contracts that may span multiple states or include plans they may not be eligible for. Setting cut points at a regional level would also better control for regional differences in beneficiary needs and practice patterns, encouraging competition for higher quality within markets that takes into account market-specific conditions. MedPAC has similarly recommended adjusting MA plan payment and quality measurement approaches to use multi-county service areas, like Hospital Service Areas or Metropolitan Statistical Areas, to ensure MAOs can not pick and choose the counties they operate in to gain higher quality scores or avoid beneficiaries with higher health care needs.
Other recommendations focus on streamlining the star rating system to include fewer measures. One association of local and regional MAOs suggested removing process measures for which many contracts already receive high scores from the star ratings system. Similarly, a roundtable of small and mid-size MAOs suggested focusing more narrowly on measures that are important for beneficiary shopping, such as member satisfaction and disenrollment rates. Alternatively, MedPAC has recommended replacing the QBP with a system of bonuses and penalties based on performance on a few population health measures. Finally, researchers have suggested limiting the QBP to small bonuses for exceptional performance on well-documented measures like prevention, combined with new incentives like quality improvement grants.
Proposals to measure quality at the local level could be combined with streamlining star ratings measures to help address any issues that arise with sample size. Further, setting regional cutpoints would enhance local competition by encouraging MAOs to focus on quality at a level closer to where enrollees live, rather than on strategically combining contracts across regions and states.
Implications of measuring Medicare Advantage quality at the contract level: What that means for beneficiary choices and plan payments
Currently, CMS measures Medicare Advantage quality at the contract level rather than the plan level. In this MPI blog, Rachel Schmidt outlines problems associated with measuring MA quality at the contract level and the implications for beneficiary choices and plan payments.
With more than half of Medicare beneficiaries now enrolled in Medicare Advantage (MA), the federal government has a responsibility to make sure beneficiaries have the information they need to make informed choices when looking at their MA plan options. More than ever, federal policy makers also bear responsibility for ensuring that Medicare payments to the private insurers who run MA plans (called Medicare Advantage Organizations—or MAOs) are appropriate. Currently, however, CMS measures quality at the contract level rather than the plan level. Because MAO contracts can include many individual plans, contract-level reporting (which reflects an average across all plans in the contract) can make it harder for beneficiaries to compare how plans might work for them and harder for the Medicare program to reward plans that are truly of higher quality.
Contracts typically include more than one plan
Before allowing an MA plan to begin offering Medicare benefits, CMS must approve a contract with the MAO in which it agrees to provide the same types of benefits as are offered in traditional Medicare and follow applicable laws and regulations. MAOs can have more than one contract with CMS, and each contract typically includes more than one MA plan.
Most MA plans operate at the county level
Nearly all MA enrollees are in what CMS calls local coordinated care plans, in which the MAO selects the counties in which it wants to operate. This is different from regional coordinated care plans in MA and from stand-alone prescription drug plans in Medicare Part D. In those latter types, sponsors must offer their plans across an entire designated region that includes one or more states.
Not all MAOs can enter or exit county markets easily. For example, an MAO that is affiliated with a local or regional integrated health system may only operate MA plans within close proximity to its hospitals, facilities, and providers. In contrast, many of the largest MAOs set up networks of unaffiliated hospitals and physician offices under contract. If a plan in a county is not profitable, these types of MAOs may choose to exit that market and their enrollees must subsequently find a new MA plan or switch to traditional Medicare. Similarly, large MAOs may expand more nimbly than local or regional MAOs into counties that they believe are growing and will be profitable.
There are big differences among MAOs in the structure of their contracts and plans
In July 2025, 163 MAOs had one or more MA plans in the 50 states and the District of Columbia. Of those organizations, 77 (47%) held just one contract with CMS, and those contracts covered 309 plans (6% of all plans), for an average of about 4 plans per contract (see Table 1). Combined, those 77 MAOs had 1.2 million enrollees, or just 3% of total enrollment in MA local coordinated care plans. Competing with those smaller entities are some of the largest MAOs that have dozens of contracts and hundreds of plans. For example, the 3 MAOs with the most contracts with CMS each had 41 contracts or more. Combined, those contracts included 1,564 plans (30% of all plans) and 13.2 million enrollees (38% of total enrollment).
Table 1. Distribution of Medicare Advantage contracts, plans, and enrollment among local coordinated care plans, July 2025
Number of MA contracts per MAO
Number of MAOs
Share of MAOs
Number of plans
Share of plans
Enrollees(In millions)
Share of enrollment
1
77
47%
309
6%
1.2
3%
2 to 5
65
40%
842
16%
4.4
13%
6 to 10
12
7%
475
9%
4.6
13%
11 to 40
6
4%
1,976
38%
11.2
32%
41 or more
3
2%
1,564
30%
13.2
38%
Total of 651
163
100%
5,166
100%*
34.5*
100%*
Source: MPI based on CMS July 2025 enrollment data for local coordinated care plans. Includes special needs plans, employer-group plans, and plans open to all beneficiaries. Excludes U.S. territories and plans with fewer than 10 enrollees.
* Sums may not total due to rounding.
For some of the largest MAOs, a single contract can include hundreds of plans, encompassing not only those open to all Medicare beneficiaries, but also others in which enrollment is limited to categories of beneficiaries such as retirees of certain employers and individuals eligible for special needs plans. Plans under the same contract do not necessarily operate in the same geographic region and some even span across all states. As examples, Table 2 shows the six MA contracts that, as of July 2025, had 1 million or more enrollees. (Note that this is just a subset of these MAOs’ contracts, plans, and enrollment.) The largest MA contract, Humana’s H5216, includes 271 plans that operate in 49 states plus the District of Columbia with, collectively, 2.71 million enrollees. Humana, UnitedHealth Group, Kaiser Permanente, and CVS Health each have at least one contract with 1 million or more enrollees.
Table 2. Medicare Advantage contracts with 1 million or more enrollees, July 2025
Medicare Advantage Organization
Contract number
Number of plans within the contract
Number of states and the District of Columbia covered by the contract
Number of MA enrollees(In millions)
Humana
H5216
271
50
2.71
UnitedHealth Group
H2001
136
51
2.57
Kaiser Permanente
H0524
37
1
1.64
CVS Health
H5522
20
51
1.40
UnitedHealth Group
H5253
116
18
1.13
CVS Health
H5521
244
34
1.08
Source: MPI based on CMS July 2025 enrollment data for local coordinated care plans. Includes special needs plans, employer-group plans, and plans open to all beneficiaries. Excludes U.S. territories and plans with fewer than 10 enrollees.
CMS evaluates MA quality at the contract level, not the plan level
The MA program evaluates and rewards quality via the star-ratings system which combines a basket of measures that CMS uses to assign ratings of 1 to 5 stars (poor to excellent). Star ratings are intended both to help beneficiaries make informed choices among their plans options and to reward higher quality plans through the MA payment system.
However, CMS evaluates star ratings at the contract level, not the plan level, and each plan that falls under the same contract receives that same star rating. This is one important reason that the Medicare Payment Advisory Commission and other analysts have said that the star-ratings system is not a reliable basis for evaluating quality across MA plans. When beneficiaries look at MA star ratings on Medicare’s Plan Finder tool to help them select among their options, they do not necessarily get an accurate depiction of the quality of some plans in their local area.
Evaluating quality at the contract level may also hinder the ability of MAOs that have relatively few contracts and plans to compete with larger plan sponsors. Under MA’s star-rating system, plans that receive star ratings of 4.0 or higher qualify for quality bonuses that boost their payment benchmarks. Plans with higher star ratings also receive a higher rebate percentage as part of their payment, which they can use to attract enrollees through lower out-of-pocket costs or supplemental benefits. However, observers have suggested that star ratings can be manipulated; large MAOs can group high-performing plans with plans from low-performing areas, with the average quality score obscuring the true performance in low-performing areas. This can lead to higher MA payments that do not fully reflect plan quality in some areas and can potentially mislead enrollees shopping for plans in low-performing areas.
This post outlines problems associated with measuring MA quality at the contract level. In an upcoming blog, we will describe policy options for improving how plans and contracts are used in quality measurement and MA payment.
Reforms to Medicare Advantage: Perspectives of Local and Regional Plans
This white paper synthesizes findings from semi-structured interviews and a closed-door roundtable conducted in 2025 with executives from 12 small and midsize Medicare Advantage Organizations (MAOs)—defined as parent organizations with total MA enrollment under 500,000. The report captures the unique operational challenges, market perspectives, and policy reform preferences of local and regional plans, whose viewpoints …
This white paper synthesizes findings from semi-structured interviews and a closed-door roundtable conducted in 2025 with executives from 12 small and midsize Medicare Advantage Organizations (MAOs)—defined as parent organizations with total MA enrollment under 500,000. The report captures the unique operational challenges, market perspectives, and policy reform preferences of local and regional plans, whose viewpoints are frequently overlooked in federal policy debates.
Takeaways:
Participating plans broadly agreed that current MA spending trends are unsustainable. They supported shifting policy incentives away from revenue-generating activities with low clinical value (such as aggressively capturing diagnosis codes) toward care coordination and member service.
Current policies favor the largest national MAOs. Large insurers can balance profitability across states, leverage vertical integration, and outspend smaller plans on marketing and IT infrastructure.
Major policy overhauls must be phased in gradually to prevent unintended operational shocks that could force smaller plans to withdraw from local markets, accelerating industry consolidation.
Policymakers should avoid piecemeal, uncoordinated updates and establish a unified roadmap linking risk adjustment, county benchmark adjustments, and quality incentives.
Download the white paper to learn more about policy recommendations covering: risk adjustment, Star ratings/Quality bonus payments, MA Marketing, Supplemental benefits, and prior authorization.
[Event] What’s Next for Prior Authorization in Medicare Advantage
On September 18, 2025, Georgetown’s Medicare Policy Initiative hosted a briefing titled What’s Next for Prior Authorization in Medicare Advantage at the Capitol Visitor Center in Washington, D.C. Speakers included: View the slides from the event here.
On September 18, 2025, Georgetown’s Medicare Policy Initiative hosted a briefing titled What’s Next for Prior Authorization in Medicare Advantage at the Capitol Visitor Center in Washington, D.C.
Speakers included:
Rodrigo Cerdá, M.D., MPH, Senior Vice President, Health Services, and Chief Medical Officer, Independence Blue Cross
Jeannie Fuglesten Biniek, PhD, Associate Director, Program on Medicare Policy, KFF
Carrie Graham, PhD, MGS, Research Professor and Executive Director, Medicare Policy Initiative (Moderator)
Neil Patil, MPP, Senior Research Fellow and Policy Director, Medicare Policy Initiative
Namrata Uberoi, PhD, MPH, Director, Health Policy, West Health
The Medicare Policy Initiative at Georgetown University is thrilled to welcome Ciannah Correa, MPH as our newest Research Fellow. Ciannah will support policymakers with research, policy analysis, and technical assistance on issues related to Medicare Advantage and Part D. Prior to joining CHIR, Ciannah was a Fellow at the Centers for Medicare & Medicaid Services Innovation Center (CMMI), where she provided technical assistance to Medicare Advantage plans participating in the Value-Based Insurance Design (VBID) model. At CMMI, she worked in the Division of Health Plan Innovation, with a primary focus on addressing Medicare Advantage issues. Ciannah has also held roles as a research assistant at KFF’s Program on Medicare, a data and performance analyst at the Patient Access Collaborative, and a public health research advocate at AIDS Healthcare Foundation. Ciannah holds a Master of Public Health in Health Policy and Management from Emory University’s Rollins School of Public Health, and a Bachelor of Arts in Molecular Biology from Pomona College.
The Medicare Policy Initiative is part of the Georgetown University McCourt School of Public Policy’s Center on Health Insurance Reform (CHIR). The Medicare Policy Initiative (MPI) is shining a light on how Medicare and the Medicare Advantage program can be strengthened so that seniors and taxpayers can get the best possible care and value for their money. This new initiative at CHIR will be doing rapid turnaround policy analysis and provide technical assistance on issues related to Medicare Advantage payment, coverage, and costs.
Artificial Intelligence in Medicare Advantage—Opportunities and Risks
This white paper synthesizes findings from semi-structured interviews and a closed-door roundtable conducted in 2025 with executives from 12 small and midsize Medicare Advantage Organizations (MAOs)—defined as parent organizations with total MA enrollment under 500,000. The report captures the unique operational challenges, market perspectives, and policy reform preferences of local and regional plans, whose viewpoints are frequently overlooked in …
This white paper synthesizes findings from semi-structured interviews and a closed-door roundtable conducted in 2025 with executives from 12 small and midsize Medicare Advantage Organizations (MAOs)—defined as parent organizations with total MA enrollment under 500,000. The report captures the unique operational challenges, market perspectives, and policy reform preferences of local and regional plans, whose viewpoints are frequently overlooked in federal policy debates.
Takeaways:
Participating plans broadly agreed that current MA spending trends are unsustainable. They supported shifting policy incentives away from revenue-generating activities with low clinical value (such as aggressively capturing diagnosis codes) toward care coordination and member service.
Current policies favor the largest national MAOs. Large insurers can balance profitability across states, leverage vertical integration, and outspend smaller plans on marketing and IT infrastructure.
Major policy overhauls must be phased in gradually to prevent unintended operational shocks that could force smaller plans to withdraw from local markets, accelerating industry consolidation.
Policymakers should avoid piecemeal, uncoordinated updates and establish a unified roadmap linking risk adjustment, county benchmark adjustments, and quality incentives.
Download the white paper to learn more about policy recommendations covering: risk adjustment, Star ratings/Quality bonus payments, MA Marketing, Supplemental benefits, and prior authorization.
New CMS WISeR Model Revives Concerns of Prior Authorization and Artificial Intelligence
In this MPI blog by Neil Patil and Jack Hoadley, we take lessons learned from prior authorization in Medicare Advantage and raise questions for policymakers and stakeholders to ensure Medicare beneficiaries receive appropriate access to timely benefits under this new model.
In June, the Centers for Medicare & Medicaid Services (CMS) announced a new six-year Innovation Center model called the Wasteful and Inappropriate Service Reduction (WISeR) Model. The model establishes new prior authorization requirements for a subset of items and services in Traditional Medicare. Under the model, CMS will partner with companies with experience managing prior authorization processes, including either utilization management contractors, or Medicare Advantage (MA) plans who can apply to be model participants.
WISeR will test the use of enhanced technologies, including artificial intelligence (AI), for prior authorizations on the designated services, beginning on January 1, 2026, in select states. The services are those that CMS has determined may pose patient safety concerns and may involve prior reports of fraud, waste, and abuse. CMS officials noted, during a public webinar, that the model’s subset of services represented $1.9-5.8 billion in spending on low-value care in 2022.
The proposed initiative is a major shift, as most traditional Medicare benefits do not require prior authorization. However, nearly all MA plans require prior authorization for some services. There is widespread recognition that prior authorization can be effective in reducing unnecessary, duplicate, harmful or “low-value” care, where the harms or costs outweigh the benefit. Conversely, prior authorization can result in denials of or delays in necessary and even critical care, as well as lead to costly out-of-pocket medical expenses when a patients receive services that are denied by their health plans after the fact. This blog takes lessons learned from use of prior authorization in MA and applies them to the new WISeR model.
Potential for Delays or Denials of Appropriate Care
Some MA plans have been criticized for inappropriately using prior authorization to delay or deny care. This has resulted in MA enrollees not receiving basic Medicare benefits to which they are entitled. In recent years, CMS has made regulatory changes to alleviate these issues, including clarifying that MA plans must cover the same benefits as traditional Medicare and setting guardrails on plans’ internal clinical decision making.
It remains unclear if these new requirements will reduce inappropriate use of prior authorization by MA plans. CMS plans to monitor WISeR model participants and measure performance based on metrics, including the accuracy and promptness of prior authorization decisions, providers’ experience with the process, and impacts on quality of care for beneficiaries. The CMS monitoring strategy will also follow principles aimed at protecting beneficiaries from harm and ensuring compliance with applicable Medicare regulations. CMS has posted the preliminary list of items and services subject to prior authorization under the model, but it is not clear how CMS determined that the services are deemed as low-value.
Policymakers and stakeholders should consider key questions to ensure Medicare beneficiaries receive appropriate access to timely benefits under the WISeR model:
How will CMS ensure that model participants comply with national coverage determinations, local coverage determinations, and general Medicare coverage and benefit conditions?
Will quality measures adequately assess model participant performance?
Will continuity of care requirements apply under the WISeR model?
MA regulations require a 90-day transition that prohibits prior authorizations for new MA enrollees undergoing active treatment
Does the WISeR model list of services accurately capture the appropriate subset of “low-value” services?
Policymakers should review other studies of low-value care, including a recent Medicare Payment Advisory Commission (MedPAC) report that lists potential low-value services.
Beneficiary Protections and Appeals Rights
Medicare Advantage has a set of disclosure requirements and appeals rights to ensure that use of prior authorization by MA plans is managed in a way that protects plan enrollees. In 2023, 11.7 percent of care denials were appealed by MA enrollees and nearly 82 percent of appeals resulted in a decision that was favorable to the enrollee.
While CMS notes that the WISeR model would maintain applicable appeal rights for beneficiaries, it is unclear if MA regulations around disclosure requirements or appeal rights would apply to MA. For instance, will MA regulations require a 90-day transition, which prohibits prior authorizations for new MA enrollees undergoing active treatment, apply to Medicare beneficiaries under the model? Policymakers and stakeholders should consider whether adequate safeguards are in place so beneficiaries understand why a service is denied and are aware of their appeal rights.
Potential for Provider Burden and Providers Exiting Traditional Medicare
Studiesshow that prior authorization and the need to support appeals make administrative burdens in MA far higher than in traditional Medicare. In one study, 90 percent of medical group practices reported that prior authorization was very or extremely burdensome—a contributing factor to increasing exits of providers and health systems from MA contracts.
Policymakers and stakeholders should consider key factors to ensure that the WISeR model does not lead to greater provider frustration from administrative burdens:
Policymakers and stakeholders should consider key issues to ensure that enhanced technologies and AI under the WISeR model are not used inappropriately:
Will there be adequate guardrails on use of AI to make decisions?
Will a clinician make the final decision if the prior authorization is denied, similar to current MA regulations?
How will CMS ensure that underlying AI algorithms used in the model ensure equitable coverage and consider beneficiaries’ individual circumstances, such as required under current MA regulations?
How will CMS ensure that the AI algorithms used in the model are transparent for beneficiaries and stakeholders?
Conclusion
Given the proliferation of prior authorization in MA, there are many factors that CMS, policymakers, and stakeholders should consider as the WISeR model establishes new prior authorization requirements in traditional Medicare—including potential denials and delays of care, beneficiary awareness, appeals rights, provider burden, and AI concerns. Since MA plans may be selected as model participants, considerations should also include whether their participation is a conflict of interest, given that MA plans could benefit if more traditional Medicare beneficiaries are denied services. Transparency may be one way CMS could alleviate these issues, including by publicly reporting prior authorization metrics under the program, similar to the requirements in MA, as well as publishing the list of model participants.
Editor’s Note (Update – August 2025):
Since the publication of this post, CMS has released a WISeR Model Frequently Asked Questions document that clarifies some of the questions raised in this blog. Key clarifications from CMS include additional information on how services were selected, beneficiary protections and appeal rights, oversight of the model, as well as the prior authorization decision timeframes under the model. Additionally, in late July, Reps. Alexandria Ocasio-Cortez (NY-14) and Lloyd Doggett (TX-37), along with 40 colleagues, sent a letter to CMS urging the agency to halt implementation of the WISeR model. The letter acknowledged the cost-saving intentions of the model, but vocalized concern over the use of for-profit companies as model participants and lessons learned from the inappropriate use of prior authorization in MA.
Improving Beneficiaries’ Ability to Make Informed Medicare Choices
This fact sheet analyzes five structural challenges that hinder Medicare beneficiaries from making fully informed plan selections and reviews policy options to reduce consumer confusion. Download the fact sheet to learn more about policy options to address these issues, such as: out-of-pocket caps to Traditional Medicare, enacting guaranteed issue rights for Medigap, standardizing MA plan …
This fact sheet analyzes five structural challenges that hinder Medicare beneficiaries from making fully informed plan selections and reviews policy options to reduce consumer confusion.
Beneficiaries often have difficulty comparing the flexibility of Traditional Medicare with the lower cost, but more restricted and managed Medicare Advantage plans.
Beneficiaries who join MA often lose guaranteed issue rights for Medigap policies, making it difficult or unaffordable to switch back to Traditional Medicare later.
In 2025, beneficiaries faced an average of 42 MA options locally, causing choice overload and reducing active plan reviews.
It is difficult to find data regarding actual out-of-pocket costs, accurate provider networks (“ghost networks”), utilization management criteria, and true supplemental benefit scopes.
High reliance on brokers whose commission structures financially incentivize enrolling beneficiaries in MA over Traditional Medicare.
Download the fact sheet to learn more about policy options to address these issues, such as: out-of-pocket caps to Traditional Medicare, enacting guaranteed issue rights for Medigap, standardizing MA plan options, enforcing accurate provider directories, and expanding funding for unbiased State Health Insurance Assistance Program (SHIP) counselors.
Medicare Advantage Whistleblower Lawsuit Alleges Insurer and Broker Misconduct
This Health Affairs Forefront piece by MPI’s Neil Patil and Carrie Graham analyzes a major federal False Claims Act lawsuit involving leading Medicare Advantage Organizations (MAOs) and large insurance brokerages. The suit alleges: The lawsuit underscores the vital role of internal whistleblowers and DOJ intervention in policing fraud within Medicare Advantage. It also brings renewed …
This Health Affairs Forefront piece by MPI’s Neil Patil and Carrie Graham analyzes a major federal False Claims Act lawsuit involving leading Medicare Advantage Organizations (MAOs) and large insurance brokerages. The suit alleges:
Between 2016 and 2021, major MAOs (including Aetna, Humana, Anthem, WellCare, and Devoted Health) allegedly paid hundreds of millions of dollars to broker firms (such as eHealth, GoHealth, and SelectQuote) to drive enrollments into their plans.
While brokers marketed themselves to consumers as “unbiased” and “carrier-agnostic,” they allegedly steered seniors toward the plans paying the highest financial incentives, regardless of whether those plans best met the beneficiaries’ needs.
To disguise these kickbacks, the payments were labeled as reimbursements for “administrative services,” “marketing,” or customer service.
Certain insurers pressured brokers to limit or suppress enrollments of individuals under age 65 who qualify for Medicare due to disabilities, as this population was viewed as more costly to cover.
Brokers allegedly complied by turning away or suppressing referrals for disabled beneficiaries, violating federal anti-discrimination and enrollment rules.
The lawsuit underscores the vital role of internal whistleblowers and DOJ intervention in policing fraud within Medicare Advantage. It also brings renewed scrutiny to how broker incentives distort consumer choice, harm vulnerable populations (such as beneficiaries with disabilities), and generate substantial costs for federal healthcare programs.
[Webinar] Medicare Advantage Payment and Opportunities for Cost Containment
On May 2, 2025, The Georgetown University Center on Health Insurance Reforms (CHIR) Medicare Policy Initiative and The Brown University Center for Advancing Health Policy through Research (CAHPR) hosted a virtual briefing exploring the complexities of Medicare Advantage (MA) payment issues and strategies to curb overpayments. As MA enrollment grows, policymakers are weighing how to …
On May 2, 2025, The Georgetown University Center on Health Insurance Reforms (CHIR) Medicare Policy Initiative and The Brown University Center for Advancing Health Policy through Research (CAHPR) hosted a virtual briefing exploring the complexities of Medicare Advantage (MA) payment issues and strategies to curb overpayments. As MA enrollment grows, policymakers are weighing how to manage costs while ensuring access and quality. Legislative and regulatory strategies to address overpayments in MA are a key focus, with ongoing discussions on how to balance program incentives, control federal spending, and ensure equitable care for beneficiaries.
Featured speakers included: • Andrew Ryan, PhD, Director, CAHPR • Carrie Graham, PhD, Research Professor and Executive Director of the Medicare Policy Initiative, CHIR • David Meyers, PhD, MPH, Associate Director, CAHPR • Neil Patil, MPP, Senior Research Fellow and Policy Director of the Medicare Policy Initiative, CHIR • Rachel Schmidt, PhD, Research Professor, CHIR • Hayden Rooke-Ley, Health Law and Policy Fellow, Brown University School of Public Health
SHIPs Provide a Critical Service for Medicare Beneficiaries
The authors have spent the majority of their careers conducting research and advising federal policymakers on improvements to the Medicare program. They also volunteer directly with Medicare beneficiaries through their counties’ State Health Insurance Assistance Program (SHIP) – a free service where consumers can call for unbiased assistance choosing among Medicare options. In this blog series the authors …
The authors have spent the majority of their careers conducting research and advising federal policymakers on improvements to the Medicare program. They also volunteer directly with Medicare beneficiaries through their counties’ State Health Insurance Assistance Program (SHIP) – a free service where consumers can call for unbiased assistance choosing among Medicare options. In this blog series the authors share thoughts on the role SHIPs play in counseling beneficiaries. The authors thank Madeline McBride, who was a George E. Richmond Fellow at the Center on Health Insurance Reforms (CHIR) at Georgetown University’s McCourt School of Public Policy, for valuable research for this post.
In April, a draft of potential spending changes proposed by the Office of Management and Budget for the Department of Health and Human Services (DHHS) budget was leaked. The draft detailed significant budget cuts and agency restructuring, including the elimination of more than $55 million in discretionary funding for the State Health Insurance Assistance Program (SHIP). The SHIP program was created by Congress in 1990 to provide free, impartial information, counseling, and other forms of assistance to current and future Medicare beneficiaries. Consumers can call their local program for help choosing among the complex array of Medicare options and for navigating the Medicare program more generally.
Our perspective on SHIPs reflects professional careers working on Medicare policy, further informed by our more recent experiences as volunteer SHIP counselors. Spending part of a day each week talking to current Medicare beneficiaries or those about to be eligible for the program has given us rich insights into both the value of Medicare and the program’s complexity. SHIP counseling sessions can be lifelines to seniors and those with disabilities who are confused or stymied about how to enroll, whether to enroll in traditional Medicare or Medicare Advantage (MA), which drug plan to select, whether they can qualify for financial help in paying for their health care or their medications, or how to navigate the appeals process. Counselors also educate beneficiaries about fraud and abuse.
The value of SHIP is especially obvious when individuals eligible for Medicare are trying to decide among traditional Medicare, Medigap plans, MA plans, and Medicare Part D drug plans. SHIP counselors are vital resources, especially in an environment saturated with aggressive insurance company marketing and insurance brokers who may be giving advice in line with their personal financial motivations rather than a beneficiary’s best interests.
Federal SHIP funding is distributed to states by the Administration for Community Living (ACL), an agency within DHHS that has been designated for elimination in the proposed DHHS reorganization. ACL allocates grants to states, which in turn support more than 2,000 community-based organizations that administer the program locally. Many states have branded their programs with state-specific names, such as the Virginia Insurance Counseling and Assistance Program (VICAP). Last year, state grants averaged $945,665; in some cases, funding is bolstered by additional state dollars. Between April 2022 and March 2023, around 11,500 SHIP counselors, half of whom were volunteers, provided community outreach and education to over 2.6 million people, and individual assistance to over 1.65 million Medicare-eligible individuals and their caregivers. SHIP counseling calls vary widely from quick answers for basic questions to detailed counseling sessions; call lengths averaged 33 minutes in recent years, representative of the personalized and detailed guidance that these counselors provide.
Not all SHIP counselors have spent their careers working on Medicare like we have. Other counselors may have worked in other parts of the health care system where they learned a lot about Medicare. Still others were educators, social workers, lawyers, or executives, who are willing to invest their time to get the credentialing and Medicare training needed to help prospective and current Medicare beneficiaries or their family members or caregivers.
The two most common types of help we provide in our counseling sessions come from clients who are new to Medicare and those using the program’s annual enrollment period. For example, people often call the SHIP phone lines or visit SHIP offices when they are soon to turn 65, become eligible after receiving disability benefits for two years, or are approaching retirement from a job that provided their health insurance. Or sometimes it is the beneficiary’s spouse, adult child, sibling, or friend who calls. Our clients want to learn the mechanics of enrolling in the program, understand how traditional Medicare differs from MA, hear about their options for supplementing Medicare, and more. As counselors, we are careful to listen to their concerns and to avoid responses that are biased in any particular direction.
During Medicare’s fall annual enrollment period, we sometimes hear from beneficiaries who have learned that their current plan is being discontinued. Medicare Advantage organizations or Part D plan sponsors generally propose to switch them to another of the organization’s plans, but sometimes it turns out that the beneficiary will save a lot of money by looking at other alternatives. We also hear from beneficiaries who would like to find out if their current plan choices are still the best options. In the fall of 2025, the Inflation Reduction Act’s changes to the Part D prescription drug benefit made it particularly important to check for alternative options. Other beneficiaries reach out because they want to switch to different MA plans, consider returning to traditional Medicare from MA, or try an MA plan for the first time. Providing this help often means an extended phone session where we enter the details of the client’s current prescriptions and other information into the Medicare Plan Finder and then tell them the two or three best Part D plans for their particular situation.
Beyond these two most common types of clients, calls come in throughout the year with more specialized requests. Over the past year, we have heard many different stories and requests for help.
A daughter calling about whether her parents, newly moved to the US from overseas, can get coverage from Medicare.
A woman calling to say that her sister (who has dementia) just qualified for Medicaid and wants to know how that will interact with her sister’s existing coverage from both Medicare and Tricare.
A son who wants to understand why his mother, who is getting rehabilitation care after a hospital stay, has received a notice that her MA plan will no longer cover the post-hospital care and wants to know whether they can appeal that decision.
A beneficiary, who has just moved from another state where she was enrolled in an MA plan, wants to know what her options are in her new home state.
A daughter reporting that her father will be going into assisted living and has been told that the facility’s providers don’t participate with her father’s MA plan.
A beneficiary who has been prescribed an expensive medication that is not on her current plan’s formulary and cannot afford to fill the prescription.
A newly eligible beneficiary, about to retire from a job that comes with retiree health benefits, wants to know how that coverage would work with Medicare or whether it makes sense for him to elect to enroll in Part B.
A newly eligible beneficiary is tilting towards enrolling in traditional Medicare and wants to learn about Medigap options.
As counselors, we try our best to find the answers to their questions. It sometimes means an hour on the phone, asking questions and then leading the client through their options. Even those of us who have studied Medicare policy for decades may find that we don’t know the answers to certain questions, but at least we know how to research the answers. Of course, sometimes there is no good answer. At the very least, we put forward some ideas, offer patience in listening to their concerns, and give them guidance. The client gets off the phone, usually with answers or next steps to take, and we hope they feel like their concerns have been heard by a friendly ear. In the words of one recent client, “Before speaking to you, I felt overwhelmed by the whole process. With your help, I’ve gotten a much better understanding and feel more confident about proceeding with my application.”
While the Administration’s proposed budget cuts to the SHIP program would leave around $15 million in annual mandatory funding, the roughly 80 percent funding reduction would certainly reduce the capacity of the program, which has already been operating on years of flat funding, to provide essential services to Medicare beneficiaries and their families. Perhaps some states or communities would step up to replace the lost federal funds if the cuts are made, but inevitably many local SHIPs would be scaled back and many would be eliminated. Although many counselors are volunteers, federal funds pay for the infrastructure, training, and administration needed to support the program, including the cost of local advertising, managing a website, and making presentations at community events. The federal Medicare call center (1-800-Medicare) would presumably remain, but it simply cannot provide the kind of in-depth problem solving that SHIP counselors provide. Nonprofit organizations such as the Medicare Rights Center and the Center for Medicare Advocacy will continue to be available as valuable resources, but they would be challenged to pick up all the clients now helped by local SHIPs.
One of the features that makes the SHIP program unique is its local focus. Counselors are based in a local county program office. As a result, we know the landscape of our community: the MA and Part D plans that operate there, the prominent hospitals and physician groups in the area, and other health, social and other resources provided by the county. That level of help cannot be provided by Medicare’s call center. Furthermore, SHIP counselors must be neutral and unbiased. We do not tell clients that MA is better than traditional Medicare or vice versa; instead we lay out the pros and cons. In shopping for a client’s Part D or MA plan, we consider all options equally, unlike a broker who may receive compensation from just a subset of Medicare Advantage organizations and may not mention all available options.
Because SHIPs rely heavily on volunteers, they are a true bargain—a very small drop in the large bucket of federal dollars spent on health care. Preserving that investment to provide Medicare beneficiaries with an unbiased source of information and advice about their Medicare choices should be an easy decision.
The Trump Administration’s First Regulatory Action on Medicare Advantage Omits Some Prior Authorization Guardrails
On April 4, 2025, the Centers for Medicare & Medicaid Services (CMS) finalized the Contract Year (CY) 2026 Medicare Advantage (MA) and Part D Final Rule. While CMS’s decision not to require Medicare and Medicaid to cover GLP-1 medications for treating obesity is likely to make headlines, another important issue has gotten less attention. The final rule …
On April 4, 2025, the Centers for Medicare & Medicaid Services (CMS) finalized the Contract Year (CY) 2026 Medicare Advantage (MA) and Part D Final Rule. While CMS’s decision not to require Medicare and Medicaid to cover GLP-1 medications for treating obesity is likely to make headlines, another important issue has gotten less attention. The final rule omitted proposals from the Biden administration to the put guardrails around the use of prior authorization in Medicare Advantage—in particular, they did not finalize rules that would have: 1) prohibited MA plans from discriminating against enrollees when using artificial intelligence (AI) to make prior authorization decisions, 2) provided more clarity on the internal rules MA plans are using to approve or deny care, and 3) required more granular reporting of each MA plan’s prior authorization approvals and denials. Since 2023, CMS has taken significant steps to improve prior authorization practices in MA, but in light of the 2026 final rule, legislation may be necessary to further strengthen prior authorization safeguards to ensure beneficiaries don’t experience delays or denials of medically necessary care.
Why this is important
Stakeholders have been eagerly awaiting the Trump administration’s CY 2026 final rule on Medicare Advantage and Part D because it provides one of the first indications of the administration’s approach to regulating the private MA industry. In the Medicare Policy Initiative’s (MPI) March 2025 fact sheet entitled, Prior Authorization in Medicare Advantage, we discussed how policymakers, federal oversight agencies, beneficiary advocates, and researchers have raised concerns that some MA plans misuse prior authorization to delay or deny medically appropriate care for Medicare beneficiaries. In January 2025 the Biden administration proposed several new safeguards and transparency measures to improve prior authorization in MA. In April, 2025, when CMS released the CY 2026 final rule, they adopted some of these changes, but did not finalize many of them. In this MPI blog, we review past regulatory actions on prior authorization, the contents of the CY 2026 final rule, and additional measures that stakeholders may want to consider to further improve guardrails for prior authorization in MA.
Regulatory Actions to Streamline Prior Authorization and Reduce Inappropriate Denials in Medicare Advantage.
In the last few years CMS finalized several regulations that address prior authorization in MA, including: requiring MA plans to cover the same services as traditional Medicare and limiting their ability to use their own internal coverage criteria to deny care— “internal coverage criteria” refers to policies, guidelines, or tools used by MA organization to determine medical necessity for covered services, beyond what is explicitly stated in Medicare law or CMS manuals. They also added continuity of care requirements to ensure that treatment is continued when an enrollee switches plans. Additionally, CMS finalized rules to speed up plan’s prior authorization decisions (within 72 hours for urgent requests) and increased transparency by requiring MA plans to 1) report their overall denial rates on their websites, 2) inform enrollees and providers of specific reasons why they denied care, 3) publicize any internal coverage criteria they use to deny care that is covered by Medicare, 4) establish a committee to review their prior authorization practices, and 5) produce a health equity report to show whether care is being denied more frequently for certain populations. All of these changes will be phased in over time.
In April 2025, CMS finalized the CY 2026 Final Rule on Medicare Advantage and Part D. There were some proposed regulations related to prior authorization that were finalized, and some that were not.
Which prior authorization provisions were finalized? The Trump Administration finalized some Biden administration proposals, including: 1) ensuring MA appeals rules apply to any denial, regardless of whether the decision is made before, during, or after the enrollee received care, 2) clarifying that an enrollee always has the right to appeal denials that affect their ongoing course of treatment, and 3) codifying certain sub regulatory requirements.
Which prior authorization provisions were not finalized? CMS did not finalize the Biden administration’s proposals to 1) further clarify the meaning of internal coverage criteria, 2) require annual health equity analysis be reported by each service rather than aggregated for all services, nor did they 3) finalize rules to ensure the use of AI provides equitable access to care. However, CMS did state in the final rule that the agency will continue to consider whether future rulemaking may be needed in the area of AI. This may open the door for Congress to consider several existing proposals aimed to further improve MA prior authorization practices.
Potential Next Steps to Improve Oversight and Transparency in MA use of Prior Authorization
There has been bipartisan interest in future legislative or regulatory action to ensure that Medicare beneficiaries enrolled in MA plans are not denied medically necessary care. Some proposals include:
The Improving Seniors Timely Access to Care Act. This bipartisan, bicameral legislation is perhaps the most well-known legislative proposal related to prior authorization in MA. In September 2022, an earlier version of the bill unanimously passed the U.S. House of Representatives. Since that time, some of the provisions of this bill were finalized by CMS, but the current iteration of this bill would go further to establish new requirements, such as plan-level reporting on prior authorization metrics (see Transparency section below) and new authority for CMS to set timeframes for “real time” decisions to speed up prior authorization requests (see MPI’s tool: Comparison of CMS Rules and legislation to address Prior Authorization in MA). Back in 2022, there was concern about the bill’s price tag when the non-partisan Congressional Budget Office (CBO) estimated that it would cost approximately $16 billion over a ten-year window. Given that some of the provisions have since been finalized, the current bill would likely be scored much lower.
The use of AI in making prior authorization decisions. As CMS noted in its CY2026 final rule, policymakers remain concerned over the ongoing use of AI in making coverage decisions. In light of recent class action lawsuits, a group of bipartisan, bicameral lawmakers sent a 2024 letter to CMS urging the agency to establish an approval process to review how AI is used in prior authorization and to prohibit its use in coverage denials until systematic reviews are completed. Another group of lawmakers recently re-introduced legislation that would require MA plans to obtain input from physicians in the MA plan’s service area for their prior authorization policies. The legislation would also require denial decisions be made by a physician, as opposed to AI or other technology.
Transparency and reporting of prior authorization practices. Beginning in 2026, CMS will require MA organizations to report more information about their prior authorization practices, including the services that require prior authorization, and the percent of all prior authorization requests that were approved, denied, approved after appeal, and reasons for denials. This information is only required to be reported at the “contract level,” meaning a combination of several or even sometimes dozens of individual plans offered by an MA company, rather than at the “plan level” which would mean reporting these metrics for each individual MA plan. Additionally, this data will be aggregated across all services, such that beneficiaries and oversight agencies will not have assess the prior authorization and denial metrics for a specific test, treatment, nor therapy. The Improving Seniors’ Timely Access to Care Act would require plan-level reporting by individual services, which could allow beneficiaries to compare prior authorization metrics when choosing a plan. It would also require disclosures and information related to the use of AI in prior authorizations.
Although CMS has taken important steps to improve prior authorization processes and reduce inappropriate denials, more work needs to be done to ensure that MA enrollees receive timely access to appropriate care. Policymakers should consider whether requiring more granular reporting at the plan level would improve transparency and help beneficiaries make better-informed choices about their plan options. To ensure that physicians, rather than algorithms, make coverage decisions, guardrails around the use of AI might also be necessary. Finally, policymakers should closely monitor the MA landscape and determine whether additional policies to address prior authorization may be necessary. Ultimately, policymakers need to carefully consider how to find a sustainable balance between timely access to appropriate care and reducing unnecessary, duplicative, or harmful low-value care.
Policy options to cover anti-obesity drugs: Highlighting the Georgetown policy compendium as a resource
The Trump Administration announced on April 4, 2025, that it would not broaden coverage of anti-obesity drugs in Medicare. They did not rule out reconsidering this possibility in the future, however, and others have offered policy proposals for expanding coverage of these drugs. These proposals are included in the compendium of policy options maintained by …
The Trump Administration announced on April 4, 2025, that it would not broaden coverage of anti-obesity drugs in Medicare. They did not rule out reconsidering this possibility in the future, however, and others have offered policy proposals for expanding coverage of these drugs. These proposals are included in the compendium of policy options maintained by Georgetown University’s Medicare Policy Initiative (MPI). We recently updated the compendium, which includes options for making legislative or administrative changes to either Medicare Advantage (MA) or Medicare Part D’s prescription drug benefit, to incorporate new proposals that have surfaced since its December launch. This post highlights the various proposals to expand the Part D program’s coverage criteria to include anti-obesity drugs that are currently excluded from the benefit.
GLP-1 Drugs
Drugs in the glucagon-like-peptide-1 (GLP-1) receptor agonists class were first approved as treatments for type-2 diabetes in 2017. In 2021, a GLP-1 drug was approved for chronic weight management. In 2024, the first GLP-1 drug received approval as a treatment for cardiovascular issues for patients who are obese or overweight. There is additional research showing promising outcomes for other health conditions ranging from dementia to substance abuse cravings, but also concerns about serious side effects such as kidney, pancreas and gastrointestinal problems. Today these drugs are taken by 12 percent of American adults. The list price for a month’s supply of the major GLP-1 drugs was $936 to $1,349 without use of insurance coverage, rebates, or coupons.
Total Medicare spending on these drugs soared from $57 million in 2018 to $5.7 billion in 2022. This growth is especially remarkable given that currently Part D only covers GLP-1 drugs as treatments for diabetes or cardiovascular disease, not for weight loss alone. As of 2023, when Medicare coverage was limited to beneficiaries with a diagnosis of diabetes, about 2.1 million beneficiaries (about 4 percent of all beneficiaries) were having their GLP-1 drugs covered under Part D.
Part D Coverage Options for Anti-Obesity Drugs
When Part D was created under the Medicare Modernization Act of 2003, the law barred coverage for the class of drugs aimed at weight gain or weight loss. This exclusion, modeled after a similar exclusion in Medicaid, reflected the idea that few drugs available at the time for treatment of weight gain or weight loss were safe or effective, thus establishing the exclusion as a means to protect patient safety. The science around GLP-1 drugs has changed the conversation on anti-obesity drugs. As a result, the Biden Administration included a provision in the proposed rule for the 2026 benefit year that proposed to “reinterpret the statutory exclusion of agents when used for weight loss such that it would not apply to drugs when used to treat beneficiaries with obesity.” The proposed reinterpretation would also apply to Medicaid as well as Medicare. On April 4, 2025, the Trump Administration chose not to make this proposal final, thus leaving GLP-1 covered by Medicare only if the beneficiary is prescribed the drug for a diagnosis of diabetes, cardiovascular diseases, or some other eligible diagnosis.
Our compendium includes several other proposals for expanded coverage of weight-loss drugs. Whereas the Biden Administration proposed rule would have allowed an obesity diagnosis as a new coverage criterion, these bills would more broadly remove the current statutory restriction on weight-loss drugs. Companion bills in the 118th Congress, introduced by Rep. Brad Wenstrup (R-OH) and Sen. Thomas Carper (D-DE), would have eliminated the statutory restriction on coverage of weight-loss drugs altogether. The Wenstrup bill was marked up by the House Committee on Ways and Means in June 2024, where it was amended to cover weight-loss drugs only for beneficiaries who had coverage for the drugs from a non-Medicare plan in the year before enrolling in Medicare. The latter represented a substantially lower-cost option that might offer a step in the direction of covering GLP-1 drugs at a much lower cost for the taxpayer. The compendium also includes a proposal from scholars at the USC Schaeffer Center to add weight-loss drugs to the list of covered drugs in Part D.
Cost and Policy Considerations for Expanding Coverage
The added indication of cardiovascular disease combined with obesity or overweight for GLP-1 drugs allowed an estimated 3.6 million Medicare beneficiaries to become eligible to have their drugs covered, though as many as half of them could already be eligible based on a diabetes diagnosis. Expanding coverage to all beneficiaries who are obese or overweight could make as many as 13.7 million beneficiaries (one-fourth of all beneficiaries) eligible for Part D coverage of GLP-1 drugs.
The addition of more potential drug users makes Medicare program costs a major consideration for these proposals. As shown in our compendium, the Congressional Budget Office (CBO) has analyzed an illustrative policy to add weight-loss medications to the list of Part D-covered drugs. It estimated that net federal spending would increase by $35.5 billion from 2026 to 2034. Spending on anti-obesity medicines would total $38.8 billion but would be offset by $3.4 billion in other lower medical spending. CBO assumed that prices for GLP-1 anti-obesity medications would be subject to government negotiation. In fact, Ozempic, Rybelsus, and Wegovy were placed on the list for the second round of price negotiations with the new prices effective in 2027. Cost considerations, however, are complex. The authors of the USC Schaeffer Center proposal make a case for substantially greater medical spending offsets, estimating $176 billion to $245 billion in medical cost offsets over 10 years (though they do not include the cost of paying for weight-loss drugs).
Our compendium also highlights the impact of these policy options on various stakeholders. Inclusion of GLP-1 drugs would place significant cost burdens on Part D plans. As a result, we estimate that Part D enrollees would see higher plan premiums to cover the cost of expanded drug coverage under any of the proposals. Beneficiaries who take GLP-1 drugs would see differing effects depending on whether they were previously prescribed a drug and whether they paid for it out of pocket without Medicare coverage. Manufacturers of GLP-1 drugs should see higher revenues if there is greater take-up of their drugs. The impact of policy changes on the revenues of Part D plan sponsors and actors in the drug supply chain will depend on demand for the drugs, their degree of therapeutic competition, and degree of competition within each supply-chain industry.
Policymakers thus have several options if they want to broaden coverage of anti-obesity drugs. They will need to consider both the cost impact of expanded coverage, the potential for greater access to these drugs, and secondary effects on MA plans, pharmaceutical manufacturers, and other stakeholders.
The Compendium as a Tool for Exploring Policy Ideas
This policy topic—approaches for providing Medicare coverage of anti-obesity medicines—demonstrates how analysts can use the Medicare Policy Initiative’s compendium to explore ideas for addressing timely and critical policy issues. The compendium includes a wide variety of topics, from technical reforms to the MA risk adjustment system to proposals that aim to better inform beneficiaries as they choose between traditional Medicare and private-plan options to potential changes in Part D that could affect drug pricing. We encourage you to delve into the compendium’s broad range of topics in your work, and we welcome your questions, comments, and suggestions for future updates.
Privatizing Medicare: Challenges and Unanswered Questions about Default Enrollment into Medicare Advantage
A number of conservative policymakers and think tanks have pushed to make “privatizing Medicare” part of the current Trump administration’s healthcare agenda. One path toward more privatization is to “default” Medicare beneficiaries into private managed care plans called Medicare Advantage (MA). This would mean that instead of being in traditional Medicare and offered a choice, …
A number of conservative policymakers and think tanks have pushed to make “privatizing Medicare” part of the current Trump administration’s healthcare agenda. One path toward more privatization is to “default” Medicare beneficiaries into private managed care plans called Medicare Advantage (MA). This would mean that instead of being in traditional Medicare and offered a choice, they would instead be auto enrolled in an MA plan, or forced to choose an MA plan at the time they first become eligible for Medicare. If pursued, this would likely drastically decrease the number of beneficiaries in traditional Medicare, and increase the number in private MA plans. Proposals to default beneficiaries into MA have provided little clarity about how such a change would be implemented, nor the potential consequences it would have on federal spending and access to care for Medicare beneficiaries. In this MPIBlog, Medicare beneficiaries’ current enrollment options are reviewed and several barriers and unanswered questions about defaulting beneficiaries into MA are examined.
Current Medicare Choices: Traditional Medicare vs. Medicare Advantage
Currently, new Medicare beneficiaries are “defaulted” into traditional Medicare, but they can choose to receive their Medicare benefits through Medicare Advantage plans which are private managed care organizations. Some of the most common are United HealthGroup, Humana, Cigna, and CVS Health. Currently, over half of the over 60 million Medicare beneficiaries have enrolled in a private MA plan—representing approximately 32.8 million MA enrollees. There are several reasons why beneficiaries may prefer either traditional Medicare or MA.
Beneficiaries who keep traditional Medicare like the flexibility. They can go to any Medicare certified provider in the country and aren’t limited by a provider network. Also, the care, tests and treatments prescribed by their doctors are rarely subject to prior authorizations or denials as they are in MA. However, traditional Medicare can be expensive because there is no limit out-of-pocket expenses and provider visits and hospital stays require copayments. Thus, 89% of traditional Medicare beneficiaries secure some sort of supplemental coverage (through retiree benefits, Medicaid, or purchasing a Medigap plan) that caps spending and covers copayments.
Beneficiaries typically enroll in MA plans because they can be more affordable. Unlike traditional Medicare, MA plans limit out-of-pocket expenses through annual caps. Beneficiaries are also attracted to the extra supplemental benefits advertised by MA plans such as dental, vision, and hearing services which are not covered in traditional Medicare. On the other hand, MA plans typically limit enrollees to specific provider networks and can require prior authorization and deny care and services that would be covered in traditional Medicare.
Barriers to “Privatizing” Medicare” through Default Enrollment into MA
Privatizing Medicare usually refers to proposals to default Medicare beneficiaries into MA plans.In Project 2025, the conservative Heritage Foundation elevated Medicare privatization as a policy priority, proposing that when individuals become eligible for Medicare, MA would be the default enrollment option. The promotion of Medicare privatization is echoed in similar proposals by the Republican Study Committee and the Paragon Health Institute. The latter has posited a forced choice between traditional Medicare and MA for all beneficiaries at the time they first become eligible for Medicare. In his 2020 campaign for the U.S. Senate, Dr. Mehmet Oz, the current nominee to lead the Centers for Medicare & Medicaid Services (CMS), co-authored a piece advocating for “Medicare Advantage for All”, a policy that would leverage private Medicare Advantage (MA) plans to provide health care for more Americans. Potential barriers to implementation of default enrollment are detailed below.
Choice of Medicare program is important to Americans. When the MA program was first implemented, there were bipartisan protections put in place to ensure that Medicare beneficiaries would not be forced into private managed care plans. This was codified into law through section 1851(c) of the Social Security Act. Thus, any change to this protection would require an act of Congress.
Increased enrollment in the Medicare Advantage program would increase federal spending. While many people assume that using managed care will automatically save money, this is not the case with Medicare Advantage. The Medicare Payment Advisory Commission and other researchers estimate that the federal government pays approximately 22% more for MA enrollees than for similar beneficiaries in traditional Medicare, constituting approximately $83 billion in extra spending in 2024. Thus, any increase to MA enrollment would likely result in increased federal spending and could threaten the sustainability of the program.
Requiring beneficiaries to choose an MA plan would require a major effort to increase beneficiaries’ access to accurate and comprehensible information. It has been well documented that it can be difficult for people to make an informed choice between traditional Medicare and MA, and between various MA plans. In 2024, beneficiaries had an average of 42 different MA plans from 8 different companies to choose from, depending on where they live. Even the most basic information that beneficiaries need to compare plans (e.g. whether their doctors are in network, out-of-pocket fees, and what supplemental benefits they qualify for) can be difficult to access. For example, MA provider directories available online are often not up to date. In fact, one CMS study revealed that an average of 50 percent of providers listed as available in MA directories had inaccurate locations, wrong phone numbers, or were not actually accepting new patients– making it difficult for beneficiaries to use this information to make an informed choice of MA plan.
MA plans have also been criticized for not being transparent about the supplemental benefits they offer. While many MA plans advertise coverage of extra supplemental benefits like dental, vision, and hearing services, these are not standardized and it can be difficult to assess the true scope of that coverage (e.g. full dental or partial coverage for cleanings only). Plans also sometimes provide special supplemental benefits for the chronically ill (SSBCI), that include benefits that are not primarily health-related like transportation, groceries, and gym memberships. The fact that enrollees must have a specific chronic illness to be eligible for these benefits is not always included in the advertising and can be misleading to those who buy the plan assuming they will be eligible.
Paid Brokers can give false or misleading guidance to steer beneficiaries into MA plans. Defaulting beneficiaries into MA plans or forcing a choice would require significantly more assistance for beneficiaries and their families. While there are several unbiased, free sources of help for beneficiaries to compare plan costs and services, (e.g. CMS Plan Compare website and State Health Information Program (SHIP) counselors), beneficiaries are most likely to get their information from paid brokers (sometimes called “marketing middlemen”) who are paid by MA plans to promote enrollment. Brokers have been criticized for aggressive marketing tactics and providing false or incomplete information, as well as for enrolling beneficiaries in MA plans without their consent.
Concerns about inadequate access to care in Medicare Advantage: Researchers, advocates, lawmakers, and oversight agencies have raised concerns about access to care for MA enrollees. Some MA plans have been criticized for: 1) requiring prior authorization for services that meet Medicare coverage criteria, 2) using artificial intelligence to issue blanket denials for certain covered services, 3) inappropriate denials of medically necessary care, 4) having inadequate provider networks, especially in rural areas where there are provider shortages, and 5) providing poor access to certain services such as post-acute care/rehabilitation and mental health care. All of these factors could mean that beneficiaries in MA do not get the same benefits as those in traditional Medicare.
Unanswered Questions about Default Enrollment into Medicare Advantage
Many questions would need to be addressed before considering defaulting Medicare beneficiaries into private managed care plans. A few of these are listed below.
Would traditional Medicare still be an option for Americans? If there were a plan to default all 33 million existing traditional Medicare beneficiaries into MA, this would effectively eliminate traditional Medicare as a choice. Alternatively, if only newly eligible Medicare beneficiaries are defaulted in MA, it would slowly decrease the number of beneficiaries in traditional Medicare over time, having major implications for the sustainability and parity of the program. If traditional Medicare is going to be maintained as a choice, there would need to be changes to the program to make it competitive with MA, such as implementing caps on out-of-pocket spending, and offering supplemental benefits like dental, vision, and hearing on para with MA.
How would it be determined which MA plan to default beneficiaries into? If CMS defaults beneficiaries into MA plans, there would need to be a massive effort on the part of CMS to match (auto-enroll) beneficiaries to one MA plan in their region. For example, some Medicaid plans have attempted this with variable success in the past by using fee-for-service data to match beneficiaries with managed care plans that their primary care provider is participating in. This approach was less successful for those without a primary care doctors and for older adults with complex conditions who rely on many specialty providers. It would also be even more difficult for newly eligible Medicare beneficiaries who have no history of Medicare FFS use.
How would important information for beneficiaries be made more accessible in order for them to select a plan? If CMS were to force a choice between traditional Medicare and MA at the time of enrollment, MA plans would need to work quickly to provide information including accurate provider directories, descriptions of eligibility and scope of supplemental benefits, and prior authorization metrics so beneficiaries would have the information and tools they need to make an informed choice.
How would MA plans prepare for this large increase in the number of enrollees? If default enrollment were implemented, MA plans would need to quickly expand their internal operations and increase the number of providers in their networks to adequately to meet the needs of more enrollees. This would be especially difficult in rural areas where there are provider shortages.
How would the federal budget accommodate the increased cost of MA? Given that the federal government spends about 22% more on MA enrollees, policies that increase MA enrollment would likely drive up federal spending. Plans to reduce payments to MA could have an effect on the benefits provided to beneficiaries, providers willingness to participate, and/or the MA plans’ revenue.
Any proposal to promote the privatization of Medicare that involves defaulting beneficiaries into private managed care plans or forcing a choice upon enrollment would raise major challenges for ensuring that beneficiaries’ access to high quality care is maintained. Importantly, policymakers and plans would need to ensure that increased MA enrollment wouldn’t increase federal spending in a way that destabilizes the fiscal integrity of the program or the benefits available to beneficiaries. Finally, policymakers would need to carefully consider whether default enrollment would undermine the principle of Medicare choice that is so highly valued by Americans.
Does Medicare Advantage Save the Government Money?
Medicare Advantage (MA) is a program that allows private health insurance companies to provide Medicare benefits to eligible beneficiaries. This program was established to help reduce government spending on Medicare through leveraging the potential efficiencies of the private sector. However, there is significant debate as to whether this program actually saves the government money compared …
Medicare Advantage (MA) is a program that allows private health insurance companies to provide Medicare benefits to eligible beneficiaries. This program was established to help reduce government spending on Medicare through leveraging the potential efficiencies of the private sector. However, there is significant debate as to whether this program actually saves the government money compared to Traditional Medicare.
In this fact sheet we examine:
Importance of debate on MA’s impact on government spending
MA plans’ efforts to reduce health care spending
Competing evidence around spending on MA versus traditional Medicare.
Download the explainer to learn about potential reforms and how they could improve transparency around government spending on MA.
“Prior authorization” is a utilization management tool employed by health insurers requiring that the enrollee (and/or their provider) receive approval from the health plan before a treatment, procedure, or service will be covered. While the use of prior authorization can effectively reduce “low-value” care, it can lead to delays and denials in necessary care. Private …
“Prior authorization” is a utilization management tool employed by health insurers requiring that the enrollee (and/or their provider) receive approval from the health plan before a treatment, procedure, or service will be covered.
While the use of prior authorization can effectively reduce “low-value” care, it can lead to delays and denials in necessary care. Private Medicare Advantage (MA) plans require prior authorization at a higher frequency than Traditional Medicare. This fact sheet includes:
Why MA Plans use prior authorization
Breaking down prior authorization, appeals, and denials in MA
Problems with prior authorization in MA
Steps and proposals to address prior authorization in MA
Despite prior authorization’s intended purpose to cut costs for the government, MA enrollees cost the Medicare program more than their counterparts in Traditional Medicare. As enrollment in Medicare Advantage grows, it is essential that prior authorization is assessed to improve the experience of enrollees and reduce government spending.
CHIR Medicare Policy Initiative Welcomes Neil Patil as Health Policy Director
Part of the Georgetown University McCourt School of Public Policy’s Center on Health Insurance Reform (CHIR), the Medicare Policy Initiative (MPI) is shining a light on how Medicare and the Medicare Advantage program can be strengthened so that seniors and taxpayers can get the best possible care and value for their money. This new initiative at CHIR …
Part of the Georgetown University McCourt School of Public Policy’s Center on Health Insurance Reform (CHIR), the Medicare Policy Initiative (MPI) is shining a light on how Medicare and the Medicare Advantage program can be strengthened so that seniors and taxpayers can get the best possible care and value for their money. This new initiative at CHIR will be doing rapid turnaround policy analysis and provide technical assistance on issues related to Medicare Advantage payment, coverage, and costs.
Neil Patil, M.P.P. has joined MPI as our new Health Policy Director and will be our lead on Medicare Advantage technical assistance.
As MPI’s new Senior Fellow and Health Policy Director, Neil conducts policy analysis and provides technical assistance to policymakers on Medicare Advantage issues. Prior to joining CHIR, Neil was a Senior Analyst at the Centers for Medicare & Medicaid Services Office of Legislation, where he provided technical assistance to Congress on issues related to Medicare Advantage and the Medicare Drug Price Negotiation Program. Neil has also served as the Legislative Assistant/Clerk in the U.S. House of Representatives, Committee on Ways and Means and as a Policy Associate for the U.S. Senate Committee on Finance.
Did Changes From the Inflation Reduction Act Affect Medicare Beneficiaries’ Plan Decisions During Open Enrollment? Reflections From Two SHIP Counselors
Two research professors from Georgetown University’s Medicare Policy Initiative, Rachel Schmidt and Jack Hoadley, have spent the majority of their careers conducting research and advising federal policymakers on improvements to the Medicare program. They also volunteer directly with Medicare beneficiaries through their counties’ State Health Insurance Assistance Program (SHIP) – a free service where consumers …
Two research professors from Georgetown University’s Medicare Policy Initiative, Rachel Schmidt and Jack Hoadley, have spent the majority of their careers conducting research and advising federal policymakers on improvements to the Medicare program. They also volunteer directly with Medicare beneficiaries through their counties’ State Health Insurance Assistance Program (SHIP) – a free service where consumers can call for unbiased assistance choosing among Medicare options like traditional Medicare, Medigap plans, Medicare Advantage plans, and Medicare Part D prescription plans. In this blog series they share some of the most common challenges beneficiaries face in understanding their constantly shifting Medicare choices, cost, and coverage. All beneficiary names and identifying details have been changed to protect their privacy.
The conversation with 90-year-old Marjorie began over trying to find a new stand-alone Part D prescription drug plan (PDP) that would cover her expensive blood thinner and 10 other medications at affordable copayments. A widow, Marjorie had no family to help her compare plans, so she called her county’s SHIP office. Majorie had traditional Medicare, and like many beneficiaries who aren’t in a Medicare Advantage (MA) plan, she purchased a Medigap policy to reduce the uncertainty about her out-of-pocket costs. She also had a stand-alone PDP. Marjorie had received an Annual Notice of Change from her current PDP and was worried about drug costs on top of the $185 per month she would pay for the Part B premium and $400 per month for her Medigap policy. Her income of about $3,000 a month was too high to qualify for Extra Help with Part D premiums and cost sharing but was low enough to qualify for some assistance from her state towards her drug premium. Yet even with that assistance, Marjorie saw health costs consuming about a quarter of her income. Her concern led her to ask not only about stand-alone drug plans, but also about options for enrolling in a MA plan, even if it meant leaving the doctors she sees regularly.
Majorie needed help with a few different choices:
She could stick with traditional Medicare, where she had a lot of flexibility to choose her providers and find another drug plan, but potentially she could find a PDP that would cover her prescriptions with lower cost sharing.
She could switch into a MA plan that would include Part D prescription coverage and likely lower her out of pocket costs, but she needed help understanding how MA plans operate networks and use prior authorization.
She also needed help figuring out if she would qualify for any of the income-based subsidies that could help her cover out-of-pocket costs.
Marjorie’s story is one of dozens we heard as SHIP counselors during the recent Medicare annual enrollment period when beneficiaries had the opportunity to join or switch stand-alone PDPs and MA plans. The two of us have many decades of experience researching issues in Medicare and health care policy. But more recently, we’ve had the opportunity to volunteer as SHIP counselors, a federally-funded service that provides free counseling to Medicare beneficiaries. We have always understood that Medicare is vitally important for providing health care coverage to tens of millions of beneficiaries and is very complicated. Still, our experiences speaking with beneficiaries leave us humbled and sometimes flabbergasted by the program’s importance and complexity. Our reflections in this post relate primarily to beneficiaries in original Medicare who get Part D benefits through stand-alone PDPs. However, questions about the affordability of PDP premiums and cost sharing are important factors behind why some beneficiaries are choosing to enroll in Medicare Advantage plans.
An important time to compare plans
Many changes taking place in 2025 made the 2024 open enrollment season an especially important time to shop. Implementation of the Inflation Reduction Act (IRA) led to unprecedented structural changes to the Part D benefit:
For 2025, enrollees will pay no more than $2,000 in cost sharing for drugs on their plans’ formularies and can elect a new option through their plan to smooth out deductibles, copayments, and coinsurance over the year (called the Medicare Prescription Payment Plan).
Part D’s standard benefit structure is redesigned, with plan sponsors bearing much more financial risk for their enrollees’ drug spending, as was intended when Part D began back in 2006. Medicare will still subsidize about 75 percent of costs for basic drug benefits, but it will do so more through monthly capitated payments to plans rather than cost-based reinsurance paid on behalf of beneficiaries with high drug costs. Plans must also bear more risk than they did in prior years for enrollees who receive Extra Help with premiums and cost sharing.
How plan sponsors responded to IRA changes
For 2025, plan sponsors reacted to Part D’s changes by submitting bids that, on average, assumed they would incur 42 percent higher costs per enrollee for basic drug benefits.Due in part to a variety of structural issues, stand-alone drug plans have been much more likely to incur losses in Part D than Medicare Advantage prescription drug plans (MA-PDs). In response to these higher bids, CMS initiated a new premium-stabilization demonstration that will pay sponsors an estimated $5 billion in 2025 to thwart PDP premium increases. Reflecting those extra demonstration subsidies, enrollees in PDPs experienced a range of premium increases and decreases. In the states where we counsel beneficiaries, PDP premiums range from zero (no enrollee premium at all) for a plan with a $590 deductible, to nearly $120 per month for a plan with no deductible, supplemental coverage, and a broader formulary.
For a few plan sponsors, another response to policy changes was to reduce their number of PDPs. One, Mutual of Omaha, exited the PDP market entirely. CMS terminated Clear Spring Health’s PDPs due to repeatedly low quality scores. Two sponsors, CVS Health/Aetna and UnitedHealthcare, reduced their numbers of plans. Wellcare, Cigna, and Humana continue to offer three PDPs each nationwide. Nevertheless, while slightly fewer stand-alone drug plans are available than in previous years, in 2025, the average beneficiary could still choose from 14 PDP options and 34 MA-PDs, down from 21 PDPs and 36 MA-PDs in 2024. Notably, while those numbers reflect the small reductions of MA plans open to general enrollment, they exclude sponsors’ expanded offerings of special needs plans for beneficiaries with Medicare and Medicaid and individuals with chronic conditions.
More beneficiaries would benefit from shopping
Every year, Medicare beneficiaries are sent an Annual Notice of Change outlining their Part D or MA plans’ changes in premiums, cost sharing, and coverage for the upcoming year and, in some cases, if the beneficiary will be affected by plan withdrawals or mergers. They are also reminded of the annual enrollment period when they can shop for different plans, use the Plan Finder tool at medicare.gov or call a SHIP office for help. Perhaps because there are so many options, few people compare plans. In 2022, less than a third of beneficiaries in original Medicare took advantage of their annual opportunity to shop.
The volume of calls to our SHIP offices for help comparing drug plans was roughly the same as last year, typically from a small minority of beneficiaries who shop each year. However, a few calls came from beneficiaries (like Marjorie) who read their Annual Notice of Change and found out that their drug copayments or plan premiums were increasing. If a plan is cancelled and the beneficiary doesn’t actively choose a new one, they will typically be enrolled in a PDP run by the same sponsor, sometimes at a higher premium. Similar situations have happened in past years, such as with Eunice, a retired nurse who, with SHIP help, found a plan that saved her hundreds of dollars.
Many more beneficiaries could find substantial savings from shopping, using either CMS’s Plan Finder themselves or asking for SHIP assistance to compare costs for plans that cover their medications. One often overlooked source of savings can come from using a plan’s “preferred cost-sharing pharmacies.” By filling prescriptions at the same pharmacy without comparing plan copayments at different pharmacies, beneficiaries can miss out on sometimes hundreds of dollars of savings over a year simply from switching pharmacies.
Among the beneficiaries we spoke with, many were confused about whether the new $2,000 cap applied to their cost sharing, premiums, or both. It only caps cost sharing. Some were also confused when the Medicare Plan Finder sometimes showed out-of-pocket costs well above $2,000. If a drug is not on a plan’s formulary, the beneficiary must pay the full cost and those expenses do not apply towards the out-of-pocket maximum. Few of our clients were aware of the Medicare Prescription Payment Plan that allows them to smooth cost sharing over the year.
We also found that some beneficiaries will pay far less than $2,000. For example, a client with a prescription for a blood thinner that has a full price of nearly $600 for a 30-day supply ($7,200 for the year) may pay just $520 in total cost sharing during 2025. This situation arises in enhanced PDPs—plans that cover supplemental benefits (eliminating the deductible or lowering cost sharing) beyond Part D’s basic coverage, but generally with higher monthly premiums. Under changes made in the Inflation Reduction Act, supplemental benefits count towards the cap as though they are part of an enrollee’s out-of-pocket spending. While beneficial to the enrollee, this means that far more beneficiaries are likely to reach the $2,000 cap than some might have thought. It will be interesting to see whether beneficiaries with expensive medicines increasingly gravitated towards these PDPs for 2025, as well as whether that affects the availability of plans with supplemental coverage in 2026.
What did Marjorie decide?
As for Marjorie, we talked over all her options, including MA plans in her area. She liked the fact that some MA plans had no monthly premium, but with the number of specialists she sees, Marjorie was concerned that the copayments for visits would add up. She would have to leave her ophthalmologist, who she especially likes; she had called the doctor’s office and found that he doesn’t participate in the networks of MA plans that have no premium. It was difficult to find out from the Plan Finder how much MA plans would charge for a wheelchair or other equipment she might need. If she joined an MA plan, Marjorie would no longer need to pay $400 a month for her Medigap. But if she gave up that policy and later wanted to return to original Medicare, she would likely have a very hard time purchasing a new Medigap. Even though her budget remains tight, for 2025, Marjorie decided to stay with original Medicare and her Medigap but enroll in a different PDP that would save her a little money. She also plans to revisit her decision next year.
Looking forward
The changes made in Part D for 2025 will have a significant effect for many Medicare beneficiaries in reducing their out-of-pocket costs. But others will probably fail to see the savings because they simply stayed in their plan without doing the shopping needed to move to a different plan. We also see many beneficiaries like Marjorie who are tempted by the savings available from enrolling in an MA plan, but they see downsides: being forced to leave a trusted doctor, worrying about whether prior authorization requirements may block them from needed care, and fearing that they cannot regain Medigap coverage if the MA plan doesn’t work out for them. The tools and support for shopping exist, but too often the information or the resources to find and use those tools do not. Ideally, Medicare should find better ways to encourage beneficiaries to make smart choices and to support them in those efforts.
What to Know About CMS’s Announcement That it Plans to Terminate VBID
On December 16, CMS announced its intention to terminate the Medicare Advantage (MA) Value-Based Insurance Design (VBID) demonstration at the end of 2025 due to the model’s substantial cost. Evaluations of the VBID model found $2.3 billion higher program spending associated with the model in 2021 and $2.2 billion in 2022. Below we describe what …
On December 16,CMS announced its intention to terminate the Medicare Advantage (MA) Value-Based Insurance Design (VBID) demonstration at the end of 2025 due to the model’s substantial cost. Evaluations of the VBID model found $2.3 billion higher program spending associated with the model in 2021 and $2.2 billion in 2022. Below we describe what VBID is and how its termination could affect benefits and cost sharing for Medicare beneficiaries enrolled in certain MA plans. Whether the incoming Administration maintains the decision to terminate the VBID demonstration remains to be seen.
What is VBID?
The VBID demonstration was launched by the CMS Innovation Center in 2017 to test the idea that providing MA plan sponsors with flexibility to target additional benefits towards certain groups of enrollees could reduce Medicare program spending and improve quality of care. As with all supplemental benefits offered by MA plans, plan sponsors finance VBID benefits through Part C rebates, which are generated from the difference between MA payment benchmarks and plan bids.
Originally, MA plans offered primarily health-related supplemental benefits such as limited dental, vision, and hearing coverage uniformly to all of their enrollees.
VBID allows MA plans to offer both uniform supplemental benefits as well as nonmedical benefits addressing health-related social needs such as food, transportation, and housing, or Part D financial rewards and incentives (a form of cash-equivalent benefit) to enrollees with low incomes or in certain geographic areas of socioeconomic disadvantage.
In 2024, the most common VBID benefits were assistance with food and utilities.
How are VBID benefits different from other supplemental benefits that MA plans can provide?
All MA plans can target nonmedical benefits to certain enrollees through SSBCI. However, there are several ways in which SSBCI differs from VBID.
Through SSBCI, MA plans can only use certain medically complex chronic conditions to qualify enrollees for nonmedical supplemental benefits.
In comparison, VBID enrollees can qualify for supplemental benefits based on: 1) certain chronic health conditions, 2) Low-Income Subsidy (LIS) eligibility (or, in the territories, dual eligibility for both Medicare and Medicaid), 3) place of residence in the most underserved areas, or 4) a combination of those factors.
VBID allows for flexibilities in Part D drug benefits while SSBCI does not. For example, MA plans participating in the VBID model often lower enrollees’ cost sharing to $0 per prescription or may use reward and incentive programs to promote medication adherence or participation in medication therapy management programs.
Why have MA plan sponsors emphasized using the VBID model in their D-SNPs?
Because D-SNP enrollees are dually eligible for Medicare and Medicaid, they have much of their cost sharing paid by Medicare Savings Programs and Part D’s LIS. Thus, plan sponsors do not need to cover those costs through Part C rebates and can use VBID flexibility for other types of benefits.
D-SNPs that participate in the VBID model do not need to reduce enrollees’ medical cost sharing because it is already paid by Medicaid-run Medicare Savings Programs.
Similarly, D-SNPs typically waive cost sharing for Part D prescriptions filled by enrollees with the LIS. However, plan sponsors only pay for the nominal cost-sharing amounts set in law for LIS enrollees, not each plan’s full cost-sharing amounts. (In 2025, LIS enrollees pay no more than $4.90 per generic and $12.15 per brand prescription.) D-SNPs typically only include basic Part D benefits, with Medicare’s LIS paying for the bulk of enrollees’ cost sharing.
What is the evidence about VBID’s costs?
When the CMS Innovation center launches a new model, they are required to evaluate its impact on Medicare spending. Early findings from a RAND evaluation suggest that while VBID was associated with some improvements in care quality and medication adherence, it was also associated with higher costs.
Plan participation in VBID was associated with higher enrollee risk scores, both for non-SNP and D-SNP enrollees. RAND found that the VBID model may have contributed to higher risk scores by enabling plans to identify new diagnoses or reestablish existing ones.
Higher costs were driven in part by higher risk scores and larger Part C rebate payments to VBID plans. CMS also noted that enrollees in VBID plans had higher Part D expenditures.
The CMS Innovation center determined that there were no further modifications to the model that could be made to offset the substantially higher costs.
What could happen if VBID ends?
If VBID is terminated it could affect: 1) the supplemental benefits offered by MA plans, 2) which beneficiaries qualify for supplemental benefits, as well as 3) beneficiaries’ cost sharing.
MA plans that want to offer nonmedical supplemental benefits to their enrollees will need to use SSBIC instead of VBID. CMS says that many of the VBID model’s most widely used interventions are now available throughout the MA program including through the SSBCI pathway. If the VBID model is terminated at the end of 2025, the availability of nonmedical supplemental benefits could be affected by whether plan sponsors are willing to expand their use of SSBCI.
If MA plans expand their use of SSBCI, it means that beneficiaries will only qualify for supplemental benefits based on certain chronic conditions. Unless there are changes to SSBCI authority, beneficiaries will no longer qualify based on low incomes nor living in communities of socioeconomic disadvantage.
MA plans will no longer be able to provide rewards and incentives for Part D health-related behaviors.
Ending VBID could lead to higher drug cost sharing for Medicare beneficiaries enrolled in D-SNPs:
If VBID ends, MA plans could include prescription drug benefits at $0 cost sharing in their D-SNPs, but only if they offer it as part of an enhanced Part D plan rather than the basic coverage they now provide. MA plans would have to rely less on Part D’s LIS to pick up most of those enrollees’ cost sharing and plans would incur more of the financial liability. As a result, D-SNP enrollees may find that fewer plan options are available in the future that have zero cost sharing for their drug benefits.
CMS acknowledges that some beneficiaries may see some changes in their Part D prescription drug benefits. The agency says that the CMS Innovation center’s new $2 drug list model, which it aims to start in 2027, would help make prescription drugs more affordable.
In light of the decision to terminate VBID, there are several potential actions that various stakeholders could take:
The new Administration will need to decide if they will uphold the decision to end the VBID program or reverse the decision.
Medicare beneficiaries will have the option during the 2026 annual enrollment period (in the fall of 2025) to choose an MA plan that offers supplemental benefits through SSBCI or get their benefits through original Medicare.
MA plans can choose to offer more supplemental benefits through SSBCI or offer fewer supplemental benefits.
CMS could expand SSBCI to allow MA plans flexibility to offer nonmedical supplemental benefits and/or rewards and incentives on the basis of income or other factors similar to VBID.
MA plan sponsors could include prescription drug benefits at $0 cost sharing in their D-SNPs as part of enhanced Part D plans but would need to accept more financial liability to do so.
[Event] Prior Authorization in Medicare Advantage: Balancing Patient Access and Program Costs
At this February 4, 2025 event, policy experts discussed the use of prior authorization in Medicare Advantage plans and its impact on care and costs. Speakers included: Watch the full recording here.
At this February 4, 2025 event, policy experts discussed the use of prior authorization in Medicare Advantage plans and its impact on care and costs. Speakers included: